
Inner-Knee Pain After Surgery? The Saphenous Nerve May Be the Missing Clue

Knee surgery is usually performed with one goal in mind: less pain and better movement. Yet some people find themselves months after surgery with a frustratingly persistent pain along the inner side of the knee. The X-rays may look good. The surgical wound may have healed. The knee replacement may be properly positioned, or the ligament or meniscus repair may appear structurally successful. Still, touching one particular area of the knee can produce burning, stabbing, tingling, or even an electric-shock-like sensation.

In some of these cases, the problem may not be coming from the knee joint itself.

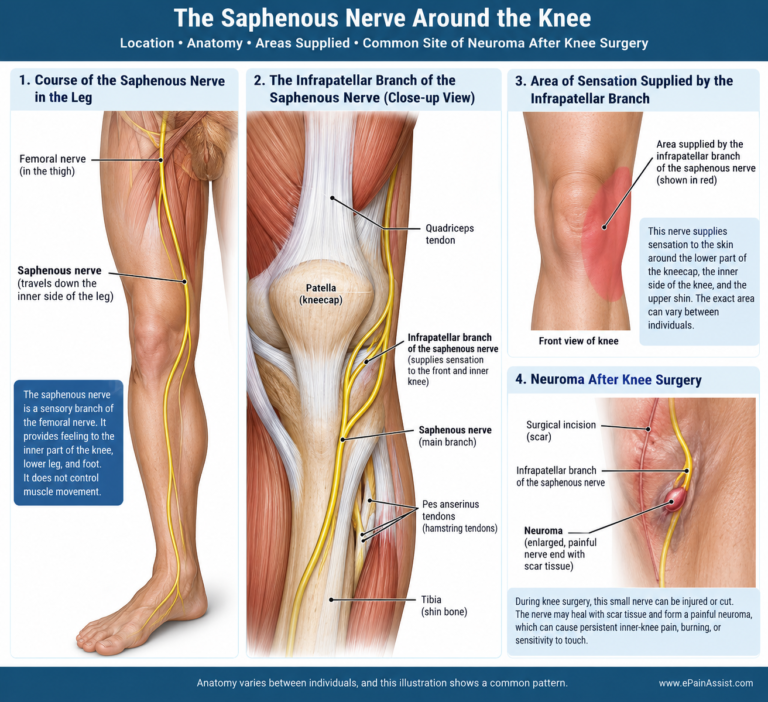
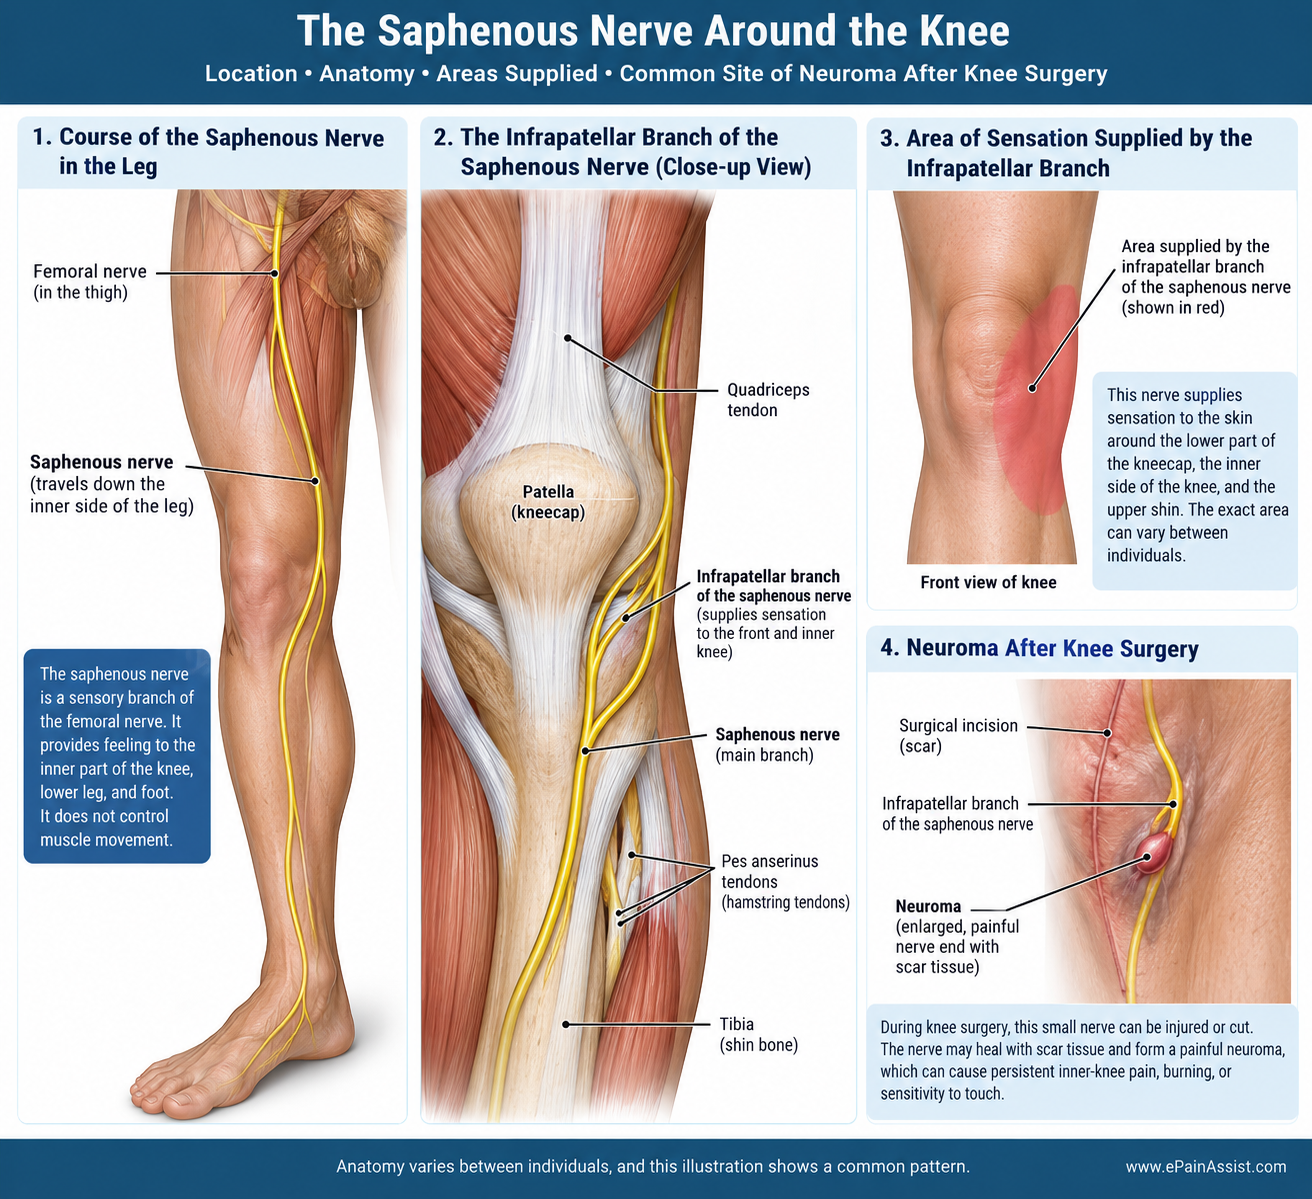
A small sensory nerve called the saphenous nerve, particularly its infrapatellar branch, can be injured during knee surgery. If the injured nerve develops abnormal scar tissue at its end, a painful saphenous nerve neuroma may form. This is an often-overlooked explanation for persistent medial or inner-knee pain following knee replacement, ligament reconstruction, arthroscopy, meniscus surgery, and other procedures around the knee. [1,2]

Although the term medial saphenous nerve neuroma is sometimes used to describe this problem, many cases of postsurgical pain around the front and inner knee specifically involve the infrapatellar branch of the saphenous nerve. This distinction can be important because the location of symptoms often provides one of the strongest clues to the diagnosis. [1,3]

What Is the Saphenous Nerve?

The saphenous nerve is a sensory branch of the femoral nerve. Unlike nerves that control muscle movement, the saphenous nerve primarily carries sensation from parts of the knee, lower leg, and inner side of the leg toward the foot.
Inner-Knee Pain After Surgery? The Saphenous Nerve May Be the Missing Clue

As the saphenous nerve travels down the thigh, it passes through an area known as the adductor canal. Around the knee, it gives off several branches. One of the most clinically important is the infrapatellar branch of the saphenous nerve.

This small nerve travels across the front and medial aspect of the knee and supplies sensation to skin around the lower patella, upper shin, and anteromedial knee. Its exact path varies considerably from one person to another. Anatomical studies have demonstrated substantial variation in the location and branching pattern of the nerve, meaning there is no single surgical incision that can completely eliminate the possibility of injury. [3,4]

That anatomical variability helps explain why the nerve can become injured during otherwise technically successful knee surgery.

What Is a Medial Saphenous Nerve Neuroma?

A neuroma is not usually a tumor in the traditional sense.

When a peripheral nerve is cut, stretched, compressed, or otherwise significantly injured, the nerve attempts to repair itself. Regenerating nerve fibers normally try to grow toward their original destination. When the normal pathway has been disrupted by surgery, scar tissue, or trauma, however, those nerve fibers may grow in a disorganized fashion.

The result can be a small collection of abnormal nerve tissue known as a traumatic neuroma.

Many nerve injuries produce only numbness or altered sensation and never become significantly painful. A painful neuroma develops when the damaged nerve becomes hypersensitive and repeatedly generates abnormal pain signals.

Around the knee, this can produce persistent focal neuropathic pain despite apparently satisfactory healing of the underlying joint.

Why Can a Saphenous Nerve Neuroma Develop After Knee Surgery?

The infrapatellar branch runs relatively close to the skin and surgical field around the front and inner knee. Because of this superficial position, it can be vulnerable to several forms of injury.

The nerve may be:

  • Cut during an incision
  • Stretched by surgical positioning or retractors
  • Compressed by postoperative scar tissue
  • Entrapped within healing tissue
  • Irritated by nearby hardware or surgical fixation
  • Injured during harvesting of tissue for ligament reconstruction
  • Damaged during placement of arthroscopy portals

Injury to the infrapatellar branch of the saphenous nerve has been described following total knee replacement, knee arthroscopy, anterior cruciate ligament reconstruction, meniscus surgery, and other procedures involving the anteromedial knee. [1,5]

Importantly, nerve injury does not automatically mean a painful neuroma will develop. Numbness around a knee incision is relatively common following certain knee operations, particularly knee replacement. Only a portion of patients with sensory nerve injury develop clinically significant neuropathic pain or a symptomatic neuroma. [6]

Saphenous Nerve Neuroma After Total Knee Replacement

One of the most recognized settings for this condition is persistent pain following total knee replacement.

Traditional knee replacement surgery commonly requires an incision along the front of the knee. Small sensory nerve branches may cross the area of the incision and can therefore be divided during surgical exposure.

Research has documented sensory changes in the distribution of the infrapatellar branch following total knee replacement, although most sensory changes do not result in severe chronic pain. [6]

In a smaller subgroup of patients, however, the divided nerve may form a painful neuroma.

This possibility becomes especially important when a patient continues to experience localized medial knee pain after knee replacement despite satisfactory implant positioning and no obvious infection, loosening, instability, or other mechanical explanation.

Recent research has suggested that neuromas may be underrecognized among patients with otherwise unexplained persistent pain following total knee replacement. [7]

What Does Saphenous Nerve Neuroma Pain Feel Like?

The quality of pain is often different from typical arthritis or mechanical knee pain.

Patients may describe:

  • Burning pain along the inner knee
  • Sharp or stabbing pain near the surgical scar
  • Electric-shock sensations
  • Tingling or pins-and-needles
  • Extreme sensitivity to light touch
  • Pain when clothing rubs against the knee
  • Pain when kneeling
  • Focal tenderness over one small area
  • Numbness surrounding an unusually painful spot
  • Pain radiating toward the front of the knee or upper inner shin
  • A sensation that the skin itself hurts

Some patients can identify one remarkably specific point that triggers the symptoms.

Pressing or tapping this location may cause pain to shoot along the distribution of the nerve. This phenomenon is sometimes referred to as a Tinel sign and can provide an important diagnostic clue. [8]

Pain From Light Touch Can Be an Important Clue

One particularly characteristic feature of neuropathic knee pain is allodynia.

Allodynia means something that should not normally be painful—such as a bedsheet, trouser leg, light finger pressure, or gentle touch—causes significant discomfort.

Hyperesthesia, or unusually intense sensation from normal stimulation, may also occur.

These symptoms point more strongly toward sensory nerve irritation than toward arthritis, ligament injury, or many other structural knee disorders.

Where Is the Pain From an Infrapatellar Saphenous Nerve Neuroma Located?

Pain is often concentrated around the:

  • Inner side of the knee
  • Lower inner border of the kneecap
  • Area immediately beside a surgical incision
  • Front-inner portion of the upper shin
  • Region between the kneecap and tibial tubercle

However, nerve anatomy varies considerably. The exact painful area therefore differs between patients. [3,4]

This is one reason symptoms do not always fit perfectly into textbook diagrams.

Can a Saphenous Nerve Neuroma Cause Knee Stiffness?

Yes—but usually indirectly.

The infrapatellar branch of the saphenous nerve is a sensory nerve and does not directly control knee muscles. Nevertheless, severe nerve pain can make patients reluctant to bend, straighten, kneel, or load the knee.

Over time, this pain-limited movement may resemble true mechanical stiffness.

A published case described severe knee pain and stiffness following total knee replacement that improved after removal of an infrapatellar saphenous nerve neuroma. The authors referred to this type of pain-related restriction as a potentially reversible form of “pseudoarthrofibrosis.” [9]

This is clinically important because treating the knee as though scar-related joint stiffness were the only problem may not adequately address a painful nerve.

Why Saphenous Nerve Pain Is Sometimes Missed

Persistent pain after knee surgery has a long list of possible causes. Physicians understandably first look for problems involving the joint or surgical reconstruction itself.

Following knee replacement, for example, doctors may need to evaluate for:

  • Infection
  • Implant loosening
  • Instability
  • Malalignment
  • Abnormal implant rotation
  • Patellar tracking problems
  • Fracture
  • Tendon problems
  • Arthrofibrosis
  • Bursitis
  • Referred pain from the hip or spine

Chronic pain after total knee replacement is often multifactorial, and localized nerve injury is only one possible explanation. [10]

Because nerve-related pain may not appear on ordinary X-rays, patients can sometimes go through repeated imaging studies without discovering why a particular part of the knee remains exquisitely painful.

The diagnosis becomes more likely when mechanical and infectious causes have been investigated and the patient has focal, neuropathic pain in the anatomical distribution of the saphenous nerve.

How Is a Medial Saphenous Nerve Neuroma Diagnosed?

There is no single test that diagnoses every case. Instead, physicians usually combine the patient’s history, physical examination, imaging when appropriate, and response to a diagnostic injection.

Medical History

A doctor will want to know:

  • Where the pain is located
  • Whether the pain began after surgery
  • Whether there is numbness or tingling
  • What type of surgery was performed
  • Whether touching the skin triggers pain
  • Whether symptoms radiate along the inner knee or leg
  • Whether the pain feels burning, shooting, or electric
  • Whether movement or weight-bearing changes the pain

The relationship between symptoms and the surgical scar may provide another clue.

Physical Examination

During examination, the physician may gently palpate along the expected course of the saphenous nerve and infrapatellar branch.

A highly localized tender point with radiating nerve pain is particularly suggestive.

A positive Tinel sign—where tapping over the injured nerve reproduces tingling or shooting pain—has been used as part of the clinical diagnosis in patients with painful infrapatellar saphenous nerve neuromas. [8]

Ultrasound

High-resolution musculoskeletal ultrasound can be particularly useful because the nerve is superficial.

Ultrasound may help a physician identify:

  • Localized enlargement of the nerve
  • Neuroma formation
  • Nerve entrapment
  • Scar tissue surrounding the nerve
  • Abnormal relationships between the nerve and nearby structures

Ultrasound can also guide diagnostic or therapeutic injections directly around the suspected nerve. [1,11]

Diagnostic Saphenous Nerve Block

A diagnostic nerve block can be one of the most useful steps when the diagnosis remains uncertain.

A physician injects a small amount of local anesthetic near the suspected nerve.

If the patient’s characteristic pain improves substantially for the duration of the anesthetic, it provides evidence that the nerve is contributing to the pain.

Diagnostic local anesthetic blocks are commonly used when considering more definitive nerve treatment and appear particularly valuable in selecting patients for surgical treatment. [8,12]

Saphenous Nerve Neuroma Versus Other Causes of Inner-Knee Pain

Not every case of medial knee pain after surgery comes from a nerve.

Several conditions can produce discomfort in a similar region.

Pes Anserine Bursitis

Pes anserine bursitis commonly causes tenderness along the inner upper shin below the knee joint. The pain is generally more aching or activity-related than electric or burning. Extreme skin sensitivity and tingling are less typical.

Medial Meniscus Problems

A medial meniscus tear usually produces pain around the medial joint line and may be associated with catching, locking, twisting pain, or swelling. Neuroma pain is more likely to be superficial, burning, hypersensitive, and reproducible by touching a particular point.

Medial Collateral Ligament Injury

Medial collateral ligament problems may cause tenderness along the ligament and pain with stress placed across the knee. They do not typically cause a localized electric shock when the skin is touched.

Lumbar Radiculopathy

A pinched nerve in the lower back can produce pain, tingling, or numbness extending into the leg. However, the distribution is usually broader, and symptoms may be accompanied by back pain, weakness, altered reflexes, or other neurological findings.

Complex Regional Pain Syndrome

Complex regional pain syndrome may produce severe burning pain and hypersensitivity after surgery or injury. However, symptoms are generally more widespread and may include abnormal swelling, temperature changes, skin color changes, sweating changes, and movement impairment.

Correctly distinguishing these conditions matters because their treatments can be very different.

Treatment for Medial Saphenous Nerve Neuroma After Knee Surgery

Treatment depends on the severity of the symptoms, duration of pain, underlying nerve abnormality, previous treatment, and how strongly diagnostic testing implicates the saphenous nerve.

Activity Modification and Desensitization

For milder nerve irritation, treatment may initially focus on reducing repetitive pressure over the painful area. Physical or occupational therapy may include gentle desensitization techniques designed to reduce excessive sensitivity of the affected skin. Maintaining knee motion is also important because guarding the knee because of pain can contribute to stiffness and functional decline.

Medications for Neuropathic Pain

When symptoms have a clear neuropathic quality, physicians may consider medications used for nerve pain rather than relying solely on conventional anti-inflammatory medication. Depending on the patient’s medical history, treatment may include medications such as gabapentin, pregabalin, duloxetine, or other agents used in neuropathic pain management. These medications treat abnormal pain signaling rather than removing the neuroma itself, and they are not appropriate for everyone. Medication selection should therefore be individualized by a physician.

Ultrasound-Guided Injection

Ultrasound-guided treatment allows medication to be placed accurately around the irritated nerve. Local anesthetic, sometimes combined with corticosteroid or other interventional techniques, may provide relief in selected patients. Small clinical studies have reported improvement in patients with infrapatellar saphenous neuralgia following ultrasound-guided local treatment. [11]

Hydrodissection

When scar tissue appears to be trapping the nerve, an ultrasound-guided technique called hydrodissection may sometimes be considered. Fluid is carefully injected around the nerve in an attempt to separate it from surrounding scarred or adherent tissue. This is different from surgically removing a neuroma and is generally considered an interventional treatment for selected cases of nerve entrapment or neuritis.

Radiofrequency and Cryoablation

For persistent pain that responds to diagnostic nerve blocks but returns, some pain specialists may consider procedures aimed at interrupting pain transmission through the affected sensory nerve.

Options described in the literature include:

  • Radiofrequency treatment
  • Cryoablation
  • Other targeted denervation techniques

Because these procedures intentionally modify sensory nerve signaling, careful patient selection and accurate identification of the painful nerve are important. [13]

Peripheral Nerve Stimulation

Peripheral nerve stimulation is another option that may be considered for selected cases of refractory neuropathic knee pain. A small electrical stimulation system is positioned near the targeted peripheral nerve to modify pain signaling. This treatment is generally reserved for persistent cases after more conservative options have failed and requires assessment by an appropriately trained pain specialist.

Surgery for a Painful Saphenous Nerve Neuroma

When pain is severe, persistent, clearly localized to a neuroma, and non-surgical treatment has failed, surgical treatment may be considered. The procedure may involve identifying the abnormal nerve segment, removing the painful neuroma, and managing the remaining nerve end in a way intended to reduce recurrent irritation.

In a series of patients with chronic painful infrapatellar saphenous nerve neuromas following surgery or trauma, surgical treatment produced meaningful improvement in many appropriately selected patients. [5]

Another study involving patients with persistent medial knee pain caused by infrapatellar saphenous neuroma after total knee replacement found substantial pain improvement after neuroma excision. The diagnosis in those patients included both a positive Tinel sign and pain relief following selective local anesthetic nerve block. [8]

A more recent systematic review and meta-analysis also found substantial improvement in pain following selective neurectomy for infrapatellar pain syndrome, although the available evidence largely consists of retrospective observational studies rather than large randomized trials. [12]

Surgery is therefore not automatically appropriate for every patient with medial knee pain. The key is demonstrating that the targeted nerve is genuinely responsible for the symptoms.

What Happens If a Saphenous Nerve Neuroma Is Left Untreated?

The course varies.

Some minor nerve injuries gradually become less noticeable as the nervous system adapts. Others remain stable without causing major functional limitations.

A painful neuroma, however, may continue generating abnormal nerve signals for months or years.

Patients may begin avoiding kneeling, exercise, prolonged walking, certain clothing, or even touching the affected knee. Chronic guarding can then contribute to reduced movement and loss of confidence in the operated leg.

Persistent unexplained pain may also lead to repeated tests or even consideration of additional joint surgery when the original joint reconstruction is not actually the source of the symptoms.

For that reason, identifying the true pain generator is particularly important before another major knee procedure is performed.

When Should Persistent Pain After Knee Surgery Be Evaluated?

Some discomfort, swelling, numbness, and altered skin sensation can occur during normal recovery after knee surgery. However, medical evaluation is appropriate when pain:

  • Persists longer than expected
  • Becomes progressively worse
  • Is strongly burning, shooting, or electrical
  • Is triggered by very light touch
  • Is concentrated around one small point near the surgical scar
  • Is associated with persistent numbness or tingling
  • Continues despite otherwise satisfactory knee healing
  • Prevents rehabilitation or normal knee movement

Neuroma should not simply be assumed. Infection, blood clots, fractures, implant problems, and other complications may require evaluation depending on the type of surgery and symptoms.

Urgent medical attention is particularly important for significant calf swelling or pain, chest pain, shortness of breath, fever, drainage from the surgical wound, rapidly increasing redness, or severe unexplained swelling.

Can Saphenous Nerve Neuroma Be Prevented During Knee Surgery?

Completely eliminating the risk is difficult.

Anatomical studies have shown that the infrapatellar branch of the saphenous nerve varies considerably between individuals, and investigators have not identified a universal surgical “safe zone” that guarantees avoidance of the nerve. [3,4]

Surgeons nevertheless use anatomical knowledge, careful tissue handling, appropriate incision planning, and meticulous surgical technique to minimize unnecessary nerve injury whenever possible.

It is also important to understand that numbness around an incision does not necessarily indicate a surgical complication requiring treatment. Small superficial sensory nerves may be affected during necessary surgical exposure without producing meaningful long-term problems.

The concern becomes greater when nerve injury produces persistent neuropathic pain rather than an uncomplicated patch of numb skin.

Persistent Inner-Knee Pain After Surgery Should Not Always Be Blamed on the Joint

A knee can be mechanically stable and still hurt.

That is one of the most important lessons in patients with persistent pain following otherwise successful knee surgery.

If the pain is highly localized, burning, electric, associated with numbness or tingling, and unusually sensitive to touch—especially near the inner knee or surgical scar—the saphenous nerve and its infrapatellar branch deserve consideration.

Diagnosis requires more than simply finding tenderness. The physician must evaluate competing causes of postoperative knee pain, examine the sensory nerve distribution, and sometimes use ultrasound or a diagnostic nerve block to confirm that the nerve is responsible.

Once correctly identified, treatment may range from desensitization and medication to ultrasound-guided procedures, targeted nerve treatments, or surgical neuroma excision.

For patients who have spent months wondering why their knee still hurts despite reassuring scans and apparently successful surgery, recognizing a medial saphenous nerve neuroma can sometimes provide the missing explanation.

References:

  1. Boyle J, Eason A, Hartnett N, Marks P. Infrapatellar branch of the saphenous nerve: A review. Journal of Medical Imaging and Radiation Oncology. 2021;65(2):195-200. doi:10.1111/1754-9485.13141.
  2. Peng MSJ, et al. Infrapatellar branch of saphenous nerve: from anatomy, sonoanatomy to its clinical implications. Regional Anesthesia and Pain Medicine. 2026. doi:10.1136/rapm-2025-106383.
  3. Kerver ALA, et al. The surgical anatomy of the infrapatellar branch of the saphenous nerve in relation to incisions for anteromedial knee surgery. Journal of Bone and Joint Surgery. 2013. doi:10.2106/JBJS.L.01297.
  4. Anatomical Study of the Infrapatellar Branch of the Saphenous Nerve in Humans. Revista Brasileira de Ortopedia. Available through PubMed Central.
  5. Regev GJ, et al. Management of chronic knee pain caused by postsurgical or posttraumatic neuroma of the infrapatellar branch of the saphenous nerve. Journal of Orthopaedic Surgery and Research. 2021;16. PMID: 34289862.
  6. Fate of the infrapatellar branch of the saphenous nerve post total knee arthroplasty. Knee. PMID: 16174002.
  7. Neuromas and Persistent Postoperative Pain Following Total Knee Arthroplasty. Journal of the American Academy of Orthopaedic Surgeons. 2025. PMID: 40600805.
  8. Chalidis B, et al. Surgical treatment outcome of painful traumatic neuroma of the infrapatellar branch of the saphenous nerve during total knee arthroplasty. World Journal of Orthopedics. 2021/2022. PMID: 35036343.
  9. Ilfeld BM, et al. Neuroma of the infrapatellar branch of the saphenous nerve: a cause of reversible knee stiffness after total knee arthroplasty. Journal of Arthroplasty. 2008. doi:10.1016/j.arth.2007.07.019.
  10. Wylde V, et al. Chronic pain after total knee arthroplasty. EFORT Open Reviews. 2018;3:461-470. doi:10.1302/2058-5241.3.180004.
  11. Clendenen S, et al. Infrapatellar saphenous neuralgia after total knee arthroplasty can be improved with ultrasound-guided local treatments. Clinical Orthopaedics and Related Research. 2015.
  12. Selective neurectomy as surgical treatment for infrapatellar pain syndrome: A systematic review and meta-analysis. PubMed PMID: 42176450.
  13. Infrapatellar Branch of the Saphenous Nerve: Therapeutic Approaches to Chronic Knee Pain. Current Pain and Headache Reports. 2024. PMID: 38294640.

Bucket-Handle Meniscus Tear: Symptoms, Causes, Diagnosis, and Treatment Options

A knee that suddenly refuses to straighten can be alarming. Sometimes there is significant pain and swelling; in other cases, the most noticeable problem is simply that something inside the knee seems to be physically blocking movement.

One possible cause is a bucket-handle meniscus tear, a distinctive type of meniscus injury in which a relatively large strip of torn meniscal tissue shifts away from its normal position. Because the displaced piece can move toward the center of the knee joint, it may interfere with normal knee movement and produce the classic symptom associated with this injury: a locked or partially locked knee.

Bucket-handle tears are different from many smaller meniscus tears. The torn tissue remains attached at its ends, creating a long mobile fragment that resembles the handle of a bucket. These injuries often occur after twisting or pivoting movements and are particularly important in younger, physically active people. They may also occur together with an anterior cruciate ligament injury. [1,2]

Although surgery is common for displaced bucket-handle tears, treatment is not identical for everyone. The patient’s age, symptoms, tear location, tissue quality, blood supply, associated injuries, activity level, and degree of displacement all influence whether the meniscus can be repaired or whether another treatment is more appropriate.

What Is a Bucket-Handle Meniscus Tear?

The knee contains two crescent-shaped pieces of fibrocartilage called the medial meniscus and lateral meniscus. They sit between the thighbone and shinbone and help distribute forces across the knee.

The menisci act as more than simple cushions. They contribute to:

  • Shock absorption
  • Distribution of body weight across the knee
  • Joint stability
  • Smooth movement between the bones
  • Protection of the articular cartilage covering the joint surfaces

A bucket-handle tear usually begins as a vertical or longitudinal tear running through a substantial portion of the meniscus. The inner portion can then separate and flip toward the center of the knee while remaining attached at both ends.

It is this displaced fragment that gives the injury its name.

Bucket-handle tears represent a minority of all meniscus tears but are clinically important because the displaced tissue can cause significant mechanical symptoms. Reviews have estimated that they account for roughly 10% to 26% of meniscal tears, depending on the population studied and definitions used. [2,3]

Why Does a Bucket-Handle Meniscus Tear Cause the Knee to Lock?

Knee locking is one of the strongest clues that a displaced meniscus tear may be present.

Normally, the meniscus remains along the edge of the knee joint as the knee bends and straightens. With a bucket-handle tear, the mobile portion of meniscus may flip inward toward the space between the thighbone and shinbone.

The displaced tissue can become trapped between moving joint surfaces.

As a result, a person may try to straighten the knee but reach a point where movement suddenly stops. It can feel as though something is physically caught inside the joint.

This is sometimes called a mechanically locked knee.

Not every person with a bucket-handle meniscus tear develops complete locking. Some experience intermittent catching instead. The knee may occasionally straighten normally and then become stuck again after turning, squatting, or changing position.

A knee that remains physically locked or cannot fully straighten deserves prompt medical assessment because a displaced meniscal fragment may be preventing normal joint motion. [2,3]

Symptoms of a Bucket-Handle Meniscus Tear

Symptoms vary according to how the injury occurred and whether the meniscus fragment has displaced.

Knee locking or catching

The most characteristic symptom is difficulty fully straightening the knee. A person may describe the knee as:

  • Locked
  • Jammed
  • Stuck
  • Catching during movement
  • Unable to straighten completely

Some patients can manipulate or move the leg until the knee “unlocks,” while others continue to have restricted motion.

Pain along the knee joint

Pain is often felt along the inner or outer joint line.

A medial bucket-handle meniscus tear usually causes pain along the inside of the knee, whereas a lateral tear tends to cause symptoms along the outside.

Pain may become worse with:

  • Squatting
  • Pivoting
  • Twisting
  • Running
  • Climbing stairs
  • Getting out of a chair
  • Deep knee bending

Knee swelling

Swelling may develop within several hours or gradually over the following day or two.

Some people initially continue walking after the injury and notice increasing stiffness and swelling later. This pattern is also seen with other meniscus injuries. [1]

Loss of range of motion

The patient may be unable to fully extend or deeply flex the knee.

Loss of extension is particularly important when the displaced meniscus fragment is physically obstructing motion.

A popping sensation

Some people recall feeling or hearing a pop when the injury occurs. However, a pop is not specific to a meniscus tear and can occur with ligament injuries as well.

Knee instability or giving way

The knee may feel unreliable or suddenly buckle during walking.

This does not necessarily mean that the meniscus itself is the only source of instability. Because bucket-handle tears can occur together with ligament injuries, the entire knee should be evaluated.

What Causes a Bucket-Handle Meniscus Tear?

Twisting the knee while the foot is planted

A common mechanism is forceful rotation of the knee while the foot remains planted on the ground.

This can occur during sports such as:

  • Football
  • Soccer
  • Basketball
  • Tennis
  • Wrestling
  • Skiing
  • Rugby

Cutting or changing direction quickly can place substantial rotational stress on the meniscus.

Deep squatting combined with rotation

A deeply bent knee places different forces on the meniscus. Turning or twisting while in this position may contribute to tearing, especially if the meniscus has already been weakened.

Sudden traumatic knee injury

A bucket-handle tear can occur during a fall, collision, awkward landing, or other traumatic knee injury.

Degenerative changes in the meniscus

Not every bucket-handle tear occurs during sports.

With aging, meniscal tissue becomes less elastic and more vulnerable to tearing. A relatively ordinary movement that would not injure a healthy younger meniscus may tear degenerative tissue.

Therefore, older adults sometimes develop meniscal tears after comparatively minor twisting movements. [1,2]

Bucket-Handle Meniscus Tears and Anterior Cruciate Ligament Injuries

An important relationship exists between bucket-handle tears and anterior cruciate ligament injuries.

The anterior cruciate ligament helps control forward and rotational movement of the knee. When it tears, the abnormal forces generated during the injury can damage the meniscus at the same time.

Meniscal damage may also develop later in an unstable knee.

Bucket-handle tears involving the medial meniscus are generally more common overall, while lateral bucket-handle tears are particularly relevant in younger athletes with associated anterior cruciate ligament injuries. [2]

For this reason, evaluating a suspected bucket-handle tear involves examining the entire knee rather than focusing only on the meniscus.

Is a Bucket-Handle Meniscus Tear Serious?

It can be.

The seriousness depends less on the label itself and more on factors such as:

  • Whether the meniscus is displaced
  • Whether the knee is locked
  • Size and location of the tear
  • Meniscal blood supply
  • Quality of the remaining tissue
  • Presence of cartilage damage
  • Associated ligament injury
  • Age and activity level of the patient

A small stable meniscus tear without mechanical symptoms is very different from a displaced bucket-handle tear preventing the knee from extending.

Recent international rehabilitation consensus recommendations note that larger traumatic tears and bucket-handle tears, particularly in younger patients, may warrant earlier surgical evaluation. [4]

When Should You See a Doctor for a Locked Knee?

Seek medical assessment if a knee injury causes persistent pain, swelling, catching, or difficulty moving the joint normally.

Evaluation becomes particularly important when:

  • The knee cannot fully straighten
  • The knee remains locked
  • Walking is very difficult
  • Significant swelling develops
  • The knee repeatedly gives way
  • Symptoms started after a twisting sports injury
  • Pain and mechanical symptoms do not improve
  • There was a significant traumatic injury

A locked knee does not automatically prove that a bucket-handle tear is present. Loose cartilage, bone fragments, severe arthritis, other meniscus tears, and several less common knee conditions can also interfere with motion.

The cause therefore needs to be established rather than assumed.

How Is a Bucket-Handle Meniscus Tear Diagnosed?

Diagnosis usually combines the history of the injury, physical examination, and imaging.

Medical history

The clinician will want to know exactly how the problem began.

Questions may include:

  • Did the knee twist?
  • Was the foot planted?
  • Did you hear or feel a pop?
  • Did swelling occur immediately or later?
  • Can the knee straighten completely?
  • Does it catch or lock?
  • Where is the pain?
  • Has the knee given way?
  • Have you previously injured the knee?

Mechanical locking after a twisting injury raises suspicion for a displaced meniscus tear.

Physical Examination for a Bucket-Handle Meniscus Tear

The clinician examines the knee for swelling, tenderness, stability, and range of motion.

Tenderness along the joint line is common.

Several examination maneuvers can also help detect meniscal pathology, including the McMurray test and Thessaly test. These tests deliberately place stress across the meniscus and may reproduce pain, clicking, or catching.

No single physical examination test is perfect. Using the patient’s symptoms, joint-line tenderness, motion findings, and several provocative tests together generally provides more useful information. [1,5]

In a truly locked knee, some examination maneuvers may be difficult or impossible to perform because the patient cannot move through the required range.

Do X-Rays Show a Bucket-Handle Meniscus Tear?

Standard x-rays do not show the meniscus well because the meniscus is soft tissue rather than bone.

Nevertheless, an x-ray may still be useful.

It can help identify other causes of knee symptoms, including:

  • Fractures
  • Significant osteoarthritis
  • Bone abnormalities
  • Changes in joint spacing

When a bucket-handle meniscus tear is suspected, magnetic resonance imaging is usually much more informative.

Magnetic Resonance Imaging for a Bucket-Handle Meniscus Tear

Magnetic resonance imaging provides detailed images of the menisci, ligaments, cartilage, tendons, and other soft tissues inside the knee. It is generally the preferred imaging method for diagnosing an acute meniscus tear. [1]

A radiologist may identify not only the tear but also the displaced meniscal fragment.

Several characteristic imaging patterns have been described in bucket-handle tears, including:

  • A displaced fragment within the intercondylar notch
  • The double posterior cruciate ligament sign
  • An absent bow-tie appearance
  • A flipped meniscus appearance
  • Truncation of the normal meniscal contour

Seeing more than one characteristic finding can improve diagnostic confidence. [3,6]

Magnetic resonance imaging can also reveal associated injuries, including damage to the anterior cruciate ligament, cartilage, or other structures.

Can a Bucket-Handle Meniscus Tear Heal Without Surgery?

This is one of the most common questions patients ask after receiving the diagnosis.

The answer is: sometimes, but many displaced symptomatic bucket-handle tears are treated surgically.

The meniscus does not have equal blood supply throughout its entire width. The outer portion receives considerably more blood than the inner portion. Tears closer to the vascular outer edge therefore generally have greater healing potential. [1]

Non-surgical management may be considered in selected patients when:

  • Symptoms are relatively mild
  • The tear is chronic and not producing significant mechanical symptoms
  • The knee is not locked
  • Surgical risks outweigh the potential benefits
  • Significant underlying arthritis changes the treatment goals
  • The patient’s functional demands are low

A displaced tear that repeatedly catches or physically blocks knee extension presents a different problem. Physical therapy can strengthen muscles and improve motion, but exercises cannot reliably reposition and heal a large fragment that remains mechanically trapped inside the joint.

Accordingly, contemporary reviews describe surgical repair as the preferred treatment for many repairable symptomatic bucket-handle tears. [2]

Initial Treatment Before Definitive Management

Before the final treatment decision is made, measures may be used to control pain and swelling.

These can include:

Activity modification

Avoid pivoting, deep squatting, running, jumping, and other activities that reproduce locking or significant pain.

Ice

Intermittent cold application can help reduce pain and swelling during the acute period.

Compression and elevation

Compression and elevation may help manage swelling.

Pain medication

Nonsteroidal anti-inflammatory drugs or other pain relievers may be appropriate for some patients, depending on their medical history and other medications.

These measures may make the knee feel better, but symptom relief does not necessarily mean that a displaced meniscus has healed.

Surgery for a Bucket-Handle Meniscus Tear

When surgery is needed, it is typically performed through knee arthroscopy.

During arthroscopy, a surgeon inserts a small camera into the knee through a small incision. Additional instruments are introduced through other small incisions.

The surgeon can directly inspect:

  • The torn meniscus
  • The displaced fragment
  • Cartilage surfaces
  • Ligaments
  • Other structures inside the joint

The two major surgical possibilities are meniscus repair and partial meniscectomy.

Meniscus Repair: Preserving the Torn Meniscus

Whenever the tear is suitable for repair, preserving the meniscus is generally preferred.

During a repair, the displaced portion is returned to its normal anatomical position and secured so the tissue has an opportunity to heal.

Repair can be performed using several techniques, including all-inside or inside-out suturing methods. Modern evidence indicates that both approaches can produce substantial functional improvement, although reported failure rates vary among studies. [7]

Preservation matters because the meniscus plays an important role in distributing forces across the knee.

The American Academy of Orthopaedic Surgeons clinical practice guidance supports preserving as much functional meniscal tissue as possible when surgery is indicated and notes that meniscal repair can provide advantages over partial removal in appropriate acute tears with healing potential. [5]

What Makes a Bucket-Handle Tear Repairable?

Not every bucket-handle meniscus tear can be repaired.

The surgeon considers several factors, including:

  • Location of the tear
  • Blood supply
  • Quality of the meniscal tissue
  • Size and length of the tear
  • Chronicity of the injury
  • Ability to reposition the displaced fragment
  • Stability of the repaired tissue
  • Patient age and activity level
  • Associated ligament injuries
  • Condition of the knee cartilage

A relatively fresh longitudinal tear near the vascular outer portion of an otherwise healthy meniscus may be an excellent candidate for repair.

A severely degenerative, fragmented, or poor-quality meniscus may not hold sutures reliably.

Importantly, the final decision about repairability is sometimes made during arthroscopy after the surgeon can directly inspect the tissue.

Partial Meniscectomy for a Bucket-Handle Tear

If the torn fragment is damaged beyond repair, the surgeon may perform a partial meniscectomy.

Rather than removing the entire meniscus, the surgeon trims away the unstable damaged portion while preserving as much healthy meniscal tissue as possible.

Partial meniscectomy often allows faster initial rehabilitation because the tissue does not have to be protected while a repair heals.

However, removing meniscal tissue also reduces the amount of shock-absorbing and load-distributing tissue remaining in the knee. This is one reason modern treatment has increasingly emphasized meniscus preservation when repair is feasible. [5]

Meniscus Repair Versus Partial Meniscectomy: Which Is Better?

There is no single answer for every patient.

Meniscus repair has the major advantage of preserving tissue, but healing takes time and rehabilitation tends to be longer.

Partial meniscectomy provides faster early recovery in many patients, but permanently removes part of the meniscus.

For a young patient with healthy tissue and a repairable bucket-handle tear, preservation is generally particularly valuable.

For an older patient with extensively degenerative tissue that cannot hold a repair, partial removal of an unstable fragment may be more realistic.

The goal is therefore not simply to choose the operation with the shortest recovery. It is to restore knee function while preserving as much useful meniscal tissue as reasonably possible.

How Successful Is Bucket-Handle Meniscus Repair?

Results are generally favorable in appropriately selected patients, although re-tearing and failure remain possible.

One systematic review and meta-analysis estimated an overall failure rate of approximately 14.8% following arthroscopic bucket-handle meniscus repair, although results differed between patient groups and studies. [8]

Another study of acute traumatic bucket-handle tears reported a clinical healing rate above 80% at follow-up, with most patients achieving acceptable symptomatic outcomes. [9]

More recent systematic review data also show improvement in patient-reported outcomes following both all-inside and inside-out repair techniques, although reported failure rates vary considerably. [7]

These numbers should not be interpreted as a guarantee for an individual patient. Tear characteristics, tissue quality, associated injuries, surgical technique, rehabilitation, and length of follow-up can all influence results.

Recovery After Bucket-Handle Meniscus Surgery

Recovery differs substantially between meniscus repair and partial meniscectomy.

Recovery after meniscus repair

After a repair, the surgeon must balance two goals:

  • Restoring movement and muscle function.
  • Protecting the healing meniscus from excessive stress.

The rehabilitation program may initially regulate:

  • Weight-bearing
  • Knee flexion
  • Brace use
  • Squatting
  • Rotational activities
  • Running and jumping

Current international consensus recommendations favor rehabilitation based on both time and functional milestones rather than the calendar alone. Progression should consider swelling, range of motion, quadriceps control, strength, and stability. [10]

For repaired vertical meniscal tears, rehabilitation may continue for at least several months. Deep loaded squatting, jumping, and rotational knee movements are generally restricted during the early healing period. [10]

Recovery after partial meniscectomy

Recovery is usually faster because there is no repaired tissue that must biologically heal together.

Patients commonly progress according to:

  • Pain
  • Swelling
  • Range of motion
  • Strength
  • Balance
  • Functional control

The exact timeline depends on the patient and procedure.

When Can You Return to Sports After a Bucket-Handle Meniscus Tear?

Return to sport should not be determined solely by how many weeks have passed since surgery.

The knee should demonstrate adequate:

  • Range of motion
  • Strength
  • Stability
  • Neuromuscular control
  • Ability to perform sport-specific movements
  • Absence of significant swelling
  • Confidence during activity

A recent international consensus recommended that return to sport after meniscus surgery be both criterion-based and time-based. It suggested approximately 4 to 12 weeks after partial meniscectomy and approximately 6 to 9 months after meniscus repair, depending on the procedure, associated injuries, rehabilitation progress, and sport. [4]

A competitive athlete returning to cutting and pivoting sports will generally face different demands than someone whose goal is ordinary walking and recreational exercise.

What Happens If a Bucket-Handle Meniscus Tear Is Left Untreated?

Not every untreated tear inevitably worsens, but an unstable displaced tear can remain problematic.

Possible concerns include:

  • Persistent knee locking
  • Recurrent catching
  • Pain
  • Swelling
  • Restricted motion
  • Difficulty exercising or playing sports
  • Ongoing abnormal joint mechanics

Repeated mechanical symptoms can substantially interfere with daily life.

Long-term preservation of meniscal tissue is also important because the meniscus protects the cartilage surfaces of the knee. Loss of functional meniscal tissue can increase loading on joint cartilage and is associated with later degenerative changes.

This does not mean that everyone with a bucket-handle tear will eventually develop arthritis. Long-term risk depends on multiple factors, including the amount of functioning meniscus remaining, cartilage health, limb alignment, body weight, ligament stability, activity exposure, and other characteristics.

Frequently Asked Questions

Can You Walk With a Bucket-Handle Meniscus Tear?

Yes, some people can. The ability to walk does not rule out a significant meniscus tear. A person may continue walking immediately after an injury and develop progressively greater pain, swelling, stiffness, or locking over the next several hours or days. [1] Others may have difficulty bearing weight from the beginning. Because bucket-handle tears vary considerably, the severity of pain alone does not determine whether the tear is displaced or repairable.

Can a Bucket-Handle Meniscus Tear Unlock by Itself?

Sometimes the displaced fragment moves temporarily, allowing the knee to straighten again. This can create a confusing pattern in which the knee locks, suddenly releases, and later locks again. Temporary improvement does not necessarily mean the tear has healed. A mobile torn fragment may simply have changed position. Recurrent locking or catching should therefore be assessed even when the knee feels relatively normal between episodes.

Is Physical Therapy Enough for a Bucket-Handle Meniscus Tear?

Physical therapy is extremely important in meniscus care, but whether it can serve as the main treatment depends on the tear. Exercise-based treatment may be appropriate for selected stable or non-displaced meniscal injuries and is often valuable for improving strength, movement, and function. However, physical therapy cannot mechanically stitch torn tissue together or reliably remove a large displaced fragment from the center of the knee. A patient with a persistently locked knee therefore requires a different evaluation from someone who has mild pain from a stable tear without mechanical symptoms. Physical therapy also plays a major role after surgery, particularly for restoring quadriceps strength, knee motion, balance, coordination, and confidence.

Can a Bucket-Handle Meniscus Tear Happen Again After Repair?

Yes. A repaired meniscus may fail to heal completely or may tear again following another injury. Possible warning signs of a recurrent tear include return of joint-line pain, recurrent swelling, new catching, knee locking, loss of motion, or symptoms following another twisting injury. Repair failure rates vary substantially across studies, which is why outcome figures should be viewed as estimates rather than precise predictions for an individual patient. [7,8]

The Bottom Line

A bucket-handle meniscus tear is a distinctive knee injury in which a long portion of torn meniscus can flip inward and interfere with normal joint movement. Pain and swelling are common, but the symptom that often raises the greatest concern is locking or inability to fully straighten the knee.

Magnetic resonance imaging is usually the preferred imaging study for identifying the tear and displaced fragment, although the diagnosis begins with the patient’s history and physical examination.

Treatment depends on the characteristics of the tear. Stable, minimally symptomatic tears may occasionally be treated without surgery, but a displaced bucket-handle tear causing mechanical locking often requires orthopedic surgical evaluation.

When surgery is required, preserving the meniscus through meniscus repair is generally favored whenever the tissue has reasonable healing potential. Partial meniscectomy remains useful when damaged tissue cannot be successfully repaired.

The distinction matters because the meniscus is an important part of the knee, not disposable cartilage. Successful treatment is therefore about more than getting an athlete back on the field or making a locked knee move again. Whenever possible, the longer-term goal is to restore function while preserving enough healthy meniscus to continue protecting the joint for years to come.

References:

  1. American Academy of Orthopaedic Surgeons. Meniscus Tears. OrthoInfo. Updated patient education resource covering causes, symptoms, diagnosis, and treatment of meniscal tears.
  2. Ross P, Livingston M, Saraf SM, Miller JR, Mulcahey MK. Bucket-Handle Meniscus Tears: Epidemiology, Diagnosis, Management, and Outcomes. JBJS Reviews. 2025;13(12). doi:10.2106/JBJS.RVW.25.00144.
  3. Current Concepts on Meniscal Repairs. Review discussing bucket-handle tear characteristics, mechanical symptoms, magnetic resonance imaging findings, and repair principles.
  4. The Formal EU-US Meniscus Rehabilitation 2024 Consensus: Part II—Prevention, Nonoperative Treatment and Return to Sport. International expert consensus addressing traumatic meniscal tears and return-to-sport criteria.
  5. American Academy of Orthopaedic Surgeons. Clinical Practice Guideline for the Management of Acute Isolated Meniscal Pathology. Published 2024.
  6. Magnetic Resonance Imaging in the Diagnosis of Bucket Handle Tears: What Is the Current Situation? Review of characteristic imaging signs associated with bucket-handle meniscal tears.
  7. Dzidzishvili L, Berreta RS, Jackson GR, et al. All-Inside and Inside-Out Repair Techniques for Bucket-Handle Meniscus Tears Both Result in Improved Patient Outcomes and a Broad Range of Failure Rates: A Systematic Review. Arthroscopy. 2024;40(9):2477-2490.e1.
  8. What Is the Failure Rate After Arthroscopic Repair of Bucket-Handle Meniscal Tears? A Systematic Review and Meta-Analysis. Study reporting pooled outcomes and risk factors following bucket-handle meniscus repair.
  9. Clinical Outcome and Healing Rate After Meniscal Bucket Handle Tear Repair. Study evaluating clinical and radiological healing after repair of acute traumatic bucket-handle meniscus tears.
  10. The Formal EU-US Meniscus Rehabilitation 2024 Consensus: Part I—Rehabilitation Management After Meniscus Surgery. International recommendations regarding rehabilitation following meniscal repair and meniscectomy.

Ankle Equinus Contracture and Foot Pain: How Limited Ankle Dorsiflexion Affects Walking, Plantar Fasciitis, and the Achilles Tendon

A painful heel does not always begin in the heel. Sometimes the problem starts several inches higher, where a tight calf prevents the ankle from moving normally.

This is one reason ankle equinus contracture can be easy to overlook.

People with ankle equinus have limited ankle dorsiflexion—the ability to bring the top of the foot toward the shin. The restriction may come from a tight gastrocnemius muscle, tightness involving both major calf muscles, a shortened Achilles tendon, joint stiffness, or another underlying condition.

The body still has to move forward when you walk, however. If the ankle cannot provide enough movement, something else has to compensate. The heel may leave the ground too soon. The foot may roll inward. Pressure may shift toward the ball of the foot. The Achilles tendon and plantar fascia may be exposed to altered forces.

For some people, this produces no obvious symptoms. For others, limited ankle dorsiflexion may be one piece of the puzzle behind recurring plantar fasciitis, Achilles tendon pain, metatarsalgia, calluses, or persistent foot fatigue.

The connection is important—but it is also easy to oversimplify. Ankle equinus is not the cause of every case of plantar fasciitis or Achilles tendinopathy. Instead, it is a biomechanical factor that can increase stress in certain people, particularly when combined with repetitive loading, footwear issues, training changes, foot structure, body weight, or other medical conditions.

Understanding what happens when the ankle stops moving normally helps explain why treating only the painful spot sometimes fails to provide lasting relief.

What Is Ankle Equinus Contracture?

Ankle equinus contracture refers to restricted upward movement of the ankle.

That upward movement is called ankle dorsiflexion.

You use ankle dorsiflexion countless times during an ordinary day. It occurs when:

  • Your shin moves forward over your foot while walking.
  • You descend stairs.
  • You squat while keeping the heel on the ground.
  • You walk uphill.
  • You run.
  • You lunge forward.
  • You rise from certain seated positions.

The calf muscles play an important role in controlling this movement.

The gastrocnemius, which forms much of the visible bulk of the calf, crosses both the knee and ankle. The soleus lies deeper and crosses the ankle but not the knee. Both eventually contribute to the Achilles tendon.

When these structures become excessively tight, they can restrict dorsiflexion.

Isolated gastrocnemius tightness is considered an important cause of restricted ankle dorsiflexion, and limited dorsiflexion has been associated with altered gait mechanics and several foot disorders. [1]

Why a Small Loss of Ankle Movement Can Matter

The foot and ankle do not work as isolated hinges.

During normal walking, the heel contacts the ground and the body gradually moves forward over the planted foot. As this happens, the shin advances over the ankle.

For that movement to occur smoothly, the ankle must dorsiflex.

Imagine trying to walk while wearing a boot that prevents your ankle from bending. You could still move forward, but you would have to change the way you walk.

The body does something similar with ankle equinus contracture.

Depending on the severity and the person’s anatomy, compensation may occur through:

  • Earlier lifting of the heel.
  • Increased motion through the midfoot.
  • Increased inward rolling of the foot.
  • Turning the foot outward while walking.
  • Shortening the stride.
  • Bending the knee differently.
  • Changing hip movement.
  • Shifting pressure toward the forefoot.

Not every person develops all of these changes. In mild ankle equinus, compensation may be so subtle that the person never realizes the ankle is stiff.

That is why someone can arrive at a clinic complaining of heel pain or pain under the ball of the foot and discover during examination that ankle dorsiflexion is restricted.

Ankle Equinus Contracture Can Change the Way You Walk

One of the most important effects of limited ankle dorsiflexion is altered tibial progression.

Tibial progression simply means the forward movement of the shin over the foot during the stance phase of walking.

If the calf-Achilles complex prevents the shin from progressing normally, the body needs another way to move its center of mass forward.

Early Heel Rise

A common compensation is lifting the heel sooner than normal.

Once the heel rises, the ankle no longer needs as much dorsiflexion for the body to continue moving forward.

The trade-off is that body weight moves toward the front of the foot earlier in the walking cycle.

Repeated thousands of times each day, that change may increase loading beneath the metatarsal heads and other parts of the forefoot.

Increased Foot Pronation

Some people compensate by allowing more movement through the foot itself.

The arch may flatten and the foot may roll inward to obtain additional functional movement.

This does not mean that everyone with ankle equinus will develop a flat foot. It means that the foot may use motion elsewhere to compensate for motion that is unavailable at the ankle.

Turning the Foot Outward

Another person may walk with the feet pointed outward.

Turning the foot outward can make it easier for the body to move forward without requiring as much straight-ahead ankle dorsiflexion.

Again, the compensation solves one problem but may change forces elsewhere in the foot and leg.

Can Limited Ankle Dorsiflexion Cause Foot Pain?

It can contribute to foot pain, although the relationship differs from person to person.

The key is load distribution.

When the ankle is restricted, forces that would ordinarily be shared across the ankle-foot system may become concentrated elsewhere.

Research involving people with diabetes provides particularly useful evidence because plantar pressure has been studied extensively in this population.

A systematic review and meta-analysis found that ankle equinus had a statistically significant association with increased plantar pressures in people with diabetes. Several of the included studies also found a relationship between limited ankle dorsiflexion and elevated plantar pressure. [2]

An earlier study of 1,666 people with diabetes similarly found that those with ankle equinus had significantly higher peak plantar pressures and were nearly three times more likely to present with elevated plantar pressure. [3]

These findings should not automatically be generalized to every healthy adult with a tight calf. Plantar loading is influenced by many factors, and other research has suggested that ankle equinus accounts for only part of increased forefoot pressure.

Still, the overall message is useful: when ankle movement becomes restricted, pressure under the foot can change.

Ankle Equinus Contracture and Plantar Fasciitis

The relationship between limited ankle dorsiflexion and plantar fasciitis is one of the best-known clinical connections.

The plantar fascia is a strong band of connective tissue running along the bottom of the foot from the heel toward the toes. It helps support the arch and plays an important role in foot mechanics during walking.

Plantar fasciitis typically causes pain near the bottom of the heel, often worst with the first few steps after waking or after sitting for a prolonged period.

A tight gastrocnemius can increase resistance when the shin attempts to move forward over the foot. This may change loading through the heel and plantar fascia.

The relationship is supported by clinical research.

In a prospective study involving 254 people with plantar fasciitis, 83 percent had limited ankle dorsiflexion. Fifty-seven percent had an isolated gastrocnemius contracture, while another 26 percent had contracture involving the broader gastrocnemius-soleus complex. [4]

That is a striking association, but it should be interpreted correctly.

It does not mean that 83 percent of plantar fasciitis is “caused” by ankle equinus. Plantar fasciitis is multifactorial. What the study demonstrates is that restricted ankle dorsiflexion is very common among people presenting with this condition.

How Tight Calf Muscles May Increase Plantar Fascia Stress

The relationship makes more sense when we look at the calf, heel bone, and plantar fascia as parts of a mechanical chain.

The gastrocnemius and soleus transmit force through the Achilles tendon to the heel bone. The plantar fascia begins from the underside of that same heel region and extends forward beneath the foot.

The exact anatomical continuity between the Achilles tendon and plantar fascia has been debated, and studies suggest that the structural relationship changes with age. Nevertheless, anatomical and biomechanical research supports a functional relationship between these tissues through the heel. [5]

When the calf is short or excessively tight:

  1. The ankle resists dorsiflexion.
  2. Forward movement of the shin becomes more difficult.
  3. The heel may rise prematurely.
  4. The foot may compensate through increased motion.
  5. Mechanical stress through the plantar heel and arch may increase.

A review of plantar fasciopathy similarly describes gastrocnemius tightness as increasing Achilles tendon tension and ankle dorsiflexion stiffness, potentially increasing tension on the plantar fascia during weight-bearing. [6]

This is why examining the calf and ankle is often worthwhile in someone whose plantar fasciitis keeps returning despite treating the heel itself.

Why Plantar Fasciitis May Keep Returning When the Ankle Stays Tight

Imagine repeatedly treating a pressure point without addressing what is creating the pressure.

Ice, supportive shoes, insoles, and temporary activity modification can calm heel pain. But if a significant ankle dorsiflexion restriction remains, the same mechanical pattern may return when normal activity resumes.

That does not mean calf stretching is a universal cure.

It means that treatment should look beyond the site of pain.

The 2023 clinical practice guideline for plantar heel pain recommends both plantar fascia-specific stretching and gastrocnemius-soleus stretching as part of treatment. The guideline also supports therapeutic exercise for the foot and ankle musculature and recommends that orthoses, when used, generally be combined with other treatments rather than relied upon as an isolated solution. [7]

Ankle Equinus and Achilles Tendon Pain

The relationship between limited dorsiflexion and the Achilles tendon is slightly different.

The Achilles tendon transmits force from the calf muscles to the heel. It is heavily loaded during walking, running, jumping, and pushing off the ground.

When calf tightness restricts ankle dorsiflexion, tension through the gastrocnemius-Achilles system may increase.

Limited ankle dorsiflexion has therefore been investigated as a possible risk factor for Achilles tendinopathy.

One prospective study followed healthy military recruits through six months of intensive training. Recruits who subsequently developed midportion Achilles tendinopathy had more limited ankle dorsiflexion at baseline than those who remained uninjured. [8]

More recent research in collegiate runners also found reduced ankle dorsiflexion among runners who later developed Achilles tendinopathy, although running injuries are multifactorial and ankle motion was not the only biomechanical difference identified. [9]

These studies support an association rather than proving that ankle equinus alone causes Achilles tendinopathy.

Training volume, sudden increases in activity, previous tendon problems, calf strength, running mechanics, age, recovery, and other factors may all matter.

Tight Calf or Achilles Tendinopathy: Which Comes First?

Sometimes the answer is not obvious.

A tight gastrocnemius may increase mechanical demand on the Achilles tendon.

But Achilles tendon pain can also lead someone to move less, avoid ankle motion, and develop secondary calf stiffness.

In other words, pain and stiffness can reinforce one another.

This is one reason a clinician may assess both:

  • Achilles tendon tenderness and thickening.
  • Calf strength.
  • Ankle dorsiflexion.
  • Gastrocnemius flexibility.
  • Soleus flexibility.
  • Walking or running mechanics.
  • Recent changes in activity.

A person with Achilles tendon pain should not assume that aggressive calf stretching is automatically the solution.

A Special Consideration With Insertional Achilles Tendon Pain

Insertional Achilles tendinopathy affects the area where the Achilles tendon attaches to the heel bone.

Deep ankle dorsiflexion can compress this portion of the tendon against the heel.

That creates an important treatment distinction.

Someone with midportion Achilles tendinopathy and limited ankle dorsiflexion may benefit from carefully prescribed stretching. Someone with highly irritable insertional Achilles tendon pain may initially need to avoid forcing the heel far below the level of the forefoot.

Current Achilles tendon rehabilitation guidelines emphasize individualized treatment rather than simply stretching every painful Achilles tendon. [10]

Can Ankle Equinus Cause Pain Under the Ball of the Foot?

Yes, forefoot pain is another possible consequence.

When the heel lifts early during walking, weight transfers to the forefoot sooner.

This may increase loading beneath the metatarsal heads.

Over time, excessive forefoot loading can potentially contribute to:

  • Metatarsalgia.
  • Pain beneath the ball of the foot.
  • Thick calluses.
  • Stress-related symptoms.
  • Aggravation of existing toe deformities.
  • Difficulty walking barefoot on hard surfaces.

This explains why a clinician evaluating chronic metatarsalgia may examine ankle dorsiflexion even if the patient has no ankle pain.

Limited dorsiflexion has been associated clinically with metatarsalgia and other foot conditions. [1]

Signs That Foot Pain May Be Related to Limited Ankle Dorsiflexion

No single symptom confirms ankle equinus contracture, but certain patterns can raise suspicion.

These include:

  • Persistent calf tightness.
  • Difficulty performing a squat without the heels lifting.
  • Heel lifting unusually early while walking.
  • Walking on the toes.
  • Frequently standing with the heels elevated.
  • Difficulty walking uphill.
  • Difficulty descending stairs comfortably.
  • Recurrent plantar fasciitis.
  • Recurrent Achilles tendon pain.
  • Pain under the ball of the foot.
  • Thick calluses beneath the forefoot.
  • One ankle feeling noticeably stiffer than the other.
  • A foot that turns outward when walking.
  • Difficulty moving the knee forward over the toes while keeping the heel down.

Some people have no calf discomfort at all. Their first sign may be pain elsewhere in the foot.

A Simple Way to Notice Limited Ankle Dorsiflexion

A common functional movement used to observe ankle dorsiflexion is a knee-to-wall type movement.

Facing a wall, keep the entire foot flat and slowly move the knee forward toward the wall without allowing the heel to lift.

If one side moves considerably less than the other, or if the heel repeatedly lifts very early, ankle dorsiflexion may be limited.

This is only a screening observation, not a diagnosis.

Range of motion can be affected by calf tightness, ankle arthritis, previous fracture, joint impingement, pain, foot position, and testing technique. A formal examination can help determine what is actually blocking movement.

How Doctors Determine What Is Causing Ankle Equinus

One of the most useful clinical assessments is the Silfverskiöld test.

The examiner checks ankle dorsiflexion with the knee straight and then checks it again with the knee bent.

Why bend the knee?

Because the gastrocnemius crosses the knee joint.

When the knee bends, tension on the gastrocnemius decreases.

If ankle dorsiflexion improves substantially when the knee is bent, isolated gastrocnemius tightness is likely contributing to the restriction.

If dorsiflexion remains restricted with both the knee straight and bent, the limitation may involve the soleus, Achilles tendon, ankle joint, or another structure. [1]

This distinction can influence treatment.

Common Causes of Limited Ankle Dorsiflexion

Not every stiff ankle comes from the same problem.

Possible causes include:

Gastrocnemius Tightness

This is a common muscular cause of limited dorsiflexion, particularly when restriction is greater with the knee straight.

Gastrocnemius-Soleus Contracture

When both major calf muscles are involved, restriction may persist even when the knee bends.

Achilles Tendon Tightness

Shortening of the Achilles tendon can physically limit upward ankle movement.

Previous Immobilization

A period in a cast, walking boot, or prolonged bed rest can allow soft tissues to shorten.

Previous Ankle Injury

Fractures, severe sprains, scar tissue, and joint damage may leave the ankle stiff long after the original injury heals.

Ankle Arthritis or Bone Impingement

Sometimes the problem is not the calf at all.

Arthritis or bone spurs at the front of the ankle can create a mechanical block to dorsiflexion.

Neurological Conditions

Abnormal muscle tone or spasticity can pull the foot downward and produce equinus.

This is especially important in conditions such as cerebral palsy and certain neurological disorders.

How Is Ankle Equinus-Related Foot Pain Treated?

Treatment should be directed at both the painful condition and the reason ankle movement is restricted.

Simply stretching every stiff ankle is not enough.

A treatment plan may include several of the following.

Gastrocnemius and Soleus Stretching

When calf muscle tightness is responsible for limited dorsiflexion, stretching may help.

A gastrocnemius stretch is generally performed with the knee straight.

A soleus-focused stretch is generally performed with the knee bent.

The heel usually remains supported on the floor while the ankle moves gradually into dorsiflexion.

Consistency matters more than forcing the ankle aggressively.

It is also important to recognize that stretching does not work equally well in every population. For example, a randomized trial involving adults with diabetes and ankle equinus found that an eight-week static calf stretching program did not significantly improve ankle dorsiflexion or reduce plantar pressure. [11]

That finding is a useful reminder that a longstanding contracture may not behave like ordinary muscle tightness.

Plantar Fascia-Specific Stretching for Heel Pain

When plantar fasciitis is present, treatment should not focus only on the calf.

Plantar fascia-specific stretching can be useful.

Research comparing plantar fascia-specific stretching with traditional Achilles tendon stretching found better early outcomes with the tissue-specific plantar fascia program in patients with chronic plantar fasciitis. Longer-term follow-up also demonstrated substantial improvement after use of the plantar fascia stretching protocol. [12]

Current guidelines therefore support both plantar fascia-specific stretching and calf stretching rather than treating these as mutually exclusive approaches. [7]

Strengthening the Foot and Calf

Flexibility is only one part of normal foot function.

Weakness may also affect how the foot absorbs and transfers force.

Rehabilitation may therefore include:

  • Calf raises.
  • Progressive resistance exercises.
  • Foot intrinsic muscle strengthening.
  • Balance exercises.
  • Controlled single-leg exercises.
  • Gait retraining.
  • Gradual return to walking or running.

For plantar fasciitis, current clinical guidance supports resistance training for the foot and ankle musculature as part of treatment. [7]

Achilles Tendon Loading Exercises

For Achilles tendinopathy, strengthening becomes particularly important.

Modern rehabilitation is no longer based on the idea that an irritated tendon simply needs prolonged rest.

The 2024 clinical practice guideline for midportion Achilles tendinopathy recommends tendon-loading exercise as first-line treatment, using progressively challenging loads that the patient can tolerate. Complete rest is generally not recommended; activity is instead adjusted according to symptoms and tendon tolerance. [10]

Programs may use eccentric, concentric-eccentric, heavy slow resistance, or other progressive loading strategies depending on the individual.

The goal is to restore the tendon’s ability to tolerate load—not merely to make the ankle more flexible.

Manual Therapy and Ankle Mobility Work

Some people have restrictions involving the ankle joint as well as the calf.

Physical therapy may include mobilization of appropriate joints and soft tissues when clinically indicated.

For plantar heel pain, the 2023 clinical practice guideline recommends manual therapy directed at relevant joints and soft tissues to address mobility and flexibility restrictions as part of a broader treatment program. [7]

Footwear and Heel Lifts

Footwear can temporarily change how much dorsiflexion is required during walking.

A shoe with a modest heel-to-toe difference or a temporary heel lift may reduce strain through a tight calf-Achilles complex.

This can occasionally be useful when Achilles tendon symptoms are irritated by dorsiflexion.

The 2024 Achilles tendon guideline allows heel lifts as a therapeutic option to temporarily reduce ankle dorsiflexion during activity in people with midportion Achilles tendinopathy. [10]

A heel lift should not automatically be viewed as a permanent correction for ankle equinus. It may relieve stress while rehabilitation addresses the underlying problem.

Can Orthotics Help Ankle Equinus-Related Foot Pain?

Orthotics can sometimes help redistribute pressure or manage excessive compensatory foot motion.

They may be useful when limited ankle movement is accompanied by:

  • Plantar heel pain.
  • Excessive pronation.
  • Forefoot overload.
  • Certain arch-related problems.

However, an orthotic does not lengthen a contracted gastrocnemius or Achilles tendon.

For plantar fasciitis specifically, current guidelines advise against using either custom or prefabricated orthoses as the sole treatment for short-term pain. They may be used as part of a combined treatment program. [7]

When Is Gastrocnemius Recession Considered?

Surgery is not the first treatment for ordinary calf tightness.

However, a gastrocnemius recession may be considered when there is a confirmed gastrocnemius contracture, symptoms remain significant, and appropriate conservative treatment has failed.

The operation lengthens part of the gastrocnemius muscle-tendon unit, allowing greater ankle dorsiflexion.

It has been studied particularly in persistent plantar fasciitis associated with gastrocnemius contracture.

A 2026 systematic review and meta-analysis of randomized controlled trials found that gastrocnemius recession improved pain, foot function, and ankle dorsiflexion in selected patients with recalcitrant plantar fasciitis. [13]

Earlier systematic review evidence also reported improvement in patients with plantar fasciitis and gastrocnemius contracture who had not responded to conservative care. [14]

Gastrocnemius Recession for Achilles Tendinopathy

Gastrocnemius recession has also been investigated for persistent Achilles tendinopathy in people with gastrocnemius contracture.

Systematic reviews suggest that selected patients may experience improvements in pain, function, and ankle range of motion after surgery. However, the evidence is lower quality than the evidence supporting exercise-based rehabilitation, and reductions in ankle strength have been reported. [15]

For that reason, surgery is generally considered only after an adequate nonsurgical program has failed.

Why Treating Only the Painful Spot May Not Be Enough

This is perhaps the most useful lesson from ankle equinus.

Where you feel pain is not always where the mechanical problem begins.

A person may rub the bottom of the heel every morning, replace shoe inserts repeatedly, and treat the plantar fascia for months while never examining ankle movement.

Another may repeatedly treat the Achilles tendon without realizing that one calf is substantially tighter than the other.

A third person may complain only of pain under the ball of the foot.

The goal is not to blame every foot problem on limited dorsiflexion. It is to make sure ankle motion is not ignored when symptoms keep returning.

A thorough assessment asks two separate questions:

What tissue hurts?

and

Why is that tissue being overloaded?

Those are not always the same question.

When Should Foot Pain and Ankle Stiffness Be Evaluated?

Consider a professional evaluation when:

  • Heel pain persists for several weeks.
  • Plantar fasciitis repeatedly returns.
  • Achilles tendon pain is worsening.
  • Ankle motion is noticeably different from side to side.
  • You cannot comfortably squat while keeping the heels down.
  • You routinely walk on your toes.
  • Your heel lifts unusually early when walking.
  • Forefoot calluses repeatedly return.
  • Foot pain interferes with work, exercise, or normal walking.
  • Ankle stiffness developed after fracture, surgery, or immobilization.
  • There is progressive weakness or difficulty walking.

People with diabetes and neuropathy should be particularly cautious about persistent calluses, pressure areas, skin breakdown, or foot deformity because reduced sensation can allow tissue damage to progress without substantial pain.

Frequently Asked Questions About Ankle Equinus and Foot Pain

Can tight calves really cause plantar fasciitis?

Tight calf muscles and limited ankle dorsiflexion are strongly associated with plantar fasciitis, and gastrocnemius tightness may increase mechanical stress through the plantar fascia. However, plantar fasciitis has multiple contributing factors, so calf tightness should be considered one potential factor rather than the sole cause.

Can limited ankle dorsiflexion cause Achilles tendon pain?

Limited dorsiflexion has been associated with Achilles tendinopathy, and prospective studies suggest it may contribute to risk in some physically active populations. It is not the only risk factor, however. Training load, previous tendon problems, calf strength, recovery, and individual biomechanics also matter.

Why does my heel lift when I squat?

Early heel lifting may occur because the ankle cannot dorsiflex far enough to allow the knees and body to move forward while the foot remains flat. Calf tightness is one possible cause, but ankle joint restriction or structural impingement can produce a similar pattern.

Will stretching my calves cure plantar fasciitis?

Not necessarily. Calf stretching may be appropriate when gastrocnemius or soleus tightness is present, but plantar fasciitis usually responds best to a broader program that may include plantar fascia-specific stretching, strengthening, activity modification, manual therapy, footwear changes, taping, or other measures.

Should I stretch an Achilles tendon that hurts?

That depends on the type of Achilles tendon problem and whether dorsiflexion is restricted. Stretching can be useful in selected patients with limited ankle dorsiflexion, but excessive dorsiflexion may aggravate insertional Achilles tendon pain. Progressive tendon loading is generally more central to Achilles tendinopathy rehabilitation than stretching alone. [10]

Can ankle equinus cause pain under the toes or ball of the foot?

It can contribute. When limited dorsiflexion causes the heel to rise early, pressure may shift forward toward the metatarsal heads. This can contribute to forefoot overload in susceptible individuals.

Does ankle equinus always need surgery?

No. Most patients are initially treated conservatively. Surgery is usually reserved for significant contractures associated with persistent symptoms or deformity that have not responded adequately to nonsurgical treatment.

The Bottom Line

A stiff ankle can create problems surprisingly far from the ankle itself.

With ankle equinus contracture, limited dorsiflexion makes it more difficult for the shin to move normally over the foot during walking. The body adapts by finding movement elsewhere—lifting the heel early, altering foot position, changing stride mechanics, or shifting pressure toward other structures.

Those adaptations are often effective enough to keep a person walking, but they are not always free of consequences.

For some people, the extra mechanical demand shows up as plantar heel pain. In others, the Achilles tendon becomes symptomatic. Still others develop forefoot pressure, metatarsalgia, calluses, or a vague sense that the foot becomes tired much sooner than it should.

The evidence is particularly compelling for the relationship between limited ankle dorsiflexion and plantar fasciitis. In one prospective study, more than four out of five people with plantar fasciitis demonstrated restricted dorsiflexion. Prospective research has also linked reduced ankle dorsiflexion with subsequent Achilles tendinopathy in some active populations.

But ankle equinus should not become a catch-all explanation for every painful foot.

Plantar fasciitis, Achilles tendinopathy, and forefoot pain are multifactorial conditions. The most useful question is whether limited ankle movement is contributing to the load experienced by the painful tissue in a particular person.

When it is, treatment may involve restoring calf and ankle mobility, strengthening the foot and lower leg, modifying activity, improving gait mechanics, and directly rehabilitating the painful structure. Persistent contractures occasionally require surgical lengthening, but most people begin with conservative management.

If heel pain or Achilles tendon pain keeps coming back despite treating the painful area, it may be worth looking a little higher.

Sometimes the foot hurts because the ankle is not moving enough.

References:

  1. Baumbach SF, et al. Diagnosis of Musculus Gastrocnemius Tightness – Key Factors for the Clinical Examination. Discusses limited ankle dorsiflexion, gait changes, gastrocnemius tightness, and associated foot and ankle disorders. (PubMed Central (PMC))
  2. Searle A, Spink MJ, Ho A, Chuter VH. Association Between Ankle Equinus and Plantar Pressures in People With Diabetes: A Systematic Review and Meta-analysis. Clinical Biomechanics. 2017;43:8-14. (PubMed)
  3. Lavery LA, et al. Ankle Equinus Deformity and Its Relationship to High Plantar Pressure in a Large Population With Diabetes Mellitus. Journal of the American Podiatric Medical Association. (PubMed)
  4. Patel A, DiGiovanni B. Association Between Plantar Fasciitis and Isolated Contracture of the Gastrocnemius. Foot & Ankle International. 2011. (PubMed)
  5. Snow SW, Bohne WH, DiCarlo E, Chang VK. Anatomy of the Achilles Tendon and Plantar Fascia in Relation to the Calcaneus in Various Age Groups. Foot & Ankle International. 1995;16(7):418-421; Zwirner J, et al. An Ossifying Bridge—On the Structural Continuity Between the Achilles Tendon and the Plantar Fascia. Scientific Reports. 2020. (PubMed)
  6. Monteagudo M, et al. Plantar Fasciopathy: A Current Concepts Review. Review of gastrocnemius tightness, ankle dorsiflexion, and plantar fascia biomechanics. (PubMed Central (PMC))
  7. Koc TA Jr, et al. Heel Pain—Plantar Fasciitis: Revision 2023. Clinical Practice Guidelines. Journal of Orthopaedic & Sports Physical Therapy. 2023;53(12). (DOI)
  8. Rabin A, et al. Limited Ankle Dorsiflexion Increases the Risk for Mid-portion Achilles Tendinopathy in Infantry Recruits: A Prospective Cohort Study. (PubMed)
  9. Preinjury Knee and Ankle Mechanics During Running Are Reduced Among Collegiate Runners Who Develop Achilles Tendinopathy. Medicine & Science in Sports & Exercise. 2023. (PubMed)
  10. Chimenti RL, et al. Achilles Pain, Stiffness, and Muscle Power Deficits: Midportion Achilles Tendinopathy Revision—2024. Clinical Practice Guidelines. Journal of Orthopaedic & Sports Physical Therapy. 2024;54(12). (PubMed)
  11. Searle A, et al. Calf Muscle Stretching Is Ineffective in Increasing Ankle Range of Motion or Reducing Plantar Pressures in People With Diabetes and Ankle Equinus: A Randomised Controlled Trial. Clinical Biomechanics. 2019. (PubMed)
  12. DiGiovanni BF, et al. Tissue-Specific Plantar Fascia-Stretching Exercise Enhances Outcomes in Patients With Chronic Heel Pain and subsequent two-year follow-up study. (PubMed)
  13. Pérez González A, et al. Gastrocnemius Recession in Recalcitrant Plantar Fasciitis: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Journal of Clinical Medicine. 2026. (PubMed)
  14. Arshad Z, Aslam A, Razzaq MA, Bhatia M. Gastrocnemius Release in the Management of Chronic Plantar Fasciitis: A Systematic Review. Foot & Ankle International. 2022. (PubMed)
  15. Arshad Z, et al. Gastrocnemius Release Is an Effective Management Option for Achilles Tendinopathy: A Systematic Review; White CJ, et al. Gastrocnemius Release in the Treatment of Achilles Tendinopathy: A Systematic Review. (PubMed Central (PMC))

When a Tight Calf Changes the Way You Walk: Understanding Ankle Equinus Contracture

A tight calf may seem like a relatively minor problem. But when tightness prevents the ankle from bending upward normally, the effects can travel well beyond the calf itself.

This loss of ankle movement is known as ankle equinus contracture. It can change the way a person stands, walks, climbs stairs, runs, or distributes weight across the foot. In some people, ankle equinus causes obvious toe walking. In others, the condition is much less noticeable and first shows up as recurring heel pain, forefoot pain, Achilles tendon discomfort, or difficulty performing activities that require the knee to move forward over the foot.

Ankle equinus can occur in children and adults and may develop because of tight calf muscles, shortening of the Achilles tendon, prolonged immobilization, neurological disorders, trauma, or structural problems within the ankle itself. Treatment depends on what is actually restricting movement and can range from stretching and physical therapy to bracing, serial casting, or surgery.

Understanding the cause is important because simply treating the painful part of the foot may not correct the underlying biomechanical problem.

What Is Ankle Equinus Contracture?

Ankle equinus describes a condition in which upward movement of the ankle toward the shin, called dorsiflexion, is restricted.

During normal walking, the ankle must dorsiflex sufficiently as the body moves forward over the planted foot. When this movement is limited, the body usually finds another way to keep moving.

A person may:

  • Lift the heel earlier than normal while walking.
  • Walk partly on the toes.
  • Turn the foot outward.
  • Allow the arch of the foot to collapse excessively.
  • Place additional pressure on the ball of the foot.
  • Alter movement at the knee, hip, or lower back.

There is no universally accepted single measurement that defines ankle equinus. Less than approximately 10 degrees of ankle dorsiflexion has frequently been used in clinical literature, although the exact threshold varies among studies and depends partly on how the ankle is examined. [1,2]

The word contracture is generally used when the muscles, tendons, joint structures, or other soft tissues have become sufficiently tight that normal range of motion is restricted.

Why Is Ankle Dorsiflexion So Important?

Ankle dorsiflexion is the movement that occurs when the top of the foot comes closer to the shin.

Try keeping your heel flat on the ground while moving your knee forward over your toes. That movement requires ankle dorsiflexion.

It occurs repeatedly during:

  • Walking
  • Running
  • Squatting
  • Going downstairs
  • Climbing stairs
  • Getting up from a chair
  • Lunging
  • Playing sports

When the ankle cannot move normally, the body compensates.

One common compensation is an early heel rise. Instead of the heel staying on the ground while the body passes over the foot, it lifts prematurely. This shifts pressure toward the front of the foot.

Research has associated reduced ankle dorsiflexion with altered gait and increased pressure beneath the forefoot. [2]

This is why ankle equinus contracture may sometimes produce symptoms somewhere other than the ankle.

What Causes Ankle Equinus Contracture?

There is no single cause. Several different problems can produce the same basic result: the ankle cannot dorsiflex normally.

1. Tight Gastrocnemius Muscle

The gastrocnemius is the large calf muscle visible at the back of the lower leg.

It begins above the knee and joins the soleus muscle before eventually connecting to the heel through the Achilles tendon.

Because the gastrocnemius crosses both the knee and ankle joints, its tension changes depending on whether the knee is straight or bent.

An isolated gastrocnemius contracture is one of the most common causes of limited ankle dorsiflexion.

A person may have adequate ankle movement when the knee is bent but considerably less movement when the knee is straight.

This distinction is important because it can influence treatment.

2. Tight Gastrocnemius-Soleus Complex

Sometimes the restriction is not limited to the gastrocnemius.

The deeper soleus muscle and other components of the calf-Achilles complex may also be shortened. When ankle dorsiflexion remains restricted even after the knee is bent, clinicians may suspect a broader gastrocnemius-soleus or Achilles tendon contracture. [1]

3. Achilles Tendon Tightness

A shortened or tight Achilles tendon can hold the ankle in a more downward-pointing position.

Achilles tendon tightness may develop gradually or occur in association with neuromuscular conditions, prolonged positioning, previous injury, or other foot and ankle disorders.

4. Prolonged Immobilization

Keeping the ankle in one position for a prolonged period can allow muscles and soft tissues to shorten.

This can occur after:

  • A fracture
  • Major ankle surgery
  • Casting
  • Severe foot injuries
  • Extended bed rest
  • Prolonged use of certain immobilization devices

Immobilization with the foot pointing downward is particularly capable of encouraging shortening of the gastrocnemius-soleus-Achilles complex. [1]

5. Neurological and Neuromuscular Conditions

Some forms of ankle equinus are caused by abnormal muscle tone rather than ordinary muscle tightness.

Conditions affecting the brain, spinal cord, peripheral nerves, or muscular system may create an imbalance between muscles that lift and lower the foot.

Cerebral palsy is an important example. Increased muscle tone and spasticity of the calf can pull the ankle into equinus and contribute to toe walking.

Other neurological disorders may also alter muscle strength, tone, and coordination.

6. Idiopathic Toe Walking in Children

Some children consistently walk on their toes even though no neurological, orthopedic, or developmental explanation is found.

This is referred to as idiopathic toe walking.

Persistent toe walking and calf tightness can eventually contribute to loss of ankle dorsiflexion in some children.

However, toe walking should not automatically be assumed to be harmless. A clinician may need to exclude neurological, muscular, developmental, or structural causes before labeling it idiopathic.

7. Trauma or Previous Ankle Injury

Fractures, severe ankle sprains, scar formation, and post-traumatic arthritis may restrict ankle movement.

In some patients, the problem is primarily soft-tissue tightness. In others, bone or joint changes create a mechanical block that physically prevents the ankle from moving farther.

8. Arthritis and Ankle Impingement

Degenerative changes within the ankle can cause stiffness and loss of dorsiflexion.

Bone spurs or other structural abnormalities at the front of the ankle may create anterior ankle impingement, meaning the bones come into contact during upward ankle movement and limit further motion. [1]

Stretching alone is unlikely to correct a true bony block, which is why identifying the source of restricted movement matters.

9. Diabetes and Related Foot Problems

People with diabetes may develop changes in joint mobility, peripheral nerves, tendons, and soft tissues that contribute to limited ankle dorsiflexion.

Reduced dorsiflexion has particular significance in people with diabetes because equinus can increase pressure under the foot.

A systematic review found an association between ankle equinus and increased plantar pressures in people with diabetes. Elevated plantar pressure is clinically important in patients who also have neuropathy because they may not feel repetitive stress or developing wounds normally. [3]

Symptoms of Ankle Equinus Contracture

Ankle equinus does not always produce pain directly.

Some people discover it during an examination for an entirely different foot problem.

When symptoms occur, they may include:

  • Tightness in the calf.
  • Difficulty bringing the foot upward toward the shin.
  • Difficulty keeping the heel down during a squat.
  • Early heel lifting while walking.
  • Toe walking.
  • Reduced stride length.
  • Difficulty walking uphill.
  • Difficulty descending stairs.
  • Pain or fatigue after prolonged walking.
  • Pain in the heel or arch.
  • Pain beneath the ball of the foot.
  • Achilles tendon discomfort.
  • Recurrent calluses beneath the forefoot.
  • A sensation that the ankle is stiff or blocked.

Children may be brought for evaluation because parents notice persistent toe walking rather than because the child complains of pain.

Can Ankle Equinus Cause Foot Pain?

Yes, although the relationship is not as simple as saying that ankle equinus always causes a particular foot disorder.

Restricted ankle dorsiflexion changes how forces pass through the lower limb.

When the ankle cannot bend adequately, the heel may rise early and pressure can shift toward the midfoot and forefoot. The foot may also compensate by pronating, or rolling inward, to obtain additional functional movement.

Gastrocnemius contracture and restricted dorsiflexion have been associated with a variety of foot and ankle problems, including plantar fasciitis, metatarsalgia, Achilles tendon pain, flatfoot deformity, midfoot problems, and forefoot overload. [4]

This does not mean everyone with one of these conditions has ankle equinus. It means ankle mobility should be considered as part of a complete biomechanical examination.

Ankle Equinus and Plantar Fasciitis

The association between calf tightness, limited ankle dorsiflexion, and plantar heel pain has received considerable attention.

When the calf is tight, forward movement of the shin over the foot becomes restricted. The foot may compensate in ways that increase stress on the plantar fascia.

In one prospective study involving 254 patients with plantar fasciitis, 83 percent had limited ankle dorsiflexion. More than half had an isolated gastrocnemius contracture. [5]

This does not prove that equinus is responsible for every case of plantar fasciitis, but it explains why clinicians often examine calf flexibility when evaluating persistent heel pain.

Ankle Equinus and Forefoot Pain

The ball of the foot can also become overloaded.

An early heel rise transfers weight forward before it normally should. Over time, this may contribute to:

  • Metatarsalgia.
  • Pain beneath the metatarsal heads.
  • Callus formation.
  • Stress-related forefoot symptoms.
  • Aggravation of certain toe deformities.

Someone seeking treatment only for forefoot pain may therefore have an underlying ankle restriction that needs to be addressed.

How Is Ankle Equinus Contracture Diagnosed?

Diagnosis usually begins with a detailed history and physical examination.

The clinician may ask about:

  • When symptoms began.
  • Previous fractures or ankle injuries.
  • Previous surgery.
  • Casting or immobilization.
  • Childhood toe walking.
  • Neurological disorders.
  • Diabetes.
  • Changes in walking.
  • Location of foot or ankle pain.
  • Activities that worsen symptoms.

The examination may include the entire lower extremity rather than focusing only on the ankle.

The clinician may evaluate:

  • Walking pattern.
  • Foot alignment.
  • Calf tightness.
  • Achilles tendon.
  • Ankle range of motion.
  • Knee and hip movement.
  • Muscle strength.
  • Reflexes and sensation when appropriate.
  • Areas of abnormal pressure or callus formation.

Measuring Ankle Dorsiflexion

Ankle dorsiflexion is generally checked with both the knee straight and the knee bent.

This seemingly small difference provides important information because the gastrocnemius crosses the knee while the soleus does not.

What Is the Silfverskiöld Test?

The Silfverskiöld test is commonly used to help determine which structures are responsible for an equinus contracture.

The examiner assesses ankle dorsiflexion with the knee straight and then repeats the examination with the knee bent.

If ankle dorsiflexion improves substantially when the knee bends, isolated gastrocnemius tightness is more likely.

If movement remains restricted even when the knee is bent, the restriction may involve the soleus, Achilles tendon, joint, or other structures. [1]

Correct positioning of the foot is important during this examination because movement through the midfoot can sometimes make ankle dorsiflexion appear greater than it actually is.

Are X-Rays or Magnetic Resonance Imaging Needed?

Not everyone with ankle equinus needs imaging.

When the physical examination strongly suggests muscular tightness without other concerning findings, imaging may add little.

An X-ray may be appropriate when the clinician suspects:

  • Previous fracture deformity.
  • Arthritis.
  • Bone spurs.
  • Anterior ankle impingement.
  • Other structural abnormalities.

Magnetic resonance imaging may occasionally be considered when soft-tissue abnormalities, neurological problems, or other pathology is suspected.

Children with unexplained toe walking and abnormal neurological findings may require additional neurological evaluation rather than simply being treated for tight calf muscles. [1]

Treatment Options for Ankle Equinus Contracture

Treatment should address both the equinus contracture and any condition contributing to it.

A person with mild calf tightness will not necessarily require the same treatment as someone with severe spastic equinus from a neurological disorder or a rigid ankle blocked by arthritis.

Whenever possible, treatment starts conservatively.

Calf Stretching for Ankle Equinus

Stretching is one of the most commonly recommended treatments for muscular ankle equinus.

A typical calf stretch may be performed with the affected leg behind the body while the heel remains on the floor.

Stretching with the knee straight emphasizes the gastrocnemius.

Stretching with the knee slightly bent places relatively greater emphasis on the soleus and deeper calf structures.

However, patients should not assume that aggressive stretching is always better. The appropriate technique depends on what is actually restricting movement.

Systematic reviews have found that calf stretching can increase ankle dorsiflexion, although the magnitude of improvement varies and may be modest. [6]

People with substantial contractures, neurological conditions, diabetes-related foot complications, recent surgery, or significant pain should obtain individualized guidance rather than repeatedly forcing the ankle into dorsiflexion.

Physical Therapy for Limited Ankle Dorsiflexion

Physical therapy may combine stretching with other interventions rather than treating the calf in isolation.

A rehabilitation program may include:

  • Gastrocnemius stretching.
  • Soleus stretching.
  • Ankle mobility exercises.
  • Strengthening of muscles that lift the foot.
  • Foot and ankle strengthening.
  • Balance exercises.
  • Gait retraining.
  • Functional movement training.
  • Progressive return to activity.

The therapist may also look at how the hip, knee, ankle, and foot interact during walking.

This is especially useful when years of restricted ankle movement have created compensatory movement patterns.

Footwear, Heel Lifts, and Orthotics

Footwear modifications may reduce symptoms while the underlying restriction is being treated.

Depending on the individual, a clinician may recommend:

  • Supportive footwear.
  • Temporary heel lifts.
  • Custom or prefabricated orthotics.
  • Ankle-foot orthoses.
  • Pressure-relieving footwear.

A heel lift can reduce tension through a tight calf-Achilles complex, but it does not necessarily correct the contracture itself.

Orthotics may help manage excessive pronation or redistribute pressure, particularly when equinus is contributing to symptoms elsewhere in the foot.

Serial Casting

Serial casting is used more commonly in children and in selected patients with neurological or substantial contractures.

The ankle is placed in a controlled stretched position using a cast. The process is repeated over time, gradually increasing dorsiflexion.

Physical therapy is often required afterward to maintain mobility and restore strength.

Casting should be medically supervised because excessive or poorly controlled stretching can lead to skin problems, pressure injury, weakness, or other complications.

Treatment of Spastic Ankle Equinus

When equinus results from abnormal muscle tone, such as spasticity associated with cerebral palsy or another neurological disorder, treatment may differ substantially from ordinary calf stretching.

Management may include:

  • Physical therapy.
  • Bracing.
  • Serial casting.
  • Medication for spasticity.
  • Botulinum toxin injections in selected patients.
  • Surgical lengthening when appropriate.

Treatment decisions usually involve assessment of the entire gait pattern because excessive correction can also create functional problems.

When Is Surgery Considered for Ankle Equinus Contracture?

Most people with mild ankle equinus do not immediately need surgery.

Surgery may be considered when:

  • The contracture is substantial.
  • Pain or functional limitations persist.
  • Appropriate conservative treatment has failed.
  • The equinus is contributing to another foot deformity.
  • Recurrent pressure problems continue.
  • The restriction significantly interferes with walking.
  • A fixed soft-tissue contracture cannot be adequately corrected nonoperatively.

The surgical procedure depends on the structure causing the restriction.

Gastrocnemius Recession

A gastrocnemius recession lengthens part of the gastrocnemius muscle-tendon unit.

It is generally considered when isolated gastrocnemius tightness is confirmed and the restriction improves when the knee is bent.

Different surgical techniques can be used, but their shared goal is to reduce gastrocnemius tension and improve ankle dorsiflexion without unnecessarily lengthening the entire Achilles tendon.

Gastrocnemius recession is also sometimes performed as part of treatment for another condition, such as selected cases of flatfoot deformity or persistent plantar heel pain associated with gastrocnemius contracture. [7]

Achilles Tendon Lengthening

When the restriction involves the broader gastrocnemius-soleus-Achilles complex rather than the gastrocnemius alone, Achilles tendon lengthening may be considered.

Lengthening the tendon can substantially improve dorsiflexion, but excessive lengthening must be avoided.

The calf muscles and Achilles tendon provide much of the power needed to push the body forward during walking. Over-lengthening may therefore cause weakness, difficulty with push-off, or an altered gait.

This is one reason why accurately distinguishing isolated gastrocnemius contracture from a more extensive contracture is important before surgery. [8]

Recovery After Ankle Equinus Surgery

Recovery depends on the procedure performed and whether another foot or ankle operation is done at the same time.

Treatment after surgery may involve:

  • Temporary activity restrictions.
  • A walking boot or brace.
  • Gradual weight-bearing.
  • Stretching.
  • Range-of-motion exercises.
  • Calf strengthening.
  • Gait training.
  • Progressive return to work and recreational activity.

Patients should follow their surgeon’s rehabilitation instructions rather than attempting to rapidly regain flexibility on their own.

Restoring dorsiflexion is only one part of recovery. Strength and control of the calf are also important for normal walking.

Can Ankle Equinus Contracture Come Back?

Recurrence is possible, particularly when the underlying cause remains present.

Risk may be higher when equinus is related to:

  • Neurological spasticity.
  • Progressive neuromuscular disease.
  • Persistent toe walking.
  • Inadequate rehabilitation.
  • Long-term inactivity.
  • Repeated immobilization.

Following a stretching and strengthening program as recommended may help preserve ankle mobility after treatment.

Can Ankle Equinus Contracture Be Prevented?

Not every case is preventable, especially when equinus is caused by congenital, neurological, or structural conditions.

However, maintaining ankle mobility may reduce the likelihood of acquired calf tightness in some people.

Helpful measures can include:

  • Remaining physically active.
  • Regularly moving the ankle through a comfortable range of motion.
  • Addressing prolonged calf tightness early.
  • Following rehabilitation after ankle injury or surgery.
  • Avoiding unnecessary prolonged immobilization.
  • Wearing appropriate footwear.
  • Seeking evaluation for persistent toe walking in children.

People recovering from a fracture, surgery, neurological event, or prolonged hospitalization may benefit from early rehabilitation aimed at maintaining joint mobility.

When Should You See a Doctor for Limited Ankle Dorsiflexion?

Occasional calf tightness after exercise does not necessarily indicate ankle equinus contracture.

Medical evaluation is worth considering when you notice:

  • Persistent inability to bring the ankle upward.
  • Toe walking.
  • One ankle moving considerably less than the other.
  • Recurrent heel or forefoot pain.
  • Increasing Achilles tendon pain.
  • Difficulty squatting with the heel on the floor.
  • Progressive foot deformity.
  • Recurrent pressure sores or calluses.
  • New walking difficulty.
  • Ankle stiffness after a fracture or surgery.

Children who continue to toe walk should also be assessed when the pattern is persistent, worsening, asymmetric, or accompanied by weakness, developmental concerns, balance problems, or other neurological symptoms.

Frequently Asked Questions About Ankle Equinus Contracture

Is ankle equinus the same as a tight Achilles tendon?

Not necessarily.

A tight Achilles tendon can cause equinus, but the restriction may instead come primarily from the gastrocnemius muscle, the combined gastrocnemius-soleus complex, the ankle joint, bone, scar tissue, or a neurological disorder.

How do I know whether my calves are causing limited ankle dorsiflexion?

A clinician can compare ankle movement with the knee straight and bent. Improvement with knee flexion may indicate that the gastrocnemius is a major contributor.

Can ankle equinus cause plantar fasciitis?

Restricted ankle dorsiflexion and gastrocnemius tightness are strongly associated with plantar fasciitis, but plantar fasciitis has multiple possible contributing factors. Ankle equinus should therefore be viewed as one potentially important biomechanical factor rather than the explanation for every case of heel pain. [5]

Can stretching fix ankle equinus?

Mild muscular tightness may improve with consistent stretching and physical therapy. A fixed contracture, neurological equinus, or restriction caused by bone or severe arthritis may require other treatment.

Does ankle equinus always cause toe walking?

No. Toe walking is one possible presentation, particularly in children, but many adults with restricted dorsiflexion continue to walk with their heels on the ground by compensating elsewhere in the foot and lower limb.

Is ankle equinus permanent?

Not always.

The outlook depends on the cause and severity. Flexible muscular tightness may respond well to conservative treatment, while long-standing fixed contractures may be more difficult to reverse without surgery.

The Bottom Line

Ankle equinus contracture is more than simply having tight calf muscles.

When the ankle cannot dorsiflex normally, the body must compensate every time a person takes a step. Some people respond by walking on their toes. Others develop an early heel rise, increased forefoot pressure, excessive foot pronation, or altered movement higher in the leg.

Over time, these mechanics may contribute to heel pain, Achilles tendon symptoms, forefoot overload, calluses, flatfoot-related problems, and difficulty performing everyday activities.

The key to effective treatment is identifying why the ankle is tight.

An isolated gastrocnemius contracture may respond to targeted stretching and physical therapy and, in resistant cases, gastrocnemius recession. A broader Achilles or gastrocnemius-soleus contracture may require a different approach. Bone or joint restrictions must be distinguished from muscle tightness, while neurological equinus requires assessment of muscle tone and the overall gait pattern.

For that reason, persistent limited ankle dorsiflexion should not simply be treated as a flexibility problem. A proper foot and ankle examination can identify the source of the restriction and help determine whether exercises, orthotics, rehabilitation, casting, treatment of an underlying condition, or surgery offers the most appropriate path toward restoring comfortable movement.

References:

  1. Robinson JM, Mielke CH. Ankle Equinus. StatPearls Publishing; updated August 16, 2024.
  2. Charles J, Scutter SD, Buckley J. Static ankle joint equinus: toward a standard definition and diagnosis. Journal of the American Podiatric Medical Association. 2010;100(3):195-203.
  3. Searle A, Spink MJ, Ho A, Chuter VH. Association between ankle equinus and plantar pressures in people with diabetes: A systematic review and meta-analysis. Clinical Biomechanics. 2017;43:8-14.
  4. Cychosz CC, Phisitkul P, Belatti DA, Wukich DK. Literature review addressing foot and ankle pathology associated with gastrocnemius contracture and altered mechanics.
  5. Patel A, DiGiovanni B. Association between plantar fasciitis and isolated contracture of the gastrocnemius. Foot & Ankle International. 2011.
  6. Radford JA, Burns J, Buchbinder R, Landorf KB, Cook C. Does stretching increase ankle dorsiflexion range of motion? A systematic review. British Journal of Sports Medicine. 2006;40(10):870-875.
  7. Arshad Z, Aslam A, Razzaq MA, Bhatia M. Gastrocnemius Release in the Management of Chronic Plantar Fasciitis: A Systematic Review. Foot & Ankle International. 2022;43(4):568-575.
  8. Review of surgical management of gastrocnemius-soleus-Achilles contracture and ankle equinus, including gastrocnemius recession and Achilles tendon lengthening.

Functional Restoration Program: What the Weeks Really Look Like

A functional restoration program is very different from going to physical therapy once or twice a week. For people who have been living with chronic pain, prolonged disability, or difficulty returning to work, it can feel more like going back to school—or even returning to a part-time or full-time job.

Participants may spend several hours a day exercising, learning about chronic pain, working with psychologists and therapists, practicing job-related activities, and gradually rebuilding their tolerance for everyday movement. The emphasis is not simply on making pain disappear. Instead, the goal is to help a person become more active, independent, confident, and capable of returning to normal daily and occupational activities despite persistent symptoms.

That naturally raises several questions: How long is a functional restoration program? How many hours a day does it take? What exercises are performed? Does it hurt? And what happens from the first day to the last?

The answer depends on the program, the patient’s condition, work demands, progress, and the treatment guidelines being followed. However, there are some common patterns.

How Long Does a Functional Restoration Program Last?

Many intensive functional restoration programs last approximately four to six weeks, although there is no single schedule used by every rehabilitation center.

The current American College of Occupational and Environmental Medicine chronic pain guideline incorporated into California’s workers’ compensation Medical Treatment Utilization Schedule describes a functional restoration program timeframe of at least five hours per day for approximately four to six weeks, with a maximum of 160 hours, unless an exception is medically justified.[1]

This four-to-six-week model is also consistent with earlier research. A systematic review of functional restoration programs for chronic low back pain described them as intensive, multidisciplinary programs that commonly ran for a full day over approximately three to six weeks.[2]

But not every modern functional restoration program follows this exact format.

Published programs have included seven-to-eight-week outpatient treatment involving three to four clinical hours a day, usually five days per week.[3] A 2025 study involving people with chronic pain after work-related injuries evaluated an eight-week functional restoration program, while another interdisciplinary chronic musculoskeletal pain program described in the literature lasted 10 weeks and provided 61 hours of treatment.[4,5]

So, a useful answer is:

A functional restoration program often lasts four to eight weeks, but both shorter and longer programs exist. The total number of treatment hours and the intensity of the program may be more meaningful than the number of calendar weeks alone.

A person attending six hours a day, five days a week for four weeks receives a very different amount of rehabilitation from someone attending four hours twice a week for eight weeks.

What Is a Functional Restoration Program?

A functional restoration program is an interdisciplinary rehabilitation program for people with chronic pain and significant loss of function. It is generally considered when conventional treatments have not restored adequate activity, independence, or work capacity.

It may be particularly relevant for someone who has undergone physical therapy, medications, injections or other appropriate treatment but continues to have substantial limitations with walking, lifting, sitting, standing, working, household activities or self-care.

The approach is based on the biopsychosocial model of chronic pain. That means clinicians look at more than the injured body part. Physical deconditioning, fear of movement, sleep problems, stress, mood, coping behaviors, medication use, social circumstances and work demands may all influence recovery.

Current occupational medicine guidance describes functional restoration as both a form of interdisciplinary pain rehabilitation and a broader approach to medical care. Assessment may include strength, sensation, range of motion, physical function, psychological stressors, fear of reinjury, support systems, mood, medication use and work incapacity.[1]

Rather than relying primarily on passive treatments, the team increasingly acts as educators and coaches, helping the patient learn how to manage activity and symptoms independently.[1]

This is one of the most important concepts to understand before starting treatment: functional restoration is designed to restore life and function, not simply to chase a lower pain score.

What Does a Functional Restoration Program Daily Schedule Look Like?

A functional restoration program daily schedule varies considerably between centers. An intensive program may occupy most of the working day, while another may combine several treatment blocks into a shorter day.

A realistic day might look something like the following.

Morning Check-In and Movement Preparation

The day may begin with a short review of symptoms, sleep, medication use and how the person responded to the previous day’s activities.

This is generally not intended to become a lengthy discussion centered entirely on pain. Instead, the rehabilitation team may use the information to determine whether the patient can continue progressing safely.

Warm-up activities may follow. These can include gentle walking, range-of-motion exercises, stretching or low-intensity cardiovascular activity.

Graded Physical Conditioning

A substantial part of the morning may be devoted to physical conditioning.

Instead of exercising only the painful area, treatment often addresses overall physical capacity. Someone who has been inactive for months may have lost cardiovascular endurance, strength, balance, mobility and confidence in movement.

The physical therapist gradually increases activity according to what the person can safely tolerate.

Exercises may initially feel surprisingly basic. Walking for a specific period, repeatedly standing up from a chair or lifting a light object may not sound difficult. For someone who has avoided these activities because of chronic pain, however, rebuilding tolerance can be challenging.

Progression is usually more important than starting intensity.

Occupational Therapy and Functional Activities

Occupational therapy focuses on activities that matter outside the clinic.

Depending on the individual’s needs, this may involve reaching, carrying, bending, pushing, pulling, sitting, standing, walking, handling objects or practicing activities similar to those performed at work.

The therapist may also address body mechanics, pacing, ergonomics and ways of performing household or self-care activities more efficiently.

For an injured worker, this portion of rehabilitation may gradually become increasingly job-specific.

Pain Education and Behavioral Treatment

An important part of the day may have little resemblance to traditional physical therapy.

Participants may attend individual or group sessions addressing chronic pain, stress, sleep, activity avoidance, fear of reinjury, communication, coping strategies and expectations about recovery.

Cognitive behavioral approaches are commonly incorporated into interdisciplinary pain rehabilitation.[1,6]

The goal is not to suggest that pain is imaginary or “all in the head.” Rather, persistent pain is influenced by biological, psychological and social factors, and those factors can affect how a person moves, sleeps, works and responds to symptoms.

Afternoon Conditioning or Work Simulation

After a break, physical activity may resume.

For someone preparing to return to a physically demanding occupation, exercises can increasingly resemble real job requirements. A warehouse worker, construction worker, nurse and office worker obviously require very different functional abilities.

The rehabilitation team may therefore reproduce relevant tasks within a controlled environment and progressively increase duration, repetition or resistance.

Review, Home Exercise and Planning for the Next Day

Before leaving, the patient may review progress and receive exercises or behavioral assignments to practice outside the clinic.

This matters because the ultimate objective is not indefinite supervised therapy. The patient needs to become capable of managing exercise, activity and pain independently.

What Exercises Are Done in a Functional Restoration Program?

There is no standard exercise routine appropriate for every participant. The exercises chosen depend on the injury, current functional capacity, overall health and the physical demands the person eventually needs to meet.

However, several types of exercise frequently appear in functional restoration programs.

Cardiovascular and Aerobic Conditioning

Walking, treadmill training, stationary cycling or other aerobic activities may be used to rebuild endurance.

Long periods of reduced activity can cause significant deconditioning. A person may initially believe pain alone prevents prolonged walking or standing when decreased cardiovascular and muscular endurance is also contributing.

Treatment therefore gradually increases activity rather than waiting for all pain to disappear before exercise begins.

Active exercise and physical conditioning are emphasized in occupational medicine guidance, with the eventual goal of transitioning patients toward sustainable independent activity.[7]

Strengthening Exercises

Strengthening may involve the legs, hips, back, abdomen, shoulders, arms or other regions depending on the patient’s needs.

Resistance can come from body weight, exercise bands, machines, free weights or functional tasks.

The objective is not bodybuilding or achieving maximum strength. Instead, strengthening is directed toward improving the capacity required for daily life and work.

Flexibility and Mobility Exercises

Persistent pain can lead to guarded movement. Over time, a person may move less and become increasingly stiff.

Range-of-motion exercises, stretching and controlled mobility work may be used to gradually restore comfortable movement.

Improvement is generally progressive rather than immediate.

Core and Trunk Conditioning

For people with chronic back pain, exercises may address trunk strength, endurance, coordination and controlled movement.

Rather than relying solely on isolated back exercises, the program may combine trunk conditioning with walking, lifting, squatting, carrying and other functional activities.

Lifting, Carrying, Pushing and Pulling

As rehabilitation progresses, exercises often become more practical.

A participant may practice lifting objects from different heights, carrying loads over a set distance, pushing or pulling weighted equipment, climbing steps or repeatedly moving between sitting and standing.

These activities may be particularly important when the eventual goal is returning to a physical occupation.

Graded Exposure to Feared Movements

Some people with chronic pain develop fear of movement, sometimes called kinesiophobia.

After repeatedly experiencing pain while bending, lifting or walking, they may understandably begin avoiding those activities. Unfortunately, continued avoidance can contribute to further deconditioning and disability.

Graded exposure reintroduces feared movements in manageable steps. The intention is to build confidence and demonstrate that movement can often be increased safely even when some discomfort remains.

Does Exercise in a Functional Restoration Program Cause More Pain?

Temporary increases in soreness or symptoms can occur when activity increases, particularly during the early part of a program.

Someone who has been relatively inactive for months may experience muscular soreness and fatigue when beginning several hours of rehabilitation.

That does not mean every increase in pain should be ignored.

The treatment team should distinguish between an expected response to increased activity and symptoms suggesting that an exercise should be modified or medically reassessed. Programs are generally designed around graded progression, rather than forcing every patient through identical exercise targets.

A pain flare may therefore lead to changes in intensity, duration, technique or pacing rather than automatically stopping all activity.

One of the skills participants often learn is how to respond to a flare without returning to prolonged inactivity.

Why Is Psychology Part of a Functional Restoration Program?

People are sometimes surprised—or even offended—when they learn that psychological treatment is included in a chronic pain rehabilitation program.

It should not be interpreted as a clinician saying that the pain is psychological.

Living with pain for months or years can affect sleep, confidence, relationships, mood and the ability to work. In the opposite direction, anxiety, poor sleep, fear of reinjury, catastrophizing and prolonged stress can make rehabilitation more difficult.

That is why comprehensive programs address both sides of the problem.

Psychological and behavioral sessions may work on coping skills, relaxation, stress regulation, problem solving, sleep habits, goal setting, fear avoidance and strategies for remaining active during pain fluctuations.

Research on interdisciplinary rehabilitation suggests that physical and psychological factors both matter when considering longer-term functioning.[8]

The practical objective is often to change the thought from “I cannot do anything until my pain is gone” to “I can learn how to function safely and progressively even when some pain is present.”

That can represent a major turning point for someone who has been trapped in a cycle of pain, inactivity and further loss of function.

What Happens During the First Week of Functional Restoration?

Before or at the beginning of treatment, the patient usually undergoes a multidisciplinary evaluation.

The team wants to understand where the person is starting—not only medically, but functionally and psychologically.

Physical therapists may assess strength, movement, endurance and activity tolerance. Psychological assessment may look at mood, coping, fear avoidance, expectations and barriers to rehabilitation. The physician reviews diagnosis, medications and medical stability. Occupational or vocational professionals may examine the gap between current abilities and job requirements.

During the first several days, exercise may deliberately begin below the person’s maximum capacity.

This allows the team to establish a reliable baseline.

The first week can also be mentally challenging. Patients who have spent months protecting an injured area are suddenly being encouraged to move more. Some begin treatment expecting the therapists to “fix” the painful area and discover that the program instead requires substantial active participation.

That shift in expectations is part of the rehabilitation process.

What Happens During the Middle Weeks?

Once baseline tolerance is understood, treatment becomes progressively more demanding.

Walking time may increase. Resistance may be added to exercises. A person who initially lifted an object only occasionally may begin performing the task repeatedly. Sitting or standing tolerance may be extended.

At the same time, psychological and educational sessions reinforce strategies for dealing with discomfort, fear, frustration and flare-ups.

Progress does not necessarily occur in a straight line.

A patient may have an excellent Monday, a difficult Tuesday and then improve again later in the week. The treatment team is looking at the overall trend rather than expecting symptoms to improve every day.

This is also when treatment becomes increasingly individualized. If returning to employment is one of the goals, rehabilitation can begin closing the gap between current functional capacity and actual job demands.

Occupational guidelines specifically emphasize evaluating job activities when determining the difference between what a worker can currently do and what the job requires.[1]

What Happens During the Final Weeks of a Functional Restoration Program?

Toward the end of treatment, the focus increasingly shifts from supervised rehabilitation to independence.

Exercise may become more demanding and more closely resemble the participant’s normal daily or occupational activities.

The team may also begin answering practical questions: How much can the person lift? How long can they sit or stand? Can they tolerate repeated activity? What restrictions remain? What exercises should continue at home? How should future pain flare-ups be handled?

For an injured worker, the final plan may address return to full duty, modified duty or another appropriate vocational pathway.

A good discharge plan is therefore more than “treatment completed.”

The patient should leave with a strategy for maintaining the gains made during the program.

Is Functional Restoration the Same as Physical Therapy?

No.

Physical therapy is usually one component of a functional restoration program rather than the entire treatment.

Traditional physical therapy may concentrate primarily on movement, strength, mobility and a particular musculoskeletal problem.

Functional restoration combines physical rehabilitation with several other disciplines. Depending on the program, these may include pain medicine, occupational therapy, psychology, behavioral medicine, nursing, vocational rehabilitation, medication management and education.[6]

The team also communicates about common goals instead of each provider treating a separate issue independently.

This coordinated approach is one reason functional restoration can involve many more treatment hours than ordinary physical therapy.

Functional Restoration vs. Work Conditioning and Work Hardening

These terms are sometimes used interchangeably, but they are not exactly the same.

Work conditioning generally emphasizes physical conditioning and simulated work activities designed to improve strength, endurance and the ability to meet job demands.

Work hardening may add a more structured job-simulation component and some educational or behavioral elements.

A comprehensive functional restoration program goes further by addressing the physical, psychological, medical and social barriers associated with chronic pain and prolonged disability.

The current occupational medicine guideline classifies functional restoration as a more intensive interdisciplinary or tertiary rehabilitation approach, whereas work conditioning and work hardening fall within secondary rehabilitation.[1]

Who May Be a Candidate for a Functional Restoration Program?

Functional restoration is generally not the first treatment given after an uncomplicated injury.

It is more commonly considered when pain has become chronic, appropriate conservative treatment has already been tried and the person remains significantly functionally impaired.

Current occupational medicine guidance recommends these programs selectively for people with chronic pain who have not adequately responded to evidence-based conventional treatment, have limited remaining treatment options and continue to experience substantial incapacity.[1]

Participation also matters.

Because rehabilitation is active and intensive, a person needs to be medically stable enough to exercise and capable of participating in the educational and behavioral portions of treatment.

Serious uncontrolled medical or psychiatric problems, active substance misuse or circumstances that prevent meaningful participation may need to be addressed before an intensive program is appropriate.[1]

How Is Progress Measured During Functional Restoration?

Pain intensity may be recorded, but it should not be the only measure of success.

Clinicians may look at walking tolerance, strength, flexibility, lifting capacity, endurance, sitting and standing tolerance, ability to perform activities of daily living, confidence with movement, emotional functioning and readiness to return to work.

This distinction is important because pain and disability are not identical.

A patient’s pain score could remain at 5 out of 10 while the person progresses from walking for 10 minutes to walking for an hour, starts shopping independently, sleeps more regularly and returns to work.

From a functional restoration perspective, that may represent substantial improvement.

Research supports the broader focus on function. Systematic reviews have found that intensive multidisciplinary biopsychosocial rehabilitation incorporating functional restoration can improve function in people with disabling chronic low back pain, with evidence of improvement in pain as well.[9]

More recent research has also found improvements across physical and psychological measures after interdisciplinary rehabilitation, although programs vary considerably in their format, intensity and results.[4,10]

Should You Expect to Be Pain-Free at the End?

Not necessarily.

This may be the biggest misconception surrounding functional restoration.

Pain reduction is certainly welcome, and some people experience it. But the defining objective is generally greater function and better self-management, not a guarantee of complete pain elimination.

A person may finish the program still experiencing chronic pain but be significantly more capable than before treatment.

For example, someone who previously avoided bending may learn to bend and lift safely. Someone unable to sit for more than 20 minutes may gradually tolerate longer periods. Another person may return to modified or full-duty work even though intermittent pain remains.

That is why simply asking, “What is your pain score now?” does not capture everything functional restoration is intended to accomplish.

What Happens After a Functional Restoration Program Ends?

The end of formal treatment is supposed to mark a transition toward independent management rather than dependence on continuous supervised care.

The participant may receive a home exercise program, recommendations for ongoing cardiovascular exercise, strengthening goals, strategies for managing future flare-ups and a plan for gradually increasing normal activities.

When work disability is involved, the final recommendations may also address work capacity and appropriate restrictions.

Long-term follow-up research on interdisciplinary pain rehabilitation suggests that improvements achieved during treatment can persist after the formal program ends, although outcomes vary and no program can guarantee a particular result.[10]

The real test of a functional restoration program therefore comes after discharge: Can the person continue using what they learned when therapists are no longer beside them every day?

What Should You Expect Before Starting a Functional Restoration Program?

Expect an active program.

Expect exercise to increase gradually.

Expect some days to be harder than others.

Expect the team to ask about more than the location of your pain.

And expect the program to require meaningful participation outside therapy sessions as well as inside them.

Most importantly, do not judge progress only by whether pain disappears.

A functional restoration program is intended to help someone move from being organized around pain and treatment toward being organized around activity, independence and participation in life.

For someone who has spent months or years moving between appointments, medications and procedures without regaining meaningful function, that shift can be the most important part of the program.

How Long Is a Functional Restoration Program? The Bottom Line

There is no universal functional restoration program duration.

Highly intensive programs commonly run for approximately four to six weeks, and current California workers’ compensation guidance describes a model involving at least five treatment hours per day for four to six weeks, generally up to 160 hours.[1] Other established programs may spread rehabilitation across seven, eight or even ten weeks.[3-5]

The daily schedule generally combines graded exercise, physical conditioning, occupational therapy, pain education, behavioral or psychological treatment, functional activities and, when appropriate, work simulation.

As treatment progresses, the exercises should become less about what the patient can do inside a rehabilitation clinic and more about what the person needs to do in everyday life.

That is ultimately what “functional restoration” means.

The goal is not simply to complete a certain number of therapy sessions. It is to restore as much physical, psychological, social and occupational function as reasonably possible—and to give the patient the skills needed to maintain those gains after the program is over.

References:

  1. American College of Occupational and Environmental Medicine. Chronic Pain Guideline. California Division of Workers’ Compensation, Medical Treatment Utilization Schedule. 2026. (CalDIR)
  2. Poiraudeau S, Rannou F, Revel M. Functional restoration programs for low back pain: a systematic review. 2007. (PubMed)
  3. An Interdisciplinary Pain Rehabilitation Programme: Description and Evaluation of Outcomes. (PubMed Central (PMC))
  4. Giertych A, et al. Clinical Effectiveness of a Functional Restoration Program Compared to Conventional Medical Management in Patients With Chronic Pain. American Journal of Physical Medicine & Rehabilitation. 2025. (PubMed)
  5. Systematic description of an interdisciplinary multimodal pain treatment programme for patients with chronic musculoskeletal pain. 2022. (PubMed Central (PMC))
  6. Stanos S. Focused review of interdisciplinary pain rehabilitation programs for chronic pain management. 2012. (PubMed)
  7. American College of Occupational and Environmental Medicine. Initial Approaches to Treatment. 2026. (ACOEM)
  8. Prognostic Factors for Physical Functioning After Multidisciplinary Rehabilitation in Patients With Chronic Musculoskeletal Pain: A Systematic Review and Meta-Analysis. (PubMed)
  9. Guzmán J, et al. Multidisciplinary rehabilitation for chronic low back pain: systematic review. BMJ. 2001. (PubMed)
  10. Longitudinal Outcome Evaluations of Interdisciplinary Multimodal Pain Treatment Programs for Patients With Chronic Primary Musculoskeletal Pain: A Living Systematic Review. (PubMed)

Functional Restoration Program After a Work Injury: What Workers’ Compensation Patients Should Expect

A work injury can begin with something very specific—a lifting injury to the lower back, a fall that damages the knee, repetitive work that aggravates the neck and shoulder, or an operation needed after an accident. But months later, the problem may no longer be limited to the original injured body part.

You may be moving less. Your strength and endurance may have declined. Physical therapy helped to a point, but you are still unable to meet the demands of your job. You may have developed fear about lifting, bending, driving, climbing, or using the injured arm. Sleep may be poor. Pain may dominate the day. You may have seen several specialists without getting any closer to returning to work.

When recovery reaches this kind of standstill, a functional restoration program after a work injury may be recommended.

Functional restoration is not simply another round of physical therapy. It is an intensive, coordinated form of rehabilitation that addresses the physical, psychological, behavioral, and occupational barriers that can keep an injured worker from recovering function. The goal is not necessarily to make every trace of pain disappear. It is to help the person become more capable, independent, and prepared to return to work or another productive level of activity.[1][2]

For workers’ compensation patients, the program can also feel very different from ordinary medical care because progress is often measured against specific job demands, such as how much a person can lift, how long they can stand, whether they can bend repeatedly, or whether they can tolerate a full workday.

Understanding that difference before starting can make the process far less confusing.

What Is a Functional Restoration Program for an Injured Worker?

A functional restoration program is an interdisciplinary rehabilitation program generally considered for people who continue to have substantial functional limitations after a work-related injury despite appropriate medical treatment.

The approach recognizes that chronic work-related pain is often more complicated than a damaged disc, painful joint, strained muscle, or irritated nerve.

After months away from normal activity, an injured worker may have:

  • Reduced muscle strength
  • Poor cardiovascular endurance
  • Limited flexibility
  • Difficulty tolerating prolonged sitting or standing
  • Fear of reinjury
  • Anxiety about returning to work
  • Depression or frustration related to prolonged disability
  • Poor sleep
  • Increasing dependence on passive treatments
  • Difficulty coping with pain flare-ups
  • A large gap between current physical capacity and actual job requirements

Functional restoration attempts to address these problems together rather than sending the patient to several unrelated providers.

Current occupational medicine guidance describes functional restoration as an intensive, multimodal rehabilitation approach that objectively measures physical function and combines graded exercise with psychological, behavioral, and case-management components.[1]

Depending on the program, the treatment team may include a rehabilitation or pain physician, physical therapist, occupational therapist, psychologist, nurse, vocational specialist, case manager, and other professionals.

Why Is Functional Restoration Recommended After a Work Injury?

Most workers do not enter a functional restoration program immediately after an injury.

Early treatment commonly focuses on diagnosing the problem and providing appropriate medical care, which may include medication, physical therapy, temporary activity modification, injections, or surgery when medically indicated.

A functional restoration program becomes more relevant when the injury has moved into a different stage: the medical condition may have stabilized, but the worker has not recovered enough function to resume normal life or work.

For example, a warehouse worker may have completed treatment for a lumbar injury but still be unable to repeatedly lift 40 pounds. A nurse may have recovered from a shoulder injury but remain unable to reach overhead or assist with patient transfers. An office employee may have persistent neck and back pain that makes sitting through an eight-hour workday difficult.

In these situations, continuing to treat pain without addressing function may not close the gap between what the person can currently do and what the job actually requires.

Functional restoration therefore asks a more practical question:

What is preventing this worker from functioning, and what needs to improve for the worker to move forward?

That may include physical limitations, but it can also include fear of movement, reduced confidence, poor coping strategies, prolonged inactivity, depression, workplace concerns, or unrealistic expectations about what recovery should feel like.

Who Is a Good Candidate for a Functional Restoration Program?

Functional restoration is not necessary for every injured worker with persistent pain.

It is generally considered for patients who have significant disability and are not progressing adequately with less intensive treatment.

Current occupational guidance lists several factors that may support referral to a tertiary pain or functional restoration program. These include being off work or on modified duty for a prolonged period without clear progress toward recovery, failure of appropriate lower-level treatments to restore function, meaningful gaps between current physical abilities and occupational demands, and the presence of behavioral or psychosocial factors interfering with recovery.[1]

A potential candidate may therefore be someone who:

  • Has persistent pain after a work injury
  • Has remained off work or on restrictions
  • Has completed appropriate conventional treatment without sufficient functional improvement
  • Has difficulty meeting essential job demands
  • Has become significantly deconditioned
  • Is fearful of movement or reinjury
  • Has difficulty progressing through standard physical therapy
  • Has psychological or behavioral barriers affecting rehabilitation
  • Requires coordinated treatment from several disciplines
  • Has reasonable rehabilitation potential
  • Is willing to participate actively in recovery

Importantly, pain severity alone does not determine eligibility.

A person with severe pain who remains active and continues progressing may not require this level of treatment. Meanwhile, someone with moderate pain but substantial disability, fear avoidance, deconditioning, and prolonged work absence may be a more appropriate candidate.

What Happens Before the Functional Restoration Program Starts?

Most programs begin with a multidisciplinary evaluation.

This is more extensive than a routine medical appointment because the team is trying to understand why recovery has stalled.

The assessment may include:

  • Review of the original work injury
  • Current diagnoses
  • Previous imaging and diagnostic studies
  • Surgery or procedures already performed
  • Physical therapy and other conservative treatment
  • Current medications
  • Pain severity and pattern
  • Strength and endurance
  • Functional limitations
  • Ability to perform activities of daily living
  • Current work restrictions
  • Physical requirements of the job
  • Psychological health
  • Fear of movement or reinjury
  • Sleep
  • Coping strategies
  • Substance or medication-related concerns
  • Personal and workplace barriers to recovery

Baseline functional testing may also be performed so that improvement can be measured objectively rather than relying only on whether the patient says the pain feels better.[1]

A worker might initially be able to lift only 10 pounds from floor to waist, tolerate 15 minutes of standing, or sit for 30 minutes before needing to change position. Those measurements provide something concrete to work on during the program.

What Does a Functional Restoration Program Actually Involve?

Although programs vary, functional restoration usually contains several components that occur together.

Intensive Physical Reconditioning

Physical rehabilitation is a major part of the program.

After months of reduced activity, it is common for strength and endurance to decline. Even when the original injury has healed as much as medically expected, deconditioning can make ordinary physical demands feel increasingly difficult.

Treatment may include:

  • Cardiovascular conditioning
  • Progressive strengthening
  • Core stabilization
  • Flexibility exercises
  • Walking
  • Balance exercises
  • Lifting
  • Carrying
  • Pushing and pulling
  • Repeated bending
  • Postural training

The exercises are typically progressed gradually based on measurable improvement rather than waiting for the patient to become completely pain-free.

Occupational medicine guidance emphasizes progressive aerobic exercise, strengthening, simulated work tasks, and exercises targeted specifically at the difference between the worker’s present ability and job requirements.[1]

Work-Specific Activities

One reason a functional restoration program for workers’ compensation patients differs from general fitness rehabilitation is its occupational focus.

If the worker’s job involves lifting, the program may progressively increase lifting capacity.

If the job requires prolonged standing, treatment may focus on standing tolerance.

If the job requires repetitive reaching, carrying, climbing, pushing, pulling, or material handling, these activities may be simulated in a controlled rehabilitation environment.

The aim is to make rehabilitation resemble real functional demands rather than simply completing exercises on a treatment table.

Occupational Therapy

Occupational therapists may focus on practical activities that connect physical recovery with everyday and workplace function.

This can include:

  • Body mechanics
  • Ergonomic strategies
  • Activity pacing
  • Task modification
  • Tolerance for sustained activity
  • Work simulation
  • Household activities
  • Daily routines
  • Energy management

The therapist may also identify inefficient or protective movement patterns that developed after the injury.

For example, a patient may avoid using one arm and compensate with the other, or may move the entire trunk to avoid bending the spine. Some protective strategies are appropriate early after an injury, but over time they can become unnecessary and interfere with normal function.

Why Is Psychology Part of a Functional Restoration Program?

Some injured workers are surprised—or even concerned—when they learn that psychology is part of the program.

A psychological component does not mean the healthcare team believes the pain is imaginary.

Chronic pain can affect emotional health, and emotional responses can also affect how people move, sleep, exercise, and respond to pain.

One important issue is fear avoidance.

Suppose a worker experiences severe back pain while lifting. Afterward, the person begins associating lifting with danger. Soon, bending is avoided as well. Then exercise is reduced. Eventually, nearly any movement that produces discomfort is interpreted as evidence of further injury.

The cycle can look like this:

Pain → fear of reinjury → movement avoidance → physical deconditioning → reduced ability → more difficulty with activity → greater fear

Functional restoration attempts to interrupt this cycle.

Psychological treatment may include cognitive behavioral strategies, relaxation techniques, stress management, pain coping skills, goal setting, and strategies for reducing fear of movement.

Research has found that psychosocial factors including perceived disability, depression, fear avoidance, and beliefs about pain can influence completion of functional restoration and successful return to function.[3]

Pain Education Is Part of Rehabilitation

Another major goal is helping workers understand how to manage chronic pain without allowing every flare-up to stop rehabilitation.

This may include learning about:

  • Chronic pain versus acute injury
  • Pain sensitization
  • Safe activity progression
  • Flare-up management
  • Pacing
  • Sleep
  • Stress
  • Relaxation
  • Exercise
  • Fear of reinjury
  • Self-management after discharge

This becomes especially important when someone has spent months moving from one passive treatment to another.

Functional restoration is an active rehabilitation model. The patient is expected to take an increasingly important role in managing the condition.

Will Medications Be Changed During Functional Restoration?

Medication review is often part of interdisciplinary pain rehabilitation, but the exact approach varies by program and by patient.

The medical team may consider:

  • Whether medication is actually improving function
  • Sedation or other adverse effects
  • Dependence on short-term symptom relief
  • Medication combinations
  • Whether certain drugs interfere with safe activity or work
  • Whether medication reduction is appropriate

Patients taking significant amounts of opioid pain medication, benzodiazepines, or other potentially dependence-forming medications may require additional assessment or specialized management before or during rehabilitation.[1]

This should not be interpreted as a reason to abruptly stop prescribed medication. Any medication change should be supervised by the treating clinician.

How Long Does a Functional Restoration Program Last?

There is no single duration used everywhere.

Some programs are highly intensive and run for several hours per day, five days per week, while others use different schedules.

For example, occupational medicine guidance used within California’s workers’ compensation medical treatment framework describes a typical functional restoration expectation of at least five hours per day for approximately four to six weeks, with a maximum of 160 hours unless an exception is justified.[1] These figures should not be assumed to apply to every state or every workers’ compensation claim.

Published studies have evaluated different formats. One United States workers’ compensation interdisciplinary pain program used a four-week schedule involving eight-hour treatment days, Monday through Friday.[4] Another recent study of patients with chronic pain following work injuries evaluated an eight-week functional restoration program.[2]

The duration therefore depends on the program, severity of disability, job demands, progress, medical conditions, psychological barriers, transportation, work schedules, and authorization.

How Does Workers’ Compensation Authorization for Functional Restoration Work?

This is often one of the biggest practical concerns for injured workers.

A treating physician or rehabilitation specialist may recommend functional restoration, but workers’ compensation treatment frequently requires documentation showing why the program is medically necessary.

The specific process differs by state, insurer, claim, and applicable medical treatment guidelines.

Documentation may include evidence that:

  • The worker has persistent functional limitations
  • Appropriate treatment has already been attempted
  • Less intensive rehabilitation has not restored adequate function
  • The worker has rehabilitation potential
  • Current physical abilities do not meet job requirements
  • Psychological or behavioral barriers are affecting recovery
  • Functional goals can be clearly identified and measured

Authorization may also be linked to continued progress.

For example, some occupational guidelines recommend regular documentation of physical and psychological gains during treatment and periodic requests for continued authorization. Current guidance incorporated into California’s workers’ compensation framework describes weekly tracking of functional progress and commonly scheduled payer review during the program.[1]

The important point for patients is that approval of a functional restoration program is usually based on documented functional need, not simply the presence of ongoing pain.

Workers should ask their treating physician or claims representative about the rules that apply specifically to their case because workers’ compensation requirements vary substantially between jurisdictions.

Functional Restoration vs Work Hardening: What Is the Difference?

These treatments overlap, but they are not identical.

Work conditioning or work hardening generally focuses more heavily on physical conditioning and job-specific abilities.

Functional restoration is broader.

It may include physical reconditioning and work simulation, but it also addresses pain behavior, psychological factors, coping strategies, fear avoidance, medication issues, and other barriers to recovery.

This distinction matters because not every worker needs a full interdisciplinary program.

If the primary problem is simply that the person needs greater strength and endurance to meet job demands, a work conditioning or work hardening program may be more appropriate. Occupational guidance specifically notes that workers who have primarily physical deficits without significant behavioral barriers may be better suited to work conditioning or work hardening rather than a full functional restoration program.[1]

Does Functional Restoration Mean You Must Return to Your Exact Same Job?

Not necessarily.

Return to work is usually an important goal, but that can take several forms:

  • Returning to the same job without restrictions
  • Returning initially with modified duties
  • Returning gradually
  • Returning to a different position with the same employer
  • Preparing for employment with another employer
  • Becoming physically ready for vocational retraining or job seeking

A worker who can no longer perform a particularly heavy job may still make substantial functional gains that allow employment in another capacity.

The rehabilitation team may compare measured abilities with actual job demands and update work restrictions as progress is made.

The focus should be on what the worker can safely and sustainably do, not simply whether pain is still present.

Does Functional Restoration Work for Injured Workers?

Research is encouraging, although no treatment guarantees that every patient will return to work.

A 2025 multicenter analysis evaluated 485 patients with chronic pain following work-related injuries. Patients who completed an eight-week functional restoration program showed significant improvement in several measures of physical function, depression, anxiety, and pain self-efficacy compared with patients receiving conventional medical management. Not every physical outcome showed a statistically significant difference, which is an important reminder that results vary.[2]

Earlier research has also reported favorable occupational outcomes.

In one prospective study of chronic low back pain, 55 percent of participants had returned to work at long-term follow-up compared with only 9 percent working at baseline. Physical disability, quality of life, psychological measures, and fear-avoidance beliefs also improved.[5]

Another large study involving workers with chronic disabling occupational musculoskeletal disorders found that people who entered functional restoration after a longer period of disability were less likely to complete the program and had somewhat poorer work outcomes. However, substantial numbers of even very long-term disabled patients still returned to and retained employment after treatment.[6]

This suggests an important principle: long-standing disability does not mean rehabilitation is pointless, but earlier restoration of function may offer advantages.

What If Pain Gets Worse During the Program?

Some increase in discomfort can occur when a person who has been relatively inactive begins exercising several hours a day.

That does not mean all pain should simply be ignored.

The rehabilitation team should distinguish between expected exercise-related discomfort and symptoms suggesting a medical problem or worsening injury.

One of the skills patients often develop is learning that pain and tissue damage are not always the same thing, especially in a long-standing pain condition.

At the same time, new neurological symptoms, substantial new weakness, significant swelling, fever, new trauma, loss of bowel or bladder control, or other concerning changes should be reported and medically evaluated rather than treated as routine rehabilitation discomfort.

What Can Cause a Functional Restoration Program to Fail?

The program requires active participation.

Factors that can interfere with success include:

  • Frequent unexplained absences
  • Lack of engagement
  • Continuing to rely exclusively on passive treatment
  • Severe untreated psychological illness
  • Substance misuse
  • Unrealistic expectations of becoming completely pain-free before increasing activity
  • Fear of movement that is not successfully addressed
  • Unresolved medical problems
  • Major transportation or family barriers
  • Workplace barriers
  • Poor coordination between treatment providers and the workers’ compensation system

Research has also shown that patients who do not complete functional restoration can have worse subsequent healthcare utilization and socioeconomic outcomes than those who complete treatment.[7]

This is one reason the initial evaluation matters. The team needs to determine whether the worker is physically and psychologically prepared to benefit from the intensity of the program.

What Happens at the End of Functional Restoration?

Toward the end of treatment, the team generally reassesses the same abilities measured at the beginning.

That might include:

  • Lifting capacity
  • Carrying
  • Sitting tolerance
  • Standing tolerance
  • Walking endurance
  • Repetitive activity tolerance
  • Strength
  • Range of motion
  • Work simulation
  • Activities of daily living
  • Psychological measures
  • Pain self-efficacy
  • Fear of reinjury

The final report may recommend return to full duty, modified work, permanent restrictions, additional vocational planning, or continued self-directed rehabilitation depending on the individual situation.

Legal and disability classifications at the end of treatment vary according to the workers’ compensation system and jurisdiction. Patients should therefore discuss claim-specific implications with their treating physician, claims representative, or attorney when appropriate rather than assuming that completion of functional restoration automatically produces a particular legal outcome.

Life After the Program: The Home Program Matters

Functional restoration is not intended to create permanent dependence on a rehabilitation facility.

Once the worker has developed the necessary skills, the emphasis shifts toward maintaining them independently.

A long-term plan may include:

  • Regular cardiovascular exercise
  • Strength training
  • Stretching
  • Proper body mechanics
  • Maintaining healthy sleep habits
  • Managing temporary pain flare-ups
  • Continuing psychological coping strategies
  • Gradually increasing recreational activity
  • Following appropriate work restrictions
  • Maintaining a healthy daily routine

Occupational guidance emphasizes continued self-directed physical restoration and psychological pain-management strategies after successful discharge.[1]

The goal is to prevent every flare-up from restarting the same cycle of inactivity, fear, medical visits, and loss of function.

Questions Workers Should Ask Before Starting a Functional Restoration Program

Before enrolling, it can help to ask:

  • Why is functional restoration being recommended in my case?
  • What specific functional deficits are being treated?
  • How many hours per day will I attend?
  • How many weeks is the program expected to last?
  • What happens if workers’ compensation does not authorize the entire program?
  • Will physical therapy and occupational therapy be included?
  • Will I meet with a psychologist?
  • How will my job requirements be incorporated into treatment?
  • How will progress be measured?
  • Will my work restrictions change during the program?
  • Will medications be changed?
  • What happens if my pain temporarily increases?
  • What are the goals for returning to work?
  • What happens if I cannot return to my previous job?
  • What home program will I follow after discharge?

The answers should make it clear that treatment has measurable goals rather than simply requiring the injured worker to attend a set number of sessions.

The Bottom Line

A functional restoration program after a work injury is generally considered when an injured worker remains significantly limited despite appropriate medical treatment and ordinary rehabilitation.

It is not simply another attempt to reduce pain.

Functional restoration focuses on rebuilding the abilities that prolonged pain and disability have taken away: strength, endurance, confidence in movement, coping skills, independence, and the capacity to perform meaningful work.

The program may combine progressive exercise, occupational therapy, simulated work activities, psychological treatment, pain education, medication management, and return-to-work planning within one coordinated treatment plan.

For workers’ compensation patients, the experience can be demanding. Treatment may occupy several hours a day, progress is closely measured, and active participation is expected. Authorization requirements may also add another layer to the process.

But the underlying objective is straightforward: to close the gap between what the injured worker can do today and what the person needs to be able to do to move forward.

Success does not always mean returning to exactly the same job with absolutely no pain. For one person, success may mean returning to full duty. For another, it may mean modified work, a different occupation, greater independence, reduced fear of activity, or the ability to manage chronic pain without allowing it to control everyday life.

That is ultimately what functional restoration is designed to restore—not simply a body part, but the ability to function again.

References:

  1. American College of Occupational and Environmental Medicine. Chronic Pain Guideline – Rehabilitation and Tertiary Pain Programs. Medical Treatment Utilization Schedule, California Division of Workers’ Compensation. Current occupational guidance addresses functional restoration eligibility, objective functional assessment, return-to-work goals, treatment duration, and program components. (Cal DIR)
  2. Giertych A, Crane J, Goozeé S, et al. Clinical Effectiveness of a Functional Restoration Program Compared to Conventional Medical Management in Patients With Chronic Pain: A Multicenter, Retrospective Observational Analysis. American Journal of Physical Medicine & Rehabilitation. 2025;104(8):735-742. doi:10.1097/PHM.0000000000002713. (PubMed)
  3. Howard KJ, Mayer TG, Gatchel RJ. Psychosocial Factors Related to Functional Restoration Treatment Completion and Return-to-Function for Patients With Chronic Disabling Occupational Musculoskeletal Disorders. Journal of Occupational Rehabilitation. 2017. (PubMed)
  4. Bosy D, Etlin D, Corey D, Lee JW. Treatment outcomes for workers compensation patients in a U.S.-based interdisciplinary pain management program. Pain Practice. 2012. (PubMed)
  5. Poulain C, Kernéis S, Rozenberg S, et al. Long-term return to work after a functional restoration program for chronic low-back pain patients: a prospective study. European Spine Journal. 2010;19:1153-1161. (PubMed Central (PMC))
  6. Mayer TG, Choi YH, Howard KJ, et al. Does the Length of Disability between Injury and Functional Restoration Program Entry Affect Treatment Outcomes for Patients with Chronic Disabling Occupational Musculoskeletal Disorders? Journal of Occupational Rehabilitation. 2018. (PubMed)
  7. Howard KJ, Mayer TG, Gatchel RJ. Failure to complete a functional restoration program for chronic musculoskeletal disorders: a prospective 1-year outcome study. Archives of Physical Medicine and Rehabilitation. 2005. (PubMed)
  8. Corey DT, Koepfler LE, Etlin D, Day HI. A limited functional restoration program for injured workers: a randomized trial. Journal of Occupational Rehabilitation. 1996;6(4):239-249. (PubMed)
  9. Roche G, Ponthieux A, Parot-Shinkel E, et al. Comparison of a functional restoration program with active individual physical therapy for patients with chronic low back pain: a randomized controlled trial. Research on multidisciplinary functional restoration and occupational rehabilitation has supported the use of active rehabilitation approaches for selected chronic pain patients.
  10. Mayer TG, Gatchel RJ, Kishino N, et al. Objective assessment of spine function following industrial injury: a prospective study with comparison group and one-year follow-up. Functional restoration research has historically emphasized objective physical capacity measurement and return-to-work outcomes.

Functional Restoration for Chronic Pain: Rebuilding Life Beyond Pain

Living with chronic pain can gradually make life smaller. At first, you may stop lifting heavy objects or avoid a particular exercise. Later, you may find yourself walking less, sleeping at unusual hours, relying on family members for routine tasks, missing work, or planning almost every part of the day around how much pain you expect to feel.

When medications, injections, physical therapy, surgery, or other treatments have not restored normal function, simply trying another pain-relieving treatment may not be enough. This is where a functional restoration program for chronic pain may be considered.

A functional restoration program takes a different approach. Rather than making pain elimination the only measure of success, it focuses on helping a person become stronger, more active, more confident, and better able to manage everyday life despite chronic pain. Treatment is usually interdisciplinary, bringing together physical rehabilitation, occupational therapy, pain education, psychological strategies, and other forms of care within one coordinated program.[1][2]

For someone who has spent months or years moving less because of pain, that change in focus can be important. The question becomes less about “How can I make sure I never hurt?” and more about “How can I safely get back to doing the things pain has taken away from me?”

What Is a Functional Restoration Program?

A functional restoration program is a structured rehabilitation program designed for people whose chronic pain has significantly interfered with physical activity, work, daily responsibilities, emotional well-being, or quality of life.

The approach is based on the understanding that long-lasting pain can affect much more than the injured or painful body part. Over time, pain can influence muscle strength, endurance, sleep, mood, confidence, movement patterns, relationships, work participation, and the way a person reacts to physical activity.

Because several parts of life may become affected at the same time, treating only one piece of the problem may not be enough.

Functional restoration therefore commonly uses a biopsychosocial approach to chronic pain. This means treatment considers physical factors along with psychological, behavioral, occupational, and social factors that can influence disability and recovery.[2][3]

This does not mean the pain is imaginary or “all in the mind.” The pain is real. The goal is to address the many ways persistent pain can affect the body and a person’s daily functioning.

Depending on the program, the treatment team may include:

  • A physician specializing in pain medicine or physical medicine and rehabilitation
  • Physical therapists
  • Occupational therapists
  • Psychologists or behavioral health professionals
  • Nurses
  • Vocational rehabilitation specialists
  • Medication-management professionals
  • Other rehabilitation specialists

These providers work toward a shared set of functional goals rather than treating each problem independently.

What Is the Main Goal of Functional Restoration for Chronic Pain?

The central goal is restoring function.

That may sound simple, but it represents a major difference from many conventional pain treatments.

A person entering treatment might naturally say, “I want my pain to go away.” A functional restoration team may instead help turn that broad goal into practical targets such as:

  • Walking for 30 minutes
  • Sitting long enough to drive or work
  • Returning to household chores
  • Improving lifting tolerance
  • Going grocery shopping independently
  • Sleeping on a more regular schedule
  • Returning to work
  • Caring for children
  • Exercising again
  • Reducing reliance on passive treatments
  • Resuming hobbies and social activities

Pain may improve during the process, and research has shown reductions in pain in some groups. However, a functional restoration program does not require pain to completely disappear before activity can improve.[4]

That distinction is particularly important for chronic pain conditions in which repeatedly waiting for a “pain-free day” can lead to months or years of inactivity.

How Does a Functional Restoration Program Work?

Most programs begin with a detailed evaluation rather than placing every patient into the same treatment plan.

The assessment may review the person’s diagnosis, medical history, previous treatments, medication use, physical abilities, psychological health, work situation, sleep, daily activity level, substance use history, social circumstances, and specific barriers preventing recovery.[5]

From there, the treatment team develops functional goals and identifies the areas that require the most attention.

Although programs differ, several components are commonly used.

Physical Reconditioning and Graded Exercise

One of the most important parts of a functional restoration program is gradually rebuilding physical capacity.

People with chronic pain often become less active over time. Sometimes this happens because movement hurts. Sometimes they have been advised to rest repeatedly. Others become understandably worried that activity will worsen an injury.

Unfortunately, prolonged inactivity can cause its own problems.

Muscle strength may decline. Cardiovascular endurance can decrease. Normal movements begin to feel unusually demanding. A short walk, climbing stairs, carrying groceries, or sitting through a workday may become increasingly difficult.

Physical rehabilitation may therefore include:

  • Aerobic conditioning
  • Strengthening exercises
  • Flexibility exercises
  • Core conditioning
  • Balance training
  • Walking
  • Postural training
  • Body mechanics
  • Lifting practice
  • Gradual exposure to previously avoided movements

The intensity is usually progressed over time according to the person’s abilities and treatment goals. Physical therapists may also teach safer lifting techniques, movement strategies, posture, and ways to increase activity without repeatedly stopping whenever discomfort occurs.[6]

The objective is not to force someone through dangerous pain. It is to distinguish between situations requiring medical protection and the discomfort that can sometimes occur while a deconditioned body gradually becomes active again.

Occupational Therapy and Returning to Everyday Activities

Chronic pain does not occur only in the gym or physical therapy room. It affects getting dressed, cleaning the house, preparing meals, driving, working, shopping, parenting, hobbies, and countless other ordinary activities.

Occupational therapy helps bridge the gap between exercise and real life.

Treatment may focus on improving tolerance for tasks such as:

  • Sitting at a desk
  • Standing for prolonged periods
  • Bending
  • Reaching
  • Carrying objects
  • Cooking
  • Household chores
  • Computer use
  • Personal care
  • Work-related activities

The therapist may also examine pacing, ergonomics, daily schedules, energy conservation, and the way a patient organizes activity throughout the day.

For someone hoping to return to employment, rehabilitation may gradually become more job-specific.

Pain Psychology and Changing the Fear-Avoidance Cycle

Psychological treatment is sometimes misunderstood when it is included in a chronic pain rehabilitation program.

Its purpose is not to convince patients that nothing is physically wrong.

Instead, chronic pain psychology addresses the thoughts, emotions, behaviors, stress responses, and fears that can understandably develop after living with pain for a long time.

Consider a person who experiences severe back pain while bending. They may begin avoiding bending altogether. Soon they avoid exercise, lifting, travel, housework, and eventually even ordinary movement. The body becomes less conditioned, movement becomes harder, and this may reinforce the belief that activity is dangerous.

This can create a cycle:

Pain → fear of movement → reduced activity → physical deconditioning → greater difficulty with activity → increased fear and disability.

Psychological approaches such as cognitive behavioral therapy and acceptance and commitment therapy may help patients recognize unhelpful patterns, improve coping skills, manage stress, set realistic goals, and gradually become less fearful of activity.[6]

Pain psychology may also address depression, anxiety, sleep problems, anger, frustration, and the emotional strain that often accompanies long-term disability.

Pain Education and Self-Management Skills

Understanding chronic pain is itself an important part of rehabilitation.

Patients may learn about:

  • How acute pain differs from persistent pain
  • Pain sensitization
  • The relationship between stress and pain
  • Sleep and pain
  • Activity pacing
  • Relaxation techniques
  • Flare-up management
  • Healthy movement
  • Problem-solving strategies
  • Setting realistic functional goals

The long-term aim is to make the patient less dependent on repeated medical interventions for every increase in symptoms and more confident in managing predictable pain fluctuations.

That does not mean new or concerning symptoms should be ignored. Rather, patients learn how to manage their established chronic pain while recognizing when a change genuinely requires medical evaluation.

Medication Review May Be Part of the Program

Some functional restoration and interdisciplinary pain rehabilitation programs include medication management.

The treatment team may review whether medications are improving function, whether adverse effects are interfering with rehabilitation, and whether certain medications can be safely reduced.

Some intensive pain rehabilitation programs specifically include medically supervised reduction of opioid pain medications or other symptom-focused medications.[1][7]

This does not mean everyone entering a functional restoration program must stop every pain medication. Medication policies vary among programs and individual patients.

Importantly, prescription pain medicines should not be stopped abruptly without appropriate medical guidance. Any medication reduction should be individualized and supervised by the treating medical team.

Who Is a Good Candidate for a Functional Restoration Program?

There is no single diagnosis that automatically makes someone an ideal candidate.

The bigger question is usually how much chronic pain has affected the person’s ability to function.

A functional restoration program may be considered when pain has persisted for months and has resulted in substantial limitations despite appropriate treatment.

Potential candidates may include people who:

  • Have chronic pain that significantly limits daily activity
  • Have difficulty returning to work
  • Have become physically deconditioned
  • Avoid movement because of fear of worsening pain
  • Have completed conventional physical therapy but remain functionally limited
  • Have tried multiple medical treatments without regaining normal activity
  • Depend increasingly on passive treatments
  • Have difficulty performing household or self-care activities
  • Experience emotional distress related to chronic pain
  • Need a coordinated approach rather than several disconnected treatments
  • Are medically stable enough to participate in progressive rehabilitation

An evaluation is important because successful participation requires more than having a painful condition. Patients generally need to be willing and medically able to participate actively in treatment.

What Conditions Can Be Treated With Functional Restoration?

Functional restoration has been studied particularly extensively in people with chronic low back pain and chronic musculoskeletal disorders, but interdisciplinary pain rehabilitation is used for a much broader range of persistent pain conditions.[4][8]

Depending on the program, patients may have conditions such as:

  • Chronic low back pain
  • Chronic neck pain
  • Persistent pain after an injury
  • Chronic pain after surgery
  • Fibromyalgia
  • Complex regional pain syndrome
  • Neuropathic pain
  • Myofascial pain
  • Chronic headaches or migraines
  • Chronic pelvic pain
  • Sciatica
  • Widespread musculoskeletal pain
  • Work-related musculoskeletal injuries

The exact diagnosis is often less important than the presence of ongoing pain accompanied by meaningful loss of function.

Who May Not Be Ready for Functional Restoration?

Functional restoration is not appropriate as a substitute for evaluating an untreated medical problem.

For example, someone with a new progressive neurological deficit, an unstable medical condition, a newly identified injury requiring specific treatment, or another serious medical problem should first receive appropriate medical evaluation and management.

Some people may also need other conditions stabilized before they can fully participate in an intensive rehabilitation program.

This could include severe uncontrolled psychiatric symptoms, active substance-related problems, or medical conditions that make sustained physical activity unsafe.

Admission criteria vary considerably. Most comprehensive programs therefore conduct medical and psychological screening before enrollment rather than accepting patients based simply on the presence of chronic pain.[5]

How Long Does a Functional Restoration Program Last?

There is no universal schedule.

Functional restoration programs are typically more intensive than ordinary outpatient physical therapy. Some historical programs have used full-day treatment for approximately three to six weeks, while other contemporary programs last longer.[8]

For example, published research has examined:

  • Three-week intensive programs
  • Four- to six-week programs
  • Five-week multidisciplinary programs
  • Eight-week functional restoration programs
  • Ten-week interdisciplinary pain rehabilitation programs

A 2025 multicenter study evaluated an eight-week functional restoration program for patients with chronic pain following work-related injuries.[9]

The important point is that functional restoration is usually not a once-a-week appointment involving one therapist. It is designed to provide enough repetition and intensity for new physical and behavioral habits to develop.

Does a Functional Restoration Program Actually Work?

No chronic pain treatment works for every person, and functional restoration should not be presented as a guaranteed cure.

However, research supports the use of intensive multidisciplinary rehabilitation for appropriately selected patients.

A systematic review involving people with disabling chronic low back pain found strong evidence that intensive multidisciplinary biopsychosocial rehabilitation incorporating functional restoration improved function compared with non-multidisciplinary treatment. Evidence also supported improvement in pain, although effects on employment outcomes were less consistent.[4]

More recent research also provides encouraging findings.

A 2025 multicenter observational study involving 485 patients with chronic pain following work-related injuries compared people who completed an eight-week functional restoration program with those receiving conventional medical management. Functional restoration graduates showed statistically significant improvements in several measures involving physical function, depression, anxiety, and pain self-efficacy, although not every functional outcome measured improved significantly.[9]

Long-term results are also being studied. A 2025 longitudinal study followed 51 patients with nonspecific chronic low back pain after functional restoration. At the ten-year follow-up, 76.5 percent reported overall improvement, and disability scores remained better than before treatment. Among patients who had been work-disabled, more than half had returned to work at long-term follow-up. The relatively small study size means these findings should be interpreted cautiously, but they suggest that improvements can persist well beyond the treatment period.[10]

The research therefore supports a realistic message: functional restoration can improve function and other important outcomes in selected patients, but results vary and pain does not necessarily disappear completely.

Functional Restoration Program vs Physical Therapy: What Is the Difference?

Physical therapy can be an important part of a functional restoration program, but the two are not interchangeable.

Traditional physical therapy may primarily focus on improving strength, mobility, flexibility, posture, balance, or movement related to a particular injury or condition.

A functional restoration program for chronic pain typically goes further.

It may combine:

  • Physical rehabilitation
  • Occupational therapy
  • Psychological treatment
  • Pain education
  • Behavioral strategies
  • Medication management
  • Work-related rehabilitation
  • Lifestyle changes
  • Self-management training

This broader approach may be particularly useful when the problem has moved beyond one painful muscle, joint, or spinal level and is now affecting many parts of daily life.

Someone who has completed several rounds of physical therapy yet still cannot work, exercise, shop independently, sleep normally, or perform everyday activities may therefore require a different rehabilitation strategy rather than simply repeating the same type of treatment.

Will You Have More Pain During Functional Restoration?

Temporary increases in discomfort can occur when activity levels increase, particularly in someone who has been inactive for a long period.

This does not mean every increase in pain should be ignored.

One purpose of a supervised program is to help patients learn the difference between an expected response to increased activity and symptoms that warrant medical reassessment.

The progression should be structured and individualized. The objective is not to see how much pain someone can tolerate. It is to gradually increase physical capacity while building confidence in movement.

Over time, patients often learn that discomfort does not always have to dictate whether an activity can be attempted.

What Happens After Completing a Functional Restoration Program?

The end of formal treatment is not the end of functional restoration.

In many ways, it is the beginning of self-management.

Before discharge, patients may receive recommendations covering:

  • Home exercise
  • Aerobic activity
  • Strengthening
  • Work restrictions or return-to-work planning
  • Sleep
  • Stress management
  • Flare-up strategies
  • Medication follow-up
  • Psychological coping skills
  • Recreational activities
  • Long-term functional goals

The patient is expected to continue applying what was learned rather than returning to prolonged inactivity whenever pain increases.

Some programs also provide aftercare or coordinate recommendations with the patient’s regular healthcare providers.[2]

What Does Success Look Like?

Success in chronic pain rehabilitation can be easy to overlook if pain intensity is the only thing being measured.

A patient may still report pain yet be able to:

  • Walk farther
  • Exercise regularly
  • Sleep better
  • Return to work
  • Drive independently
  • Take care of children
  • Reduce reliance on medication
  • Attend social activities
  • Travel
  • Complete household tasks
  • Spend less time seeking medical treatment
  • Feel less frightened by pain flare-ups

Those changes can represent meaningful recovery even when some pain remains.

This is why functional restoration shifts the emphasis from “How much pain do you have today?” toward “What are you able to do today that pain previously prevented you from doing?”

Is Functional Restoration the Same as Accepting That Nothing More Can Be Done?

No.

Being referred to a functional restoration program does not mean doctors are dismissing the pain or giving up on treatment.

In fact, the approach is highly active.

Patients may spend considerably more time exercising, learning, practicing coping strategies, rebuilding endurance, and working toward specific goals than they would during many conventional treatments.

The difference is where the effort is directed.

Instead of continuing an endless search for a treatment that promises complete pain elimination, functional restoration attempts to reduce the control that chronic pain has over daily life.

For some patients, this represents an important turning point.

Questions to Ask Before Starting a Functional Restoration Program

If your doctor recommends functional restoration, it can help to understand exactly what the program involves.

Consider asking:

  • How intensive is the program?
  • How many weeks does it last?
  • How many hours per day will I participate?
  • Which healthcare professionals will be involved?
  • Will treatment include physical and occupational therapy?
  • Is pain psychology included?
  • How will my progress be measured?
  • Will my medications be changed?
  • How are pain flare-ups handled?
  • Does the program include return-to-work planning?
  • What happens after I complete the program?
  • What level of improvement would be considered a successful outcome?

Different programs use the term functional restoration somewhat differently, so asking about the actual treatment components is more useful than relying on the program name alone.

The Bottom Line

A functional restoration program for chronic pain is designed for people whose lives have become increasingly restricted by persistent pain. Instead of concentrating exclusively on reducing a pain score, the program aims to restore physical ability, confidence, independence, coping skills, and participation in everyday life.

Treatment commonly combines physical conditioning, occupational therapy, pain education, psychological strategies, and other rehabilitation services within a coordinated interdisciplinary program.

Functional restoration is not appropriate for everyone, and it is not a promise of complete pain relief. However, it can be an important option for people who remain significantly limited after conventional treatments and are medically able and willing to participate actively in rehabilitation.

For many people living with chronic pain, the most meaningful improvement is not waking up one morning with absolutely no pain. It is realizing that pain no longer decides whether they can work, walk, exercise, travel, spend time with family, or take part in the activities that make life feel normal again.

References:

  1. Mayo Clinic. Pain Rehabilitation Center – Overview. Integrated rehabilitation for chronic pain using behavioral, physical, occupational, and medication-management approaches. (Mayo Clinic)
  2. Mayo Clinic. Pain Rehabilitation Center – Featured Programs. Interdisciplinary treatment, physical reconditioning, cognitive behavioral treatment, medication optimization, and functional goals for chronic pain rehabilitation. (Mayo Clinic)
  3. Stanos S. Focused review of interdisciplinary pain rehabilitation programs for chronic pain management. Current Pain and Headache Reports. 2012;16(2):147-152. doi:10.1007/s11916-012-0252-4. (PubMed)
  4. Guzmán J, et al. Multidisciplinary rehabilitation for chronic low back pain: systematic review. BMJ. 2001;322:1511-1516. The review evaluated intensive multidisciplinary biopsychosocial rehabilitation incorporating functional restoration. (PubMed)
  5. Malaty A, Sabharwal J, Lirette LS, Chaiban G, Eissa H, Tolba R. How to assess a new patient for a multidisciplinary chronic pain rehabilitation program: a review article. Ochsner Journal. 2014;14(1):96-100. (PubMed)
  6. Mayo Clinic. Pain Rehabilitation Center – Core Components. Physical therapy, occupational therapy, pain education, behavioral treatment, biofeedback, and medication management within interdisciplinary rehabilitation. (Mayo Clinic)
  7. Townsend CO, et al. A longitudinal study of the efficacy of a comprehensive pain rehabilitation program with opioid withdrawal: comparison of treatment outcomes based on opioid use status at admission. Pain. 2008. (PubMed)
  8. Roche G, et al. Functional restoration programs for low back pain: a systematic review. Annales de Réadaptation et de Médecine Physique. 2007;50(6):425-429. (PubMed)
  9. Giertych A, Crane J, Goozeé S, et al. Clinical Effectiveness of a Functional Restoration Program Compared to Conventional Medical Management in Patients With Chronic Pain: A Multicenter, Retrospective Observational Analysis. American Journal of Physical Medicine & Rehabilitation. 2025;104(8):735-742. doi:10.1097/PHM.0000000000002713. (PubMed)
  10. Jacob L, Heslot C, Ribau M, et al. Long-term outcomes after a functional restoration program for non-specific chronic low back pain: A 10-year longitudinal study. Joint Bone Spine. 2025;92(5):105941. doi:10.1016/j.jbspin.2025.105941. (PubMed)

Why Does T11 Still Hurt After Kyphoplasty? Normal Soreness vs. Warning Signs

Kyphoplasty is usually performed because a vertebral compression fracture hurts enough to interfere with walking, sleeping, standing, or ordinary daily activities. So it can be unsettling to wake up after a T11 kyphoplasty and discover that the back is not completely pain-free.

A certain amount of discomfort after kyphoplasty is expected. The needle has passed through the skin and back muscles to reach the fractured vertebra, and those tissues can remain sore for a few days. In many patients, however, the deeper pain caused by the T11 compression fracture begins to improve fairly quickly—sometimes almost immediately and often within the first day or two.[1,2]

The more important question is not simply, “Do I have pain after T11 kyphoplasty?” It is:

What kind of pain is it, where is it located, when did it begin, and is it improving or getting worse?

Pain that feels like bruising around the needle site and improves over several days is very different from severe back pain that disappears after kyphoplasty and then suddenly returns a week later. Likewise, new leg weakness, numbness, fever, or shortness of breath should not be dismissed as part of normal recovery.

Persistent pain after kyphoplasty can have several causes. Some are temporary and relatively harmless. Others, such as another vertebral compression fracture, infection, nerve compression, or a significant cement leak, need further medical evaluation.[3,4]

Understanding these differences can make the recovery period much less confusing.

Is Pain Normal After T11 Kyphoplasty?

Yes. Some pain after T11 kyphoplasty is normal, particularly during the first few days.

Kyphoplasty is minimally invasive, but it still involves passing a needle or trocar through the skin, muscles, and other tissues of the back before entering the T11 vertebral body. The procedure itself can therefore produce localized tenderness or soreness.

Typical early discomfort may include:

  • Tenderness where the needle entered the back
  • Mild aching around the treated area
  • A bruised sensation
  • Muscle soreness
  • Discomfort when lying directly against the treatment area
  • Mild pain when changing position

Procedure-related pain generally diminishes within approximately two to three days.[1] Patients may also use an ice pack over the needle-entry area for short periods when advised by their treating team.[1]

What matters is the direction in which the pain is moving.

Normal post-kyphoplasty soreness should generally become less noticeable with time rather than progressively more severe.

How Long Should Pain Last After T11 Kyphoplasty?

There are really two different types of pain to think about after T11 kyphoplasty:

  1. Pain created by the procedure itself
  2. Pain from the original T11 compression fracture

The first usually lasts only a few days.

The second may improve very rapidly if the fractured T11 vertebra was truly the main pain generator and was successfully stabilized.

Some patients experience substantial relief shortly after kyphoplasty. In others, the reduction in fracture pain develops over the following 24 to 48 hours.[1,3]

Research comparing balloon kyphoplasty with conservative care has also found that pain improvement can persist beyond the immediate postoperative period. A 2025 systematic review found greater pain reduction after balloon kyphoplasty at one, three, six, and 12 months, with the largest difference seen during the first month.[5]

That does not mean every patient should be pain-free within 48 hours.

A person may still have muscular soreness, stiffness, other degenerative spinal conditions, or pain from a second fracture. The important issue is whether the severe mechanical pain that prompted the kyphoplasty has meaningfully improved.

What Does Normal Pain After T11 Kyphoplasty Usually Feel Like?

Normal early post-procedure pain is generally fairly localized.

The area may feel tender when touched or when the patient lies against a chair or mattress. There may be a dull muscular ache around the lower thoracic spine.

T11 is located toward the lower end of the thoracic spine, close to the transition into the lumbar region. For that reason, patients may describe discomfort in the lower mid-back rather than directly identifying it as “T11 pain.”

A reassuring pattern would be:

  • Mild to moderate soreness immediately after the procedure
  • Tenderness around the needle-entry point
  • Gradual reduction in soreness over two or three days
  • Improvement in the deeper pain that occurred when standing and walking before treatment
  • Increasing ability to move around comfortably

The pain does not have to disappear overnight for the procedure to have worked.

When Is Pain After T11 Kyphoplasty More Concerning?

Pain deserves further attention when it behaves differently from expected postoperative soreness.

Examples include:

  • Severe pain that does not begin to improve
  • Pain that becomes progressively worse
  • Sudden new pain after several pain-free or relatively comfortable days
  • Pain at a different spinal level
  • New pain following a minor fall, bend, twist, or lifting movement
  • Pain associated with fever or wound changes
  • Pain accompanied by new numbness or weakness
  • Pain radiating around the trunk or into the legs
  • New difficulty walking

Persistent pain following kyphoplasty is not explained by a single cause. A recent 2026 review identified several possible contributors, including new vertebral fractures, cement distribution issues, cement leakage, fracture nonunion, injury to surrounding structures, and patient-specific factors such as severe osteoporosis.[4]

The timing and character of the pain can provide important clues.

1. The T11 Fracture May Still Be Painful

Kyphoplasty stabilizes a vertebral compression fracture, but every patient’s fracture is different.

There may occasionally be residual pain originating from the treated vertebral level, particularly if the fracture was complex, treatment occurred relatively late, healing was impaired, or the cement did not provide optimal mechanical stabilization throughout the painful portion of the vertebra.

Recent research into persistent pain after kyphoplasty has identified inadequate cement distribution as one factor associated with poorer outcomes. When cement does not adequately support important areas of the fractured vertebral body, mechanical stress and vertebral re-collapse may contribute to continued pain.[4]

Delayed treatment has also been associated in some studies with less favorable pain relief, although the ideal timing of kyphoplasty remains individualized.[4]

This is one reason persistent focal tenderness directly over T11 may prompt the physician to review the procedure images and obtain additional imaging when necessary.

2. A New Vertebral Compression Fracture Can Cause Pain After Kyphoplasty

One of the most important causes of new pain after apparently successful T11 kyphoplasty is another vertebral compression fracture.

Imagine a patient who has severe T11 pain before surgery. Kyphoplasty is performed, and the pain improves dramatically. A week or several weeks later, severe pain suddenly develops again.

The natural assumption may be that something has gone wrong with T11.

But the new pain could actually be coming from T10, T12, or another vertebra.

People who develop one osteoporotic vertebral compression fracture already have an increased risk of developing additional fragility fractures because the underlying bone weakness remains present.[8]

A new fracture may occur after:

  • A minor fall
  • Bending forward
  • Twisting
  • Lifting something
  • Coughing or sneezing in severe osteoporosis
  • An apparently ordinary movement
  • No memorable triggering event at all

In a study examining pain after vertebral augmentation, some patients with recurrent pain were found to have developed a new thoracic or lumbar vertebral compression fracture.[6]

Therefore, pain relief followed by sudden recurrence of severe focal back pain is a pattern worth reporting to the treating physician.

Does Kyphoplasty Cause Adjacent Vertebral Fractures?

This question has been debated for years.

It has been proposed that placing hardened bone cement into one vertebra could alter the way forces are distributed through nearby vertebrae, potentially increasing stress on the levels above and below.

However, patients receiving kyphoplasty generally already have osteoporosis and a history of vertebral fracture—two powerful reasons why additional fractures may occur even without the procedure.

Current evidence has not conclusively shown that balloon kyphoplasty itself causes a significant increase in new vertebral compression fractures compared with conservative treatment. A 2025 systematic review found no statistically significant difference in new vertebral fracture risk between the kyphoplasty and conservatively treated groups.[5]

Therefore, if T12 fractures after T11 kyphoplasty, it should not automatically be assumed that the cement in T11 caused it.

The underlying osteoporosis may be the larger problem.

3. Persistent Pain May Come From the Facet Joints Rather Than T11

This is an easily overlooked reason for pain after kyphoplasty.

Not every person with back pain after vertebral augmentation continues to hurt because the treated vertebra is still fractured.

A compression fracture changes the shape and biomechanics of the spine. The altered posture and loading can place additional stress on the small facet joints at the back of the spinal column.

In one study of 124 patients who underwent vertebral augmentation, persistent or recurrent back pain not attributable to a new compression fracture or failed procedure occurred in 23 percent. Among those patients, the pain most commonly originated from the facet joints and/or sacroiliac joints.[6]

This finding is particularly useful clinically because patients often assume that any back pain following kyphoplasty means, “The kyphoplasty didn’t work.”

That may not be true.

The original T11 fracture may have been successfully stabilized while a different structure has become the new pain generator.

Facet-related pain may feel more off-center than the original fracture pain and may be aggravated by particular movements, especially extension or rotation.

4. Muscle Pain and Deconditioning Can Continue After the Fracture Is Stabilized

A painful T11 compression fracture can cause a person to move differently for days or weeks before treatment.

They may:

  • Walk with a guarded posture
  • Avoid standing upright
  • Spend more time in bed or in a chair
  • Stop exercising
  • Use the arms excessively when getting up
  • Hold the muscles around the fracture constantly tense

The vertebra may be stabilized during kyphoplasty, but the muscles do not instantly forget several weeks of guarding.

Muscular pain, weakness, fatigue, and altered posture can therefore continue after the fracture pain improves.

The thoracolumbar fascia and other soft tissues surrounding the fracture have also been investigated as potential contributors to residual pain after vertebral compression fracture and kyphoplasty.[4,5]

This type of pain may become more noticeable as patients begin increasing their activity.

For example, someone who could barely walk before kyphoplasty may suddenly start walking much farther because the severe fracture pain has disappeared. The deconditioned back muscles can become sore even though the vertebra itself is doing well.

5. Pre-Existing Arthritis or Disc Problems May Become More Noticeable

Kyphoplasty treats a painful vertebral compression fracture. It does not treat every abnormality visible on spinal imaging.

An older patient with an osteoporotic T11 fracture may also have:

  • Thoracic or lumbar spondylosis
  • Facet joint arthritis
  • Degenerative disc disease
  • Spinal stenosis
  • Scoliosis
  • Sacroiliac joint pain
  • Chronic muscular back pain

Before kyphoplasty, the severe fracture pain may dominate everything else.

Once that pain improves, an older underlying ache may become noticeable again.

Studies evaluating pain after vertebral augmentation have found that delayed pain can frequently be associated with pre-existing degenerative spinal disease rather than the successfully treated vertebral fracture.[6,7]

This distinction matters because another kyphoplasty would not help pain caused by arthritis or spinal stenosis.

6. Cement Leakage Can Cause Pain After Kyphoplasty

The bone cement injected during kyphoplasty is intended to remain within the vertebral body.

A small amount can sometimes escape beyond the borders of the vertebra. This is called cement leakage or cement extravasation.

Cement leakage is one of the most frequently identified imaging findings associated with vertebroplasty and kyphoplasty, but an important point often gets lost when patients read about it online:

Most small cement leaks do not cause symptoms.[1,9]

A 2024 systematic review comparing kyphoplasty and vertebroplasty identified cement leakage on imaging in both procedures, but none of the leaks in the studies included in that review resulted in the major leak-related complications being investigated.[9]

Problems become more concerning when cement travels into a location where it can affect a nerve, the spinal canal, or a blood vessel.

Depending on where the leakage occurs, symptoms could potentially include:

  • New radiating pain
  • Numbness
  • Tingling
  • Muscle weakness
  • Neurological symptoms
  • Rarely, breathing problems if cement enters the pulmonary circulation

Symptomatic cement leakage is therefore very different from an incidental, tiny leak seen on an image.

7. New Nerve Pain After T11 Kyphoplasty Needs Attention

A typical uncomplicated vertebral compression fracture mainly causes localized axial back pain.

New neurological symptoms after kyphoplasty are different.

These may include:

  • Burning or shooting pain
  • Numbness
  • Tingling
  • Leg weakness
  • Difficulty coordinating walking
  • Unusual sensations wrapping around the chest or abdomen

Possible explanations include irritation or compression of neural structures from the fracture, needle placement, bleeding, swelling, or cement extending toward the spinal canal or neural foramen.

Posterior cement leakage can potentially compress neural structures, although serious neurological complications are rare.[10]

Because T11 lies relatively close to the spinal cord, new neurological symptoms should not simply be watched at home for several days without medical advice.

8. Infection Is Rare but Can Cause Increasing Pain

Infection following kyphoplasty is uncommon, but it is one reason progressively worsening pain after an initially uneventful recovery deserves attention.

Possible warning signs include:

  • Increasing pain rather than decreasing pain
  • Fever
  • Chills
  • Redness around the needle-entry site
  • Swelling
  • Drainage
  • Increasing tenderness
  • Feeling generally unwell

The infection risk associated with vertebral augmentation is considered low, but infection involving the vertebra or disc can become serious if it occurs.[1]

Pain that is becoming worse several days after surgery, particularly when accompanied by fever or wound changes, should therefore be reported.

9. Fracture Nonunion or Vertebral Re-Collapse Can Cause Persistent Pain

Although kyphoplasty is designed to stabilize the vertebral body, some patients can continue to have structural problems at the treated level.

Persistent movement at areas of incompletely healed fracture, inadequate internal stabilization, poor bone quality, and vertebral re-collapse have all been explored as explanations for ongoing pain after kyphoplasty.[4]

Very severe osteoporosis may make the situation more complicated because the surrounding bone is fragile even after cement has been injected.

This type of problem cannot be diagnosed from symptoms alone. Imaging and examination are needed to determine whether the treated T11 vertebra remains the source of pain.

Pain That Returns After Initially Successful T11 Kyphoplasty

The timing of recurrent pain can be particularly informative.

Consider this pattern:

Before surgery, standing produces severe focal lower thoracic pain. After T11 kyphoplasty, the patient is dramatically better for several days. Then a new episode of severe pain develops.

That pattern is different from someone whose original pain never improved at all.

Pain that returns after a pain-free interval can be caused by:

  • A new vertebral compression fracture
  • Facet joint pain
  • A new musculoskeletal injury
  • Degenerative spinal pain
  • Less commonly, a kyphoplasty-related complication

Research into post-vertebral augmentation pain has specifically distinguished persistent pain, which never meaningfully resolves, from recurrent pain, which appears after an interval of improvement.[6]

That distinction can be useful when describing symptoms to the physician.

How Do Doctors Investigate Persistent Pain After T11 Kyphoplasty?

There is no single test for “failed kyphoplasty.”

Evaluation begins by determining whether the current pain resembles the original fracture pain.

The physician may ask:

  • Did the original pain improve after kyphoplasty?
  • How long did the improvement last?
  • Is the current pain in exactly the same place?
  • Is there tenderness directly over T11?
  • Did the new pain begin suddenly?
  • Was there a fall or twisting event?
  • Is the pain central or off to one side?
  • Does it radiate?
  • Are numbness or weakness present?
  • Is there fever?

The physical examination can help identify whether the pain appears to arise from the vertebra, muscles, facet joints, nerves, or another structure.

X-Rays

X-rays may show whether another vertebra has developed new compression or whether the treated T11 vertebra has changed.

Magnetic Resonance Imaging

Magnetic resonance imaging can be particularly useful when doctors suspect a new vertebral compression fracture. It can help determine whether a fracture is recent and can also evaluate the spinal canal, nerves, discs, infection, and other soft tissues.

Computed Tomography

Computed tomography provides detailed visualization of bone and may be useful when assessing the treated vertebral body, cement distribution, cortical bone, or suspected cement leakage.

The choice of imaging depends on the patient’s symptoms and what the physician suspects.

What Can Help With Normal Soreness After T11 Kyphoplasty?

For uncomplicated post-procedure soreness, recovery is usually fairly straightforward.

Patients should follow the individual instructions provided by their treating physician.

Common measures include:

  • Using prescribed or approved pain medication
  • Applying ice to the needle-entry area
  • Gradually increasing activity
  • Avoiding strenuous exertion during early recovery
  • Avoiding heavy lifting until cleared
  • Keeping the procedure site appropriately protected
  • Attending scheduled follow-up

Guidance for kyphoplasty commonly recommends gradual return to regular activities while avoiding strenuous activity and heavy lifting during early recovery.[1,2]

One of the more common mistakes after successful kyphoplasty is actually doing too much too soon.

If severe fracture pain disappears quickly, a patient may feel ready to clean the house, lift groceries, garden, or resume exercise immediately. The treated fracture may be stabilized, but surrounding muscles may still be weak and other osteoporotic vertebrae remain vulnerable.

When Should You Call the Doctor About Pain After T11 Kyphoplasty?

Contact the treating physician if:

  • Pain remains severe instead of gradually improving
  • Pain becomes noticeably worse after the first few days
  • Severe pain returns after an initial period of relief
  • A new area of the spine becomes painful
  • Pain begins after a fall, bend, or lifting episode
  • New radiating pain develops
  • The procedure site becomes increasingly red or swollen
  • There is drainage from the procedure site
  • Fever develops

These symptoms do not automatically mean a serious complication has occurred, but they may justify examination or repeat imaging.

When Is Pain After Kyphoplasty an Emergency?

Certain symptoms need more urgent assessment.

Seek urgent medical attention for:

  • New or rapidly worsening leg weakness
  • Significant new numbness
  • Loss of bowel or bladder control
  • Inability to walk because of neurological symptoms
  • Severe rapidly worsening pain accompanied by neurological changes
  • Severe shortness of breath
  • Chest pain
  • Collapse or loss of consciousness

Cement entering the pulmonary circulation is a rare potential complication of vertebral augmentation, while cement or other material entering the spinal canal can potentially affect the spinal cord or nerves.[10]

These serious complications are uncommon, but symptoms involving breathing or neurological function should not be treated as routine post-kyphoplasty soreness.

Why Treating Osteoporosis Matters When Pain Returns

When T11 fractured because of osteoporosis, evaluating recurrent pain is only part of the problem.

The patient has already demonstrated that the spine is vulnerable to fragility fracture.

A recent vertebral fracture is associated with a particularly high risk of another fragility fracture during the following period, and current osteoporosis guidance recommends prompt assessment and treatment of fracture risk.[8]

Depending on the individual, prevention may include:

  • Bone density testing
  • Calcium and vitamin D assessment
  • Medication to strengthen bone
  • Weight-bearing exercise when appropriate
  • Muscle strengthening
  • Balance training
  • Fall prevention
  • Evaluation for secondary causes of osteoporosis
  • Review of medications that may contribute to bone loss

Kyphoplasty strengthens the treated vertebral level. It does not make the rest of the spine resistant to fracture.

For someone developing recurrent pain after T11 kyphoplasty, osteoporosis management is therefore not an optional side issue—it is part of preventing the next painful episode.

Frequently Asked Questions About Pain After T11 Kyphoplasty

Is it normal to still have pain three days after T11 kyphoplasty?

Yes. Mild soreness around the needle-entry site can persist for two or three days after the procedure.[1]

The important question is whether the overall pain is improving. Severe pain that is progressively worsening rather than settling deserves medical review.

Why does my T11 still hurt after kyphoplasty?

Possible reasons include normal postoperative soreness, residual pain from the fracture, poor bone quality, incomplete fracture healing, muscle pain, another spinal pain generator, a new compression fracture, or less commonly a procedure-related complication.[4,6]

Persistent pain does not automatically mean the kyphoplasty failed.

What if I felt better after kyphoplasty but the pain suddenly came back?

A new vertebral compression fracture is one important possibility, particularly in someone with osteoporosis. New facet or muscular pain and other spinal conditions can also cause recurrent symptoms.[6]

Sudden significant pain after a pain-free interval should be discussed with the treating physician, especially if there is focal tenderness over a different vertebral level.

Can T12 fracture after T11 kyphoplasty?

Yes. T12 or another vertebra can develop a compression fracture after T11 has been treated.

However, current evidence does not clearly show that balloon kyphoplasty itself significantly increases the overall risk of new vertebral fractures compared with conservative treatment.[5] Osteoporosis remains an important underlying reason additional fractures occur.

Does cement leakage always cause pain?

No.

Small cement leaks seen on imaging are often asymptomatic. Symptoms become more concerning when cement reaches a location where it can irritate or compress neural structures or enter the circulation.[9,10]

Does persistent pain mean T11 kyphoplasty failed?

Not necessarily.

Research has shown that some patients with persistent or recurrent pain after vertebral augmentation actually have pain originating from other structures, such as facet joints or other areas of the spine.[6,7]

Determining the source of the pain is more useful than simply labeling the procedure a failure.

The Bottom Line

Some pain after T11 kyphoplasty is expected.

Tenderness and a bruised or aching feeling around the needle-entry area commonly last for a few days. At the same time, the deeper pain caused by the T11 compression fracture often begins to improve within the first 24 to 48 hours.[1,3]

What deserves more attention is pain that does not follow that pattern.

Severe pain that never improves may mean the original fracture is still painful or that another structure was contributing to the symptoms all along. Pain that disappears and then suddenly returns raises the possibility of a new vertebral compression fracture. Pain accompanied by fever, wound drainage, new weakness, numbness, or breathing problems requires more urgent evaluation.

Perhaps the most important thing to remember is that back pain after kyphoplasty does not automatically mean the procedure failed.

The treated T11 vertebra is only one possible pain generator. Muscles, facet joints, degenerative spinal disease, another vertebral fracture, and the underlying osteoporosis can all influence how a person feels after treatment.

Instead of judging the outcome by whether there is absolutely no pain, look at the pattern: Is the original pain better? Is mobility improving? Is the remaining soreness settling? Or has something new appeared?

Those questions often provide a much clearer picture of whether recovery is proceeding normally or whether the spine needs another look.

References:

  1. Radiological Society of North America and American College of Radiology. Vertebroplasty and Kyphoplasty. RadiologyInfo.org. Last reviewed June 1, 2026. (Radiologyinfo.org)
  2. MedlinePlus Medical Encyclopedia. Kyphoplasty. U.S. National Library of Medicine. Review date September 2, 2025. (MedlinePlus)
  3. Johns Hopkins Medicine. Kyphoplasty. Johns Hopkins Medicine. (Hopkins Medicine)
  4. Cao H, Li LW, Yao M, et al. Exploration of Causes for Persistent Pain after Percutaneous Kyphoplasty in Osteoporotic Vertebral Compression Fractures. SN Comprehensive Clinical Medicine. 2026;8:286. Published July 6, 2026. doi:10.1007/s42399-026-02508-3. (DOI)
  5. Encalada S, Hunt C, Duszynski B, et al. The effectiveness of balloon kyphoplasty compared to conservative treatment for osteoporotic vertebral compression fractures: A systematic review and meta-analysis. Interventional Pain Medicine. 2025;4(1):100569. doi:10.1016/j.inpm.2025.100569. (PubMed Central (PMC))
  6. Kamalian S, Bordia R, Ortiz AO. Post-Vertebral Augmentation Back Pain: Evaluation and Management. American Journal of Neuroradiology. 2012;33(2):370-375. doi:10.3174/ajnr.A2775. (PubMed Central (PMC))
  7. Hatgis J, Granville M, Jacobson RE. Evaluation and Interventional Management of Pain After Vertebral Augmentation Procedures. Cureus. 2017;9(2):e1078. (PubMed Central (PMC))
  8. National Osteoporosis Guideline Group. Clinical Guideline for the Prevention and Treatment of Osteoporosis: Summary of Main Recommendations. Updated September 2024. (NOGG)
  9. Rose LD, Bateman G, Ahmed A. Clinical significance of cement leakage in kyphoplasty and vertebroplasty: a systematic review. European Spine Journal. 2024;33(4):1484-1489. doi:10.1007/s00586-023-08026-3. (PubMed)
  10. Margetis K, Korfias S, Boutos N, et al. Percutaneous Vertebroplasty and Kyphoplasty. StatPearls. National Center for Biotechnology Information Bookshelf. (NCBI)

T11 Compression Fracture Kyphoplasty: Recovery Time, Pain Relief, and What to Expect

A compression fracture at T11 can make even simple movements surprisingly difficult. Getting out of bed, standing at the kitchen counter, walking across a room, bending to put on shoes, or riding in a car may trigger sharp pain in the middle or lower back. For some people, the fracture follows a fall or another obvious injury. For others, particularly those with osteoporosis, the vertebra may fracture during an everyday movement without any major trauma.

When a painful T11 compression fracture does not improve adequately with conservative treatment, kyphoplasty may be considered. Kyphoplasty is a minimally invasive procedure in which a balloon is introduced into the fractured vertebral body to create a cavity, followed by injection of medical-grade bone cement to stabilize the weakened bone.[1,3]

For patients considering the procedure, the biggest questions are usually practical ones: How quickly will the pain improve? How long does T11 kyphoplasty recovery take? When can I walk, drive, work, or exercise again?

The encouraging part is that recovery from the procedure itself is often relatively quick. Many patients are able to walk within hours, and some experience substantial pain relief within the first few days.[1,4] But complete recovery involves more than waiting for the small puncture site to heal. Restoring strength, returning safely to normal activities, and treating the osteoporosis or other condition responsible for the fracture are equally important.

What Is a T11 Compression Fracture?

The thoracic spine contains 12 vertebrae, numbered T1 through T12. T11 is located near the bottom of the thoracic spine, just above T12 and the lumbar spine.

A T11 compression fracture occurs when the vertebral body loses structural strength and partially collapses. Instead of maintaining its normal height and shape, the front or central portion of the vertebra may become compressed.

Osteoporosis is the most common cause of vertebral compression fractures, particularly in older adults. As bone density and strength decrease, the vertebrae become vulnerable to fractures that may occur after relatively minor stresses.[2]

Other causes of a T11 compression fracture can include:

  • A fall
  • Motor vehicle trauma
  • A direct blow to the back
  • Cancer that has spread to the spine
  • Multiple myeloma
  • Long-term corticosteroid use
  • Metabolic conditions that weaken the bones

When osteoporosis is severe, a person does not necessarily need to fall to develop a compression fracture. Bending, lifting, twisting, coughing, or another ordinary activity may sometimes be enough to fracture a weakened vertebra.

Multiple vertebral compression fractures can eventually lead to loss of height and an increasingly forward-curved posture known as kyphosis.[2]

What Does a T11 Compression Fracture Feel Like?

Pain from a T11 compression fracture is commonly felt around the lower part of the mid-back, although discomfort can spread toward the sides of the trunk.

The pain may appear suddenly after an injury or develop more gradually in someone with osteoporosis.

Common symptoms include:

  • Sharp or aching pain around the lower thoracic spine
  • Pain that worsens when standing or walking
  • Difficulty getting into or out of bed
  • Pain when bending or changing position
  • Localized tenderness over the T11 area
  • Muscle spasms around the injured vertebra
  • Reduced ability to perform daily activities
  • Loss of height after significant vertebral collapse

Vertebral compression fracture pain is often more noticeable when the spine is bearing weight and may decrease when the person lies down.[2]

Most osteoporotic compression fractures do not injure the spinal cord. However, new leg weakness, numbness, difficulty walking, or loss of bowel or bladder control requires urgent medical evaluation, because these symptoms can indicate neurological involvement.[2,6]

How Is a T11 Compression Fracture Diagnosed?

Diagnosis usually begins with the patient’s symptoms, medical history, physical examination, and spinal imaging.

An X-ray may show that the T11 vertebral body has lost height or developed the wedge-shaped appearance typical of a compression fracture.

However, simply seeing a compressed vertebra on an X-ray does not always prove that it is responsible for the patient’s current pain. An older fracture may remain visible long after it has healed.

Magnetic resonance imaging can be particularly useful when doctors need to determine whether the fracture is recent or active. It can also help evaluate the spinal canal, nerves, surrounding tissues, and possible causes such as a tumor.

Computed tomography provides more detailed information about the bony anatomy and may be especially useful following significant trauma.[2]

If osteoporosis is suspected, bone density testing and evaluation for causes of bone loss may also be recommended. A vertebral fragility fracture is important not only because of the immediate pain but also because it indicates an increased risk of additional fractures.[6,7]

Does Every T11 Compression Fracture Need Kyphoplasty?

No. Finding a T11 compression fracture does not automatically mean that kyphoplasty should be performed.

Many vertebral compression fractures improve with nonsurgical treatment. Depending on the circumstances, initial treatment can include:

  • Pain medication
  • Temporary modification of activities
  • Gradual return to movement
  • Physical therapy
  • Osteoporosis treatment
  • A spinal brace in selected patients

Most compression fractures caused by injury can heal over several weeks, and many osteoporotic compression fractures also become less painful with conservative care.[2]

Kyphoplasty is generally considered when the treating physician determines that the fracture is the likely source of significant persistent pain and that vertebral stabilization is appropriate.

Potential reasons for considering kyphoplasty include:

  • Severe pain that remains disabling
  • Difficulty standing or walking because of the fracture
  • Inadequate improvement with conservative treatment
  • Imaging showing a recent or incompletely healed painful fracture
  • Inability to tolerate prolonged immobility
  • A painful vertebral fracture related to certain cancers or multiple myeloma

The timing of kyphoplasty is individualized. Some guidance suggests that vertebral augmentation is most likely to be effective when performed relatively early in an active painful fracture rather than after the fracture has completely healed.[1]

Most importantly, the pain should actually be coming from the fractured vertebra. Kyphoplasty does not treat other causes of back pain such as spinal arthritis, disc disease, spinal stenosis, or muscular pain.[1,4]

What Happens During T11 Kyphoplasty?

Kyphoplasty is performed through a small puncture rather than a large surgical incision.

The patient typically lies face down. Depending on the patient’s health and the physician’s preference, the procedure may be performed using local anesthesia with sedation or general anesthesia.[3]

Using real-time X-ray guidance, the physician passes a hollow needle through the skin and into the T11 vertebral body.

A small inflatable balloon is then passed through the needle and positioned inside the fractured vertebra. The balloon is carefully inflated. This creates a cavity within the vertebral body and may restore some of the height lost when the vertebra collapsed.

The balloon is then deflated and removed.

Medical-grade bone cement is injected into the cavity. The cement hardens rapidly and stabilizes the fractured vertebra.[1,3]

Treatment of a single vertebral level commonly takes less than an hour, although the patient will spend additional time at the medical facility for preparation, anesthesia, monitoring, and recovery.[4]

How Does T11 Kyphoplasty Reduce Pain?

A fractured vertebral body contains damaged bone that can move slightly when the spine is loaded. This instability can stimulate pain whenever a person stands, walks, bends, or changes position.

Kyphoplasty stabilizes the fractured area with bone cement. By limiting painful movement within the fractured vertebra, the procedure can substantially reduce fracture-related pain.[1]

The balloon may also partially restore vertebral height in some patients. However, restoring height is not always possible and is not the main measure of whether the procedure has been successful.

The main goals are to stabilize the painful fracture, reduce pain, and help the patient regain mobility.

How Quickly Does Pain Improve After T11 Kyphoplasty?

Pain relief can occur surprisingly quickly.

Some patients notice a major difference shortly after the procedure. Others experience progressive improvement over the next 24 to 48 hours. Temporary soreness at the needle insertion site is common and usually settles within a few days.[1,4]

A 2025 systematic review and meta-analysis comparing balloon kyphoplasty with conservative treatment for painful osteoporotic vertebral compression fractures found greater pain reduction following kyphoplasty at one, three, six, and 12 months. The largest difference was observed during the first month after treatment. The analysis also found greater improvement in disability during the first three months.[5]

However, kyphoplasty does not guarantee complete pain relief.

The result depends on several factors, including:

  • Whether T11 is truly the primary source of pain
  • How recent the fracture is
  • How much vertebral collapse has occurred
  • Whether another vertebra is also fractured
  • The patient’s bone quality
  • The presence of spinal arthritis or disc degeneration
  • Muscle weakness and deconditioning
  • Other causes of back pain

This is why identifying the painful fracture accurately before the procedure matters so much.

T11 Kyphoplasty Recovery Time: What Happens During the First Few Days?

It helps to think of T11 kyphoplasty recovery as a progression rather than a single recovery date.

The First Few Hours After Kyphoplasty

After the procedure, the patient remains under observation while the effects of anesthesia or sedation wear off.

In uncomplicated cases, patients can often begin walking within approximately an hour. Kyphoplasty is frequently performed as an outpatient procedure, allowing the patient to return home the same day.[1,4]

Some patients may need an overnight stay because of their age, other medical problems, the severity of the fracture, anesthesia concerns, or difficulty with mobility.

Patients should arrange for someone else to drive them home.

The First 24 to 48 Hours

This is when many patients begin to appreciate the difference between their original fracture pain and temporary soreness from the procedure.

The deep, movement-related pain from the T11 compression fracture may be substantially reduced. At the same time, there can be tenderness where the needle passed through the skin and back muscles.

Procedure-related soreness usually improves within approximately two to three days.[4]

Short periods of walking are generally preferable to remaining in bed for prolonged periods once the treating physician has cleared the patient for activity.

The First Week After T11 Kyphoplasty

During the first week, basic daily activities may become noticeably easier.

Patients may find that they can:

  • Walk around the house more comfortably
  • Stand for longer periods
  • Get into and out of bed more easily
  • Perform light personal care
  • Sit more comfortably
  • Reduce their reliance on pain medication

The reduction in pain can sometimes create a false sense that the spine is completely back to normal.

This is an important point: rapid pain relief does not mean the underlying bone weakness has disappeared.

Kyphoplasty stabilizes the T11 fracture. It does not immediately strengthen every other vertebra or cure osteoporosis.

T11 Kyphoplasty Recovery at Two to Six Weeks

During the following weeks, activity can generally be increased gradually according to symptoms and the treating physician’s recommendations.

Walking is often one of the simplest and most useful ways to restore activity tolerance.

Someone who had been significantly limited for several weeks before the procedure may have lost considerable strength and endurance. Even though the fracture pain improves quickly, the muscles may need longer to recover.

Exercise programs after vertebral fracture can include progressive muscle strengthening, back extensor strengthening, endurance training, posture work, and instruction in safer movements.[6]

Patients should not assume that they need to remain inactive for six weeks simply because they had a spinal procedure. At the same time, strenuous exercise, repeated bending, twisting, or heavy lifting should not be resumed simply because the pain has disappeared.

The appropriate balance depends on the fracture, bone quality, age, and overall health.

How Long Does It Take to Fully Recover From T11 Kyphoplasty?

There is an important difference between recovering from kyphoplasty and recovering from the condition that led to kyphoplasty.

The procedural recovery can be rapid. Many patients walk the same day, return to light activities soon afterward, and experience improvement in fracture pain within days.[1,4]

Functional recovery may take longer.

A patient who was otherwise healthy and mobile before the T11 fracture may regain normal activities relatively quickly. Someone who spent several weeks in bed or avoiding movement because of severe pain may need substantially longer to restore:

  • Leg strength
  • Trunk strength
  • Endurance
  • Balance
  • Walking confidence
  • Normal posture
  • Independence in daily activities

The fracture itself also remains part of the recovery process even after it has been mechanically stabilized.

Therefore, there is no single number such as “three days” or “six weeks” that accurately describes T11 kyphoplasty recovery for everyone.

Can You Walk After T11 Kyphoplasty?

Yes. In uncomplicated cases, walking can often begin shortly after the procedure.[1]

Initially, this may mean simply standing with assistance and walking a short distance.

Once home, several short walks can be easier on the body than one long walk. Distance and duration can then be increased gradually as comfort and confidence improve.

Prolonged bed rest is generally undesirable because inactivity contributes to muscle loss, reduced mobility, and further loss of bone strength. Exercise and gradual restoration of mobility are important parts of recovery after vertebral fracture.[6]

However, patients should follow specific restrictions given by their treating physician, particularly if the T11 fracture resulted from major trauma rather than osteoporosis.

What Should You Avoid After T11 Kyphoplasty?

Individual instructions vary, but patients are commonly advised to avoid strenuous loading of the spine during the early recovery period.

Activities that may need to be limited include:

  • Heavy lifting
  • Repeated forward bending
  • Forceful twisting
  • High-impact exercise
  • Strenuous housework
  • Heavy gardening
  • Sudden jerking movements
  • Activities with a high risk of falling

Restrictions are especially important in patients with osteoporosis. Even though cement stabilizes T11, the vertebrae above and below remain susceptible to fracture if the underlying bone disease has not been addressed.

Patients should also learn safer ways of bending, lifting, and carrying objects. Exercise programs following vertebral fracture should include guidance on adapting everyday movements and improving posture.[6]

How Should You Sleep After T11 Kyphoplasty?

There is no single sleeping position that is best for every patient.

Comfort is usually the main guide, provided the physician has not given specific restrictions.

Some people are more comfortable sleeping on their back with a pillow beneath the knees. Others prefer lying on their side with a pillow between the knees.

Getting into and out of bed can initially be more uncomfortable than lying down itself. Rolling onto the side and using the arms to help push the body upright may reduce unnecessary twisting of the spine.

If a particular position causes sharp or escalating pain, it should not be forced.

When Can You Drive After T11 Kyphoplasty?

Patients should not drive themselves home after kyphoplasty because anesthesia or sedation may impair coordination, reaction time, and judgment.[1,4]

There is no universal day on which everyone can safely begin driving again.

Before returning to driving, the patient should generally be able to:

  • Sit comfortably for the required period
  • Get into and out of the vehicle safely
  • Turn sufficiently to observe surrounding traffic
  • Operate the pedals normally
  • Brake suddenly if necessary
  • Concentrate without significant distraction from pain
  • Avoid medications that impair alertness

The treating physician’s instructions should take priority, especially when prescription pain medication is still required.

When Can You Return to Work After T11 Kyphoplasty?

Return to work depends more on the physical demands of the job than on the small skin puncture from kyphoplasty.

Someone performing sedentary or computer-based work may be able to return relatively soon if sitting is comfortable and pain is controlled.

A patient whose job involves lifting, repeated bending, climbing, pushing, pulling, or physical labor may require a longer period of restriction.

Age, osteoporosis severity, additional fractures, general fitness, and the amount of deconditioning that occurred before treatment can also affect the timeline.

Rather than focusing on a fixed number of days, it is often more useful to ask whether the person can safely perform the specific tasks required by the job.

Do You Need Physical Therapy After T11 Kyphoplasty?

Not every patient requires formal physical therapy immediately after kyphoplasty.

However, physical therapy can be especially helpful when the compression fracture caused prolonged inactivity, loss of strength, impaired balance, or fear of moving.

Rehabilitation may include:

  • Walking progression
  • Balance training
  • Posture education
  • Lower-extremity strengthening
  • Back extensor strengthening
  • Endurance exercises
  • Safe lifting and movement techniques
  • Fall-prevention strategies

Supervised exercise following vertebral fracture can improve pain and physical performance, and current osteoporosis guidance recommends progressive muscle strengthening, including back extensor strengthening or endurance exercise.[6]

The exercise program should be adapted to the individual rather than using a generic back-strengthening routine.

Why Does My Back Still Hurt After T11 Kyphoplasty?

Some pain during the first few days is expected.

Persistent pain several weeks after kyphoplasty, or pain that returns after initially improving, deserves closer evaluation.

Possible explanations include:

  • Soreness of the muscles and surrounding tissues
  • Another vertebral compression fracture
  • A second fracture that was already present
  • Spinal arthritis
  • Disc degeneration
  • Facet joint pain
  • Incomplete relief from the original T11 fracture
  • Postural and muscular changes associated with vertebral collapse
  • Another source of back pain unrelated to the fracture

A particularly important pattern is substantial initial improvement followed by sudden new severe back pain.

People who have already sustained an osteoporotic vertebral fracture remain at increased risk for another fragility fracture, especially in the period following the first fracture.[6,7]

Repeat imaging may therefore be necessary if significant new pain develops.

Can Another Vertebra Fracture After T11 Kyphoplasty?

Yes.

Kyphoplasty strengthens the treated T11 vertebral body, but it does not strengthen every other bone in the spine.

If osteoporosis caused the original fracture, other vertebrae remain vulnerable.

Some patients do develop additional compression fractures following vertebral augmentation. However, a 2025 systematic review found no statistically significant difference in the risk of new vertebral compression fractures between patients receiving balloon kyphoplasty and those treated conservatively.[5]

This is an important distinction. A new fracture occurring after kyphoplasty does not necessarily mean that kyphoplasty caused it. The underlying osteoporosis itself creates a substantial ongoing fracture risk.

What Are the Possible Complications of T11 Kyphoplasty?

Kyphoplasty is minimally invasive, but it is still a medical procedure and complications are possible.

Potential risks include:

  • Bleeding
  • Infection
  • Temporary increase in pain
  • Nerve irritation or injury
  • Allergic or anesthesia-related reactions
  • Bone cement leakage
  • Numbness or tingling
  • New neurological symptoms
  • Additional vertebral fractures

A small amount of bone cement may sometimes leak beyond the vertebral body without producing symptoms. More significant leakage into the spinal canal or blood vessels is uncommon but can potentially result in serious complications.[1,3]

The patient’s fracture pattern, bone quality, underlying disease, anatomy, and overall medical health can all affect the level of risk.

When Should You Call a Doctor After T11 Kyphoplasty?

Mild soreness around the puncture site is usually expected for a short period after kyphoplasty.

Medical attention should be sought for symptoms such as:

  • Increasing redness around the procedure site
  • Increasing swelling
  • Fever
  • Wound drainage
  • Excessive bleeding
  • Severe or progressively worsening back pain
  • New numbness or tingling
  • New weakness in the legs
  • New difficulty walking

Loss of bowel or bladder control, rapidly worsening leg weakness, or another significant neurological change requires urgent assessment.[2,4]

Sudden new back pain after a period of successful pain relief should also be evaluated because another vertebral compression fracture may have occurred.

Osteoporosis Treatment After T11 Kyphoplasty Should Not Be Overlooked

One of the most important parts of recovery actually begins after the T11 fracture has been stabilized.

Kyphoplasty treats the fracture. It does not treat osteoporosis.

A vertebral fragility fracture is an important warning sign that the skeleton may be vulnerable to additional fractures. People with a recent vertebral fracture have an increased risk of experiencing another fragility fracture, which is why current recommendations emphasize prompt investigation and secondary fracture prevention.[6,7]

Depending on the patient, evaluation may involve:

  • Bone density testing
  • Assessment of calcium and vitamin D status
  • Review of medications that may affect bone health
  • Investigation for secondary causes of osteoporosis
  • Fall-risk assessment
  • Dietary changes
  • Weight-bearing and muscle-strengthening exercise
  • Prescription osteoporosis medication

Several types of osteoporosis medication can substantially reduce future vertebral fracture risk in appropriately selected patients.[8]

Therefore, the long-term question after T11 kyphoplasty should not simply be, “Did the procedure relieve the pain?”

It should also be, “Why did T11 fracture, and what are we doing to prevent the next fracture?”

How Successful Is Kyphoplasty for a T11 Compression Fracture?

There is no single success percentage that applies specifically to every T11 compression fracture.

Published kyphoplasty research generally evaluates painful vertebral compression fractures across thoracic and lumbar levels rather than treating T11 as a separate category.

The best results are more likely when there is a clear relationship between the patient’s pain and a recent vertebral compression fracture.

A 2025 systematic review and meta-analysis found moderate-certainty evidence that balloon kyphoplasty provided greater pain relief than conservative treatment at one, three, six, and 12 months, with the largest benefit during the first month. Improvement in disability was also greater during the first three months.[5]

At the same time, medical guidance is not completely uniform. Some osteoporosis guidelines do not recommend routine balloon kyphoplasty for every painful osteoporotic vertebral fracture, noting that clinical trials have not consistently demonstrated benefit across all patient populations.[6]

These positions are not necessarily contradictory.

Kyphoplasty is not meant to be an automatic treatment whenever an X-ray shows a compressed vertebra. The decision becomes much more individualized when the patient has:

  • A recent fracture
  • Severe localized pain
  • Significant functional limitation
  • Imaging findings consistent with the painful level
  • Persistent symptoms despite appropriate conservative treatment
  • Difficulty tolerating prolonged inactivity

In other words, careful patient selection is central to the outcome.

Frequently Asked Questions About T11 Compression Fracture Kyphoplasty

Is T11 kyphoplasty considered major back surgery?

No. Kyphoplasty is considered a minimally invasive procedure. The vertebra is accessed through a small puncture in the skin rather than through a large surgical incision.[1,4]

How long does T11 kyphoplasty take?

Treatment of one vertebral level commonly takes less than an hour. However, the total time spent at the hospital or outpatient center will be longer because of preparation, anesthesia, monitoring, and postoperative recovery.[4]

Is pain relief immediate after T11 kyphoplasty?

It can be. Some patients notice improvement very soon after treatment, while others experience more gradual relief during the next day or two. Temporary soreness caused by the procedure may persist for several days.[1,4]

Can you go home the same day after T11 kyphoplasty?

Yes. Many uncomplicated kyphoplasty procedures are performed on an outpatient basis, allowing the patient to return home the same day.[1,4]

Some patients may need to remain overnight depending on their medical condition and mobility.

Can a T11 compression fracture heal without kyphoplasty?

Yes. Many vertebral compression fractures improve without vertebral augmentation. Treatment may include pain control, activity modification, rehabilitation, osteoporosis management, and sometimes bracing.[2]

Kyphoplasty is generally considered for selected patients rather than being required for every compression fracture.

Does kyphoplasty completely restore the height of T11?

Not necessarily.

The balloon used during kyphoplasty may restore some vertebral height, particularly when the fracture is relatively recent. Complete restoration is not guaranteed, and an older vertebra that has already healed in a collapsed position is less likely to regain height.[1]

Pain relief and improved function are generally more clinically important than achieving a perfectly shaped vertebra on an X-ray.

Does the cement eventually dissolve?

The bone cement used for kyphoplasty is intended to remain in the vertebral body permanently. It provides lasting structural support to the treated area.[1]

Can T11 collapse again after kyphoplasty?

Kyphoplasty is designed to stabilize the treated vertebral body and reduce further collapse at the fracture site. However, patients with osteoporosis remain at risk for fractures in other vertebrae.

Will I need a back brace after T11 kyphoplasty?

Not everyone requires a brace. Whether one is recommended depends on the fracture, underlying cause, bone quality, and physician’s judgment.

Current evidence does not support routine bracing for every osteoporotic vertebral compression fracture, although selected patients may experience symptomatic benefit.[6]

The Bottom Line

For someone struggling with severe pain from a T11 compression fracture, kyphoplasty can offer something particularly valuable: the possibility of stabilizing the painful vertebra and becoming mobile again relatively quickly.

Many patients can walk within hours after the procedure, and meaningful pain relief may occur during the first 24 to 48 hours. Procedure-related soreness usually improves within a few days, while return to heavier activity should occur more gradually.[1,4]

But T11 kyphoplasty recovery does not end when the pain disappears.

Someone who spent weeks moving less because of the fracture may still need time to rebuild strength, endurance, balance, and confidence. More importantly, if osteoporosis caused the T11 fracture, the rest of the spine remains vulnerable.

That makes the best recovery plan a combination of fracture stabilization, gradual return to movement, appropriate rehabilitation, and long-term attention to bone health.

Kyphoplasty may stabilize the fractured T11 vertebra. Preventing the next fracture requires treating the person—and the bones—as a whole.

References:

  1. Radiological Society of North America and American College of Radiology. Vertebroplasty and Kyphoplasty. RadiologyInfo.org. Last reviewed June 1, 2026.
  2. MedlinePlus Medical Encyclopedia. Compression Fractures of the Back. U.S. National Library of Medicine.
  3. MedlinePlus Medical Encyclopedia. Kyphoplasty. U.S. National Library of Medicine. Reviewed September 2, 2025.
  4. Cleveland Clinic. Kyphoplasty: What It Is, Purpose, Procedure & Side Effects. Medically reviewed November 30, 2023.
  5. Encalada S, Hunt C, Duszynski B, et al. The effectiveness of balloon kyphoplasty compared to conservative treatment for osteoporotic vertebral compression fractures: A systematic review and meta-analysis. Interventional Pain Medicine. 2025;4(1):100569. doi:10.1016/j.inpm.2025.100569.
  6. National Osteoporosis Guideline Group. Management of Symptomatic Osteoporotic Vertebral Fractures. NOGG Clinical Guideline for the Prevention and Treatment of Osteoporosis.
  7. National Osteoporosis Guideline Group. Summary of Main Recommendations: Clinical Guideline for the Prevention and Treatment of Osteoporosis.
  8. International Osteoporosis Foundation. Treatment of Osteoporosis.

How Long Does Psoas Tendinitis Take to Heal? Exercises, Recovery Timeline, and What to Avoid

Psoas tendinitis can be frustrating for one simple reason: everyday movements keep asking the irritated tendon to work.

You use the iliopsoas every time you lift your thigh, climb stairs, get out of a chair, step into a car or walk uphill. So even after you stop running, playing sports or doing strenuous exercise, the tendon rarely gets complete rest.

That does not mean recovery has to drag on indefinitely.

A relatively recent and mild case of psoas tendinitis may improve noticeably within a few weeks, while a more established iliopsoas tendinopathy often requires 6 to 12 weeks or longer of carefully progressed rehabilitation. Chronic cases can take several months, particularly when the tendon has been repeatedly irritated, the original activity has not been modified, or another hip or back problem is contributing to the symptoms. [1,2]

One published rehabilitation case involving a runner with iliopsoas tendinopathy showed improvement within the first two weeks of a progressive exercise program, but unrestricted running was not achieved until around 12 weeks. The authors also noted that tendinopathies commonly require several weeks of rehabilitation before substantial improvement becomes apparent. [3]

The important point is that psoas tendinitis recovery is not simply a matter of waiting for inflammation to disappear. The tendon needs to tolerate normal daily activity again and, for athletes, eventually tolerate running, jumping, kicking or other high-load movements without repeatedly flaring.

What Is Psoas Tendinitis?

The psoas major is a deep muscle that begins along the lumbar spine and travels through the pelvis. Together with the iliacus muscle, it forms the iliopsoas, one of the body’s main hip flexors.

The iliopsoas helps bring the thigh toward the trunk. It is active when you:

  • Walk and run
  • Climb stairs
  • Lift your knee
  • Get into a car
  • Rise from a chair
  • Kick a ball
  • Sprint uphill
  • Perform many abdominal and leg exercises

Psoas tendinitis refers to irritation involving the iliopsoas tendon. You may also see the condition called iliopsoas tendinitis, iliopsoas tendinopathy or psoas syndrome.

Although these terms are sometimes used interchangeably, tendinopathy is a broader description. Persistent tendon pain is not always caused by ongoing inflammation alone. Chronic overload can produce changes in the tendon that require progressive rehabilitation rather than simply rest and anti-inflammatory treatment. [2,4]

How Long Does Psoas Tendinitis Take to Heal?

There is no single recovery period that applies to everyone.

As a practical guide, recovery may look something like this:

  • A mild, recently developed irritation: symptoms may start settling within 2 to 4 weeks when the aggravating activity is reduced and rehabilitation begins early.
  • More established psoas tendinitis or iliopsoas tendinopathy: improvement commonly requires a structured rehabilitation period of approximately 6 to 12 weeks.
  • Chronic or repeatedly aggravated iliopsoas tendinopathy: recovery may take 3 months or longer.
  • Persistent pain caused by another hip problem, previous hip surgery or mechanical impingement: recovery may be considerably longer and may require treatment beyond exercises alone.

These are ranges rather than deadlines. Iliopsoas-specific recovery research remains limited, and studies do not support telling every patient that the tendon will be healed by an exact week. Rehabilitation research instead supports gradually rebuilding the tendon’s ability to tolerate load. [2,3,5]

A person who has had mild pain for two weeks after suddenly increasing running mileage is in a very different situation from someone who has continued training through groin pain for nine months.

Why Does Psoas Tendinitis Sometimes Take So Long to Heal?

Tendons generally adapt more slowly than muscles.

A sore muscle after an unfamiliar workout may settle within days. An overloaded tendon may continue reacting when it is repeatedly exposed to more force than it can currently tolerate.

The iliopsoas also presents another problem: it is difficult to completely unload.

Even without exercising, the iliopsoas works during routine activities such as walking and climbing stairs. Sitting also keeps the hip in a flexed position for prolonged periods, while standing and walking require the hip to move back toward extension.

Several factors can therefore slow psoas tendinitis recovery.

Continuing the Activity That Started the Pain

A runner who continues hill running, sprint intervals and high mileage may never give the irritated tendon an opportunity to settle.

The same applies to dancers, soccer players, martial artists and people performing frequent leg raises or repetitive hip-flexion exercises.

Usually the goal is not permanent avoidance. It is temporary load reduction followed by a gradual return.

Returning to Exercise Too Quickly

Feeling better during ordinary walking does not necessarily mean the tendon is ready for sprinting or repeated high-knee exercises.

Tendon rehabilitation works best when loading progresses in stages. Sudden jumps in training volume or intensity can provoke another flare even after symptoms have improved. [5]

Complete Rest for Too Long

The opposite approach can also create problems.

Rest may calm symptoms temporarily, but prolonged avoidance of activity does not rebuild the strength or load tolerance required for normal movement. Once exercise resumes, the tendon may again encounter more load than it is prepared to handle.

For many people, relative rest is more useful than complete inactivity. This means reducing movements that clearly provoke symptoms while maintaining tolerable activity and progressively rebuilding strength. [2,3]

Stretching an Irritated Psoas Too Aggressively

When the front of the hip feels tight, the instinct is often to stretch it repeatedly.

That is not always helpful.

Hip extension stretches the iliopsoas. If the tendon is highly irritable, repeatedly forcing the hip into a deep lunge or aggressive hip-flexor stretch may continue provoking symptoms.

Stretching can have a place in rehabilitation when there is genuine loss of flexibility, but it should not produce increasing groin pain afterward.

The Diagnosis May Be Wrong

Persistent “psoas tendinitis” sometimes turns out to be something else.

Deep groin pain can also occur with:

  • Hip labral tears
  • Femoroacetabular impingement
  • Hip osteoarthritis
  • Adductor injuries
  • Iliopsoas bursitis
  • Stress fractures
  • Lumbar spine disorders
  • Other causes of anterior hip pain

The hip has complex anatomy, and several conditions can exist simultaneously. [6]

If treatment aimed at the psoas repeatedly fails, confirming the diagnosis becomes increasingly important.

Psoas Tendinitis Recovery Timeline: What Usually Happens?

Rather than thinking of recovery as a countdown to a particular date, it is more useful to think of it in phases.

Early Stage: Calm the Flare and Identify What Is Irritating the Psoas

During the first several days to two weeks, the priority is usually to stop repeatedly provoking the tendon.

This may mean temporarily reducing:

  • Running
  • Sprinting
  • Hill workouts
  • Kicking
  • Deep lunges
  • High-knee drills
  • Hanging leg raises
  • Straight-leg raises
  • Repetitive stair climbing
  • Exercises that repeatedly reproduce anterior hip or groin pain

Ice or heat may provide temporary symptom relief for some people. Pain-relieving or anti-inflammatory medication may occasionally be appropriate, but medication should be considered in the context of the person’s medical history rather than automatically used for every tendon problem. [2]

You do not necessarily need to stop walking unless walking itself significantly aggravates symptoms.

Weeks 2 to 6: Restore Comfortable Movement and Begin Controlled Loading

Once ordinary movement becomes more comfortable, rehabilitation generally shifts toward restoring hip and pelvic control and gradually strengthening the muscles surrounding the hip.

Early rehabilitation does not necessarily require aggressively strengthening the psoas itself.

Exercises may initially emphasize muscles that help control the pelvis and hip while placing relatively modest demands on the iliopsoas. Research examining muscle activation during hip rehabilitation has identified several exercises that can strengthen surrounding musculature while limiting excessive iliopsoas activity. [4]

The exact progression depends on pain severity, strength and the person’s usual activities.

Weeks 6 to 12: Build Strength and Tendon Capacity

As symptoms improve, the rehabilitation program becomes more demanding.

The goal now is not merely to remain pain-free around the house. The goal is to prepare the iliopsoas and surrounding muscles for the loads they will eventually need to handle.

Progressive strengthening may include:

  • More challenging bridge variations
  • Hip abductor strengthening
  • Hip extension exercises
  • Controlled hip-flexion strengthening
  • Core and pelvic stabilization
  • Squatting and functional lower-body exercises
  • Balance and single-leg control
  • Gradually increasing walking speed and distance

Athletes may then progress toward sport-specific loading.

A rehabilitation study involving iliopsoas tendinopathy used a staged program that progressed over approximately 12 weeks rather than immediately returning the athlete to unrestricted running. [3]

Beyond 12 Weeks: Return to Running, Sport or Higher-Level Activity

Some people will already have returned to normal activity before this point. Others, especially those with chronic symptoms, may still be rebuilding capacity.

Return to sport should generally be criteria-based rather than date-based.

That means considering whether the person can tolerate progressively demanding movements without significant pain during the activity or a notable flare later that day or the following morning.

Returning to activity is best viewed as a progression from modified participation, to normal participation, and eventually to full performance. Gradual load progression is an important part of reducing the risk of repeated overload. [7]

What Are the Best Exercises for Psoas Tendinitis?

There is no single “best psoas exercise.”

Exercise selection should depend on how irritable the tendon is and what activity the person is trying to return to.

A runner needs a different end-stage program from someone whose main goal is to walk comfortably and climb stairs.

Still, several types of exercises commonly play a role.

1. Double-Leg Bridge

The bridge strengthens the gluteal muscles and posterior hip while helping build pelvic control.

Lie on your back with your knees bent and feet on the floor. Tighten the abdominal muscles gently and lift the hips without excessively arching the lower back.

Early rehabilitation research has identified double-leg bridging as an exercise capable of strengthening surrounding muscles with relatively limited iliopsoas demand. [4]

If the exercise reproduces deep groin pain, it should be modified or stopped.

2. Side-Lying Hip Abduction

Strength around the outer hip is important because the gluteal muscles help stabilize the pelvis during walking and running.

Lie on your side and raise the upper leg slowly while keeping the pelvis stable.

Exercise selection and positioning matter because different variations produce different levels of iliopsoas activation. Progressive hip rehabilitation therefore often moves from easier exercises toward more demanding versions rather than starting with the hardest variation. [4]

3. Core and Pelvic Stabilization Exercises

The psoas does not function in isolation.

Control of the trunk, pelvis, gluteal muscles and lower extremity influences how forces are distributed around the hip. Rehabilitation of iliopsoas problems therefore commonly includes strengthening beyond the painful tendon itself. [2,6]

Simple exercises may progress toward more demanding anti-rotation, balance and single-leg activities as symptoms improve.

4. Gentle Hip-Flexor Stretching

Stretching may be appropriate when the iliopsoas and surrounding tissues are genuinely restricted.

One common stretch involves placing one knee on the floor and gently shifting the pelvis forward while keeping the trunk upright.

The key word is gently.

A useful stretch should feel like controlled tension through the front of the hip—not sharp groin pain.

Deep lunges that strongly reproduce the person’s familiar symptoms are not a better stretch simply because they feel more intense.

5. Progressive Hip-Flexion Strengthening

Eventually, a tendon that needs to tolerate hip flexion must be trained to tolerate hip flexion.

That does not mean beginning with repeated straight-leg raises on the first painful day.

Controlled hip-flexion loading can be introduced and progressed as symptoms permit. A systematic review examining iliopsoas activation during common rehabilitation exercises supports the concept that hip-flexor exercises can be ranked and progressed according to how much they recruit the iliopsoas. [8]

Progression might eventually move from easier short-lever movements to greater resistance and longer-lever exercises.

For athletes, the final progression must eventually resemble the demands of their sport.

Is Walking Good for Psoas Tendinitis?

For many people, yes.

Walking can provide useful low-level loading and help prevent excessive deconditioning while the tendon recovers.

The important question is not simply, “Does walking hurt?”

A better question is:

“How does the hip respond during the walk and over the next 24 hours?”

A small amount of discomfort that settles promptly may be acceptable in some rehabilitation programs. But walking is probably too demanding at the current stage if it produces:

  • Increasing groin pain with every step
  • Limping
  • Pain that continues to escalate after the walk
  • Significantly worse pain the following morning
  • A progressive reduction in walking tolerance

In one iliopsoas tendinopathy rehabilitation case, walking was reintroduced after symptoms had improved and was progressed as long as it did not worsen pain. [3]

Can You Run With Psoas Tendinitis?

Running through persistent psoas tendinitis is usually not the fastest route back to running.

Running repeatedly flexes the hip, and sprinting, hill running and faster speeds can place particularly high demands on the hip flexors.

That does not mean every runner needs weeks of complete inactivity.

Depending on symptom severity, alternatives such as walking, swimming or other forms of conditioning that do not provoke groin pain may be possible.

When running returns, the progression is usually safer when it begins below the person’s previous training load.

For example, a runner may progress through:

  • Pain-controlled walking
  • Brisk walking
  • Short walk-jog intervals
  • Easy continuous running
  • Increasing distance
  • Increasing speed
  • Hills
  • Intervals and sprinting

Trying to restore distance, speed and hills simultaneously makes it much harder to identify how much load the tendon can tolerate.

What Exercises Should You Avoid With Psoas Tendinitis?

There is no universal blacklist. An exercise that is inappropriate during an irritable phase may become an important strengthening exercise later.

However, during an active flare, be cautious with movements that strongly reproduce anterior hip or groin pain.

Common offenders include:

Repeated Straight-Leg Raises

Keeping the knee straight creates a longer lever and can substantially increase the demand on the hip flexors. These may be useful later in rehabilitation but can be too provocative early on.

Hanging Leg Raises and Hanging Knee Raises

These exercises repeatedly load the hip flexors and may aggravate an irritated iliopsoas.

High-Volume Sit-Ups

Although usually thought of as an abdominal exercise, some sit-up variations recruit the hip flexors substantially.

Deep Lunges

The trailing hip moves into extension, which stretches the iliopsoas. Aggressive stretching into a painful range can irritate the area further.

Sprinting and Hill Running

Both substantially increase the demand placed on hip flexion compared with easy level walking.

High-Knee Drills

Repeated forceful hip flexion is exactly the movement that frequently aggravates the tendon.

The aim is not to fear these exercises permanently. It is to reintroduce them when the tendon has enough capacity to tolerate them.

Should You Foam Roll the Psoas?

Trying to aggressively press directly into the psoas with a hard ball, massage device or foam roller is not necessary for recovery.

The psoas lies deep within the abdomen and pelvis, with important nerves, blood vessels and organs nearby. It is not positioned like a superficial calf or thigh muscle that can easily be rolled directly.

Gentle work around surrounding muscles may feel helpful, but repeatedly digging deeply into the abdomen in an attempt to “release the psoas” is not an essential treatment for psoas tendinitis.

The more important rehabilitation goals are identifying excessive loading, restoring comfortable movement and progressively rebuilding strength.

Is Stretching Good or Bad for Psoas Tendinitis?

It depends.

A person with limited hip extension and true hip-flexor tightness may benefit from carefully prescribed stretching.

But pain does not automatically mean the psoas needs to be stretched.

Tendon pain may actually become worse when the irritated structure is repeatedly stretched into a painful range.

If every hip-flexor stretch creates sharp groin pain that lasts afterward, continuing to stretch harder is unlikely to be productive.

Stretching should therefore be considered one component of rehabilitation, not the entire treatment.

What Should You Avoid While Your Psoas Tendon Is Healing?

Several habits commonly delay recovery.

Avoid Testing the Pain Repeatedly

People often check the tendon every few hours by lifting the leg, performing a lunge or pressing deeply into the groin. Repeatedly provoking the tendon does not provide useful new information and may keep the area irritated.

Avoid the “No Pain, No Gain” Approach

A tendon rehabilitation program should challenge the tissue eventually, but sharp or progressively worsening groin pain is not evidence that an exercise is working.

Avoid Increasing Exercise Too Quickly After a Good Day

Tendons can react with a delay. You may feel good during exercise but be significantly worse the next morning. That delayed response is one reason rehabilitation should be progressed gradually.

Avoid Resting Until You Feel Absolutely Nothing

Waiting for complete symptom disappearance before performing any strengthening can result in weeks of lost conditioning. Activity should usually be adjusted rather than abandoned indefinitely.

Avoid Assuming Every Tight Hip Flexor Is a Tight Psoas

Persistent anterior hip pain can originate from the joint, tendon, bursa or surrounding structures. If treatment is repeatedly unsuccessful, the answer may not be “more stretching.”

How Do You Know When Psoas Tendinitis Is Getting Better?

Pain intensity is only one measure.

Recovery is moving in the right direction when you notice improvements such as:

  • Getting out of a chair with less pain
  • Climbing stairs more comfortably
  • Lifting the knee with less groin discomfort
  • Walking farther without symptoms increasing
  • Less stiffness after sitting
  • Improved hip strength
  • Fewer painful flare-ups
  • Better tolerance of exercises
  • Faster recovery after activity
  • Ability to gradually increase training without next-day worsening

Progress is rarely perfectly linear.

A slightly sore day after introducing a new exercise does not necessarily mean you have reinjured the tendon. What matters more is the overall trend and whether the tendon is tolerating progressively greater loads.

Why Does My Psoas Still Hurt After 6 Weeks?

Six weeks of symptoms does not automatically mean something serious is wrong, particularly if the problem began as an established tendinopathy rather than a mild acute irritation.

However, ongoing symptoms deserve another look when:

  • There has been no meaningful improvement
  • Pain is progressively worsening
  • Walking is becoming more difficult
  • The hip catches or locks
  • There is substantial loss of hip motion
  • Pain occurs at night without an obvious mechanical reason
  • There is numbness or weakness
  • Pain travels far down the leg
  • You cannot bear weight comfortably
  • Rehabilitation consistently makes symptoms worse

At this stage, it may be necessary to reconsider whether the iliopsoas tendon is truly the main pain generator.

When Is Imaging Needed for Persistent Psoas Tendinitis?

Imaging is not automatically required for every new case.

If the history and examination fit iliopsoas tendinopathy and symptoms respond to conservative treatment, rehabilitation may begin without advanced imaging.

Persistent or unusual symptoms may lead to further investigation.

Magnetic resonance imaging can evaluate the tendon and surrounding structures while also looking for other sources of hip or pelvic pain.

Musculoskeletal ultrasound can evaluate the iliopsoas dynamically and may be especially useful when snapping or bursitis is suspected.

Imaging can also help identify conditions that mimic psoas tendinitis. [2]

What If Exercises and Physical Therapy Do Not Help?

Most iliopsoas problems are initially managed without surgery.

Conservative treatment can include:

  • Activity modification
  • Physical therapy
  • Progressive strengthening
  • Stretching when appropriate
  • Modification of training errors
  • Pain management when medically appropriate

If symptoms remain significant despite a properly performed rehabilitation program, an image-guided injection may sometimes be considered.

A 2025 systematic review examining iliopsoas injections found improvement in pain and functional outcomes across studies involving iliopsoas tendinopathy, bursitis and snapping hip. Most patients included in the review did not progress to surgery, although the available studies varied considerably and larger prospective trials are still needed. [9]

Surgery is generally reserved for carefully selected cases that remain symptomatic despite conservative management, particularly when mechanical snapping or iliopsoas impingement is present. [2,10]

How Can You Prevent Psoas Tendinitis From Coming Back?

Getting rid of pain is only part of recovery.

If the tendon became irritated because running mileage doubled, returning directly to the same mileage creates the same loading problem.

Long-term prevention may involve:

  • Increasing training gradually
  • Building hip and gluteal strength
  • Maintaining adequate recovery between demanding workouts
  • Avoiding abrupt increases in sprinting or hill training
  • Improving trunk and pelvic control
  • Addressing obvious movement limitations
  • Varying training rather than repeating the same high-load movement every day
  • Continuing maintenance strengthening after symptoms resolve

For athletes, returning to sport should be seen as a continuum rather than a single day on which the injury is declared “healed.” [7]

Frequently Asked Questions About Psoas Tendinitis Recovery

Can psoas tendinitis heal in two weeks?

A mild, recent flare may improve substantially within two weeks, but established iliopsoas tendinopathy often requires considerably longer. Feeling better is also not the same as having completely restored the tendon’s capacity for demanding activity.

Is 6 weeks enough for psoas tendinitis to heal?

Six weeks may be enough for some mild to moderate cases, but many rehabilitation programs continue for 6 to 12 weeks or longer. Recovery should be judged by symptoms, strength and activity tolerance rather than the calendar alone. [3,4]

Can psoas tendinitis last for months?

Yes. Chronic iliopsoas tendinopathy can persist for several months, particularly if the tendon continues to be overloaded or if another hip condition is contributing to the pain.

Should I walk with psoas tendinitis?

Walking is often acceptable when it does not cause progressively increasing pain, limping or a significant symptom flare afterward. Walking distance and speed may need to be temporarily reduced.

Should I stretch my psoas every day?

Not necessarily. Gentle stretching may help when hip-flexor tightness is present, but repeatedly stretching an irritated tendon into pain can aggravate symptoms. Stretching should be only one part of a broader rehabilitation program.

Can I do squats with psoas tendinitis?

Some people tolerate squats well because the movement primarily strengthens the hips and thighs without demanding repeated open-chain hip flexion. Others may experience anterior hip pain, particularly with deep squats. Depth, load and technique should be adjusted according to symptoms.

Are leg raises bad for psoas tendinitis?

Straight-leg raises require substantial hip-flexor activity and can aggravate an irritable iliopsoas tendon. They may be introduced later as strengthening exercises when the tendon is ready for greater loading.

Can I continue running if the pain is mild?

This depends on how the tendon responds during and after running. In established psoas tendinopathy, temporarily reducing running volume or stopping provocative running may allow rehabilitation to progress more effectively. A gradual return is generally preferable to repeatedly running through increasing groin pain.

When can I return to the gym after psoas tendinitis?

You may not need to stop all gym activity. Upper-body work and lower-body exercises that do not provoke the tendon can often continue. Hip-flexion-heavy exercises and movements that reproduce groin pain may need to be modified temporarily.

Why does my psoas feel better and then hurt again?

Tendon symptoms often respond to changes in load. A person may feel substantially better after several quiet days and then overload the tendon by immediately returning to normal training. A recurrence does not necessarily mean the tendon has been newly injured; it may mean the increase in activity exceeded its current capacity.

The Bottom Line: Recovery Is About Building Capacity, Not Just Waiting

So, how long does psoas tendinitis take to heal?

For some mild cases, noticeable improvement may occur within a few weeks. A more established iliopsoas tendinopathy commonly requires roughly 6 to 12 weeks of progressive rehabilitation, and stubborn or chronic cases may take several months. [3,4]

But the calendar tells only part of the story.

The better question is whether the tendon is gradually becoming capable of doing more.

Can you walk farther? Can you climb stairs without sharp groin pain? Can you lift the leg comfortably? Can you perform strengthening exercises and feel similar or better the following day? Can a runner gradually increase mileage without another flare?

Those improvements matter more than reaching a particular week.

Reducing the movements that repeatedly irritate the iliopsoas, avoiding overly aggressive stretching, strengthening the hip and pelvic muscles, progressively reloading the hip flexors and returning to sport gradually gives the tendon a far better chance of recovering than alternating between complete rest and sudden bursts of full activity.

And if several weeks of well-planned rehabilitation produce little or no improvement, it is worth reconsidering the diagnosis rather than simply assuming that the psoas needs more time.

References:

  1. Anatomy, Bony Pelvis and Lower Limb: Iliopsoas Muscle. Updated 2026. Conservative rehabilitation of iliopsoas disorders and recovery considerations. (NCBI)
  2. Dydyk AM, Hu Y, Stretanski MF. Psoas Syndrome. Updated 2025. Evaluation and conservative management of iliopsoas-related pain. (NCBI)
  3. Rauseo C. The Rehabilitation of a Runner With Iliopsoas Tendinopathy Using an Eccentric-Biased Exercise—A Case Report. International Journal of Sports Physical Therapy. Progressive loading and return-to-running rehabilitation. (PubMed Central (PMC))
  4. Reiman MP, et al. Conservative Management of Tendinopathies Around Hip. Review of exercise progression and rehabilitation strategies for iliopsoas tendinopathy. (PubMed Central (PMC))
  5. Ardern CL, et al. 2016 Consensus Statement on Return to Sport. British Journal of Sports Medicine. Principles of graded loading and return to sport following injury. (British Journal of Sports Medicine)
  6. Rehabilitation of Soft Tissue Injuries of the Hip and Pelvis. Review of iliopsoas syndrome and overlapping causes of hip and groin pain. (PubMed Central (PMC))
  7. Ardern CL, et al. Return to Sport From the First World Congress in Sports Physical Therapy. Graded return from participation to sport and performance. (British Journal of Sports Medicine)
  8. Hip Flexor Muscle Activation During Common Rehabilitation and Strength Exercises. Systematic review of iliopsoas activation during rehabilitation exercises. (PubMed Central (PMC))
  9. Katz L, Feinberg G, Kent V, et al. Iliopsoas Injections: A Systematic Review of Patient Outcomes and Progression to Surgery. Journal of Bone and Joint Surgery Reviews. 2025. (PubMed)
  10. Anderson CN. Iliopsoas: Pathology, Diagnosis, and Treatment. Clinics in Sports Medicine. Review of conservative and surgical management of iliopsoas disorders. (PubMed)

Is Your Hip or Groin Pain Coming From the Psoas? The Clues That Help Tell

Pain at the front of the hip or deep in the groin can be surprisingly difficult to pin down. You may feel it when climbing stairs, lifting your leg into the car, getting up from a chair, running, or simply trying to stand fully upright. Because the hip joint, lower spine, groin muscles and iliopsoas tendon all sit close together, several very different conditions can produce pain in roughly the same area.

One possible cause is psoas tendinitis, more commonly discussed medically as iliopsoas tendinitis or iliopsoas tendinopathy. The iliopsoas is one of the body’s main hip flexors. When its tendon becomes irritated or overloaded, the most characteristic complaint is deep pain in the front of the hip or groin, particularly during activities that require repeated or forceful hip flexion. However, the discomfort can sometimes extend toward the thigh, pelvis, buttock or lower back. [1]

That overlap is exactly why psoas pain is frequently confused with a hip joint problem, groin strain, bursitis or pain coming from the lumbar spine.

The location of the pain provides an important clue, but it is rarely enough by itself. What triggers the pain, what does not trigger it, and whether there are symptoms such as stiffness, clicking, numbness or weakness often tell us much more.

What Is Psoas Tendinitis?

The psoas major is a deep muscle that begins along the lumbar spine. It travels through the pelvis and joins with the iliacus muscle to form the iliopsoas, which attaches to the upper part of the thigh bone at an area called the lesser trochanter.

Together, these muscles form the body’s most important hip-flexing unit. They help bring your thigh toward your trunk when you walk, run, climb stairs, get into a vehicle or lift your knee. The iliopsoas also contributes to hip stability and has an anatomical relationship with the lumbar spine. [2]

Repetitive loading of the iliopsoas can irritate the tendon. This is particularly relevant in runners, dancers and athletes whose activities involve repeated hip flexion, sprinting or kicking, although psoas problems are not limited to athletes. Prolonged sitting, altered movement patterns, abrupt changes in activity and some hip or spinal conditions can also contribute. [1]

You may see several names used for similar problems, including:

  • Psoas tendinitis
  • Iliopsoas tendinitis
  • Iliopsoas tendinopathy
  • Psoas syndrome
  • Iliopsoas syndrome
  • Iliopsoas bursitis
  • Iliopsoas impingement

These terms are not technically identical. For example, tendinitis implies inflammation of the tendon, while tendinopathy is a broader term that can include tendon degeneration and chronic overload. Iliopsoas bursitis involves irritation of the fluid-filled bursa located near the tendon. In everyday clinical practice, however, symptoms can overlap considerably. [1]

Where Does Psoas Tendinitis Hurt?

The classic location of psoas tendinitis pain is the front of the hip and deep groin.

People often have difficulty pointing to one exact spot because the iliopsoas tendon lies deep rather than directly under the skin. Instead of superficial soreness, the pain may feel as though it is coming from somewhere inside the front of the hip.

The pain may be felt in one or more of these areas:

  • Deep in the groin
  • Front of the hip
  • Upper front of the thigh
  • Pelvic region
  • Lower abdomen near the crease of the hip
  • Lower back
  • Buttock or sacral region in some cases

Psoas syndrome is described as typically producing anterior groin pain that may radiate toward the thigh or lumbar region. Altered walking mechanics can also contribute to discomfort around the lower spine. [1]

This means that psoas tendinitis does not always feel like straightforward hip pain.

What Does Psoas Tendinitis Pain Feel Like?

The sensation varies according to how irritated the tendon is and how long the problem has been present.

Some people describe a persistent deep ache in the groin. Others notice a sharper pain only when they lift the leg against resistance.

Common descriptions include:

  • Deep aching pain at the front of the hip
  • Sharp groin pain when lifting the knee
  • Tightness through the front of the hip
  • Pulling discomfort when extending the hip
  • Pain when transitioning from sitting to standing
  • Clicking, snapping or catching at the front of the hip
  • Pain that improves with rest but returns with activity

Psoas pain is often movement-dependent. That is an important distinction.

If you are reasonably comfortable while resting but experience a familiar deep pain every time you lift your thigh, climb stairs or extend the hip behind you, the iliopsoas becomes more suspicious as a source.

Which Movements Usually Make Psoas Tendinitis Hurt?

Because the iliopsoas is heavily involved in hip flexion, symptoms commonly appear during activities that repeatedly bring the thigh toward the body.

Pain may increase while:

Climbing stairs

Every step requires the hip flexors to lift the leg onto the next stair. Repeated stair climbing can therefore reproduce iliopsoas pain.

Getting into or out of a car

This is a particularly useful clue. Getting into a vehicle often involves lifting the thigh while rotating the hip. Someone with an irritated iliopsoas may notice a sharp or deep groin pain during this movement.

Getting up from a chair

Moving from prolonged hip flexion in sitting to standing can stretch and load the iliopsoas. Some people feel pain or stiffness during the first few steps after sitting.

Running or sprinting

Running repeatedly loads the hip flexors, particularly when accelerating, running uphill or increasing training volume suddenly.

Kicking

Soccer, martial arts and other kicking activities combine rapid hip flexion with substantial force and can aggravate the iliopsoas.

Doing sit-ups or leg raises

Exercises that repeatedly lift the legs or trunk can heavily recruit the hip flexors.

Walking with a long stride

A long stride places the hip farther into extension behind the body. Stretching an irritated iliopsoas tendon in this position may provoke symptoms.

Clinical descriptions of iliopsoas-related groin pain emphasize pain with resisted hip flexion and pain when the hip flexors are stretched into extension. [3]

Can Psoas Tendinitis Cause Lower Back Pain?

Yes, it can—but lower back pain by itself does not establish that the psoas is the problem.

The psoas major originates along the lumbar vertebrae before passing through the pelvis. This anatomical connection helps explain why irritation, tightness or altered function of the iliopsoas can be associated with discomfort around the lower back.

People with psoas syndrome may notice lower back pain during walking, difficulty standing fully upright or discomfort when moving from sitting to standing. Pain may also be felt near the sacrum, pelvis or buttock. [1]

However, lower back pain is extraordinarily common and can arise from muscles, joints, discs, nerves and many other structures. For that reason, assuming that a “tight psoas” explains chronic back pain without a proper examination can easily lead someone in the wrong direction.

The more convincing pattern is lower back or pelvic discomfort occurring together with anterior hip or groin pain that is reproducible when the hip flexors are loaded or stretched.

Psoas Tendinitis vs Hip Joint Pain: How Can You Tell the Difference?

This is one of the hardest distinctions because both problems can produce deep groin pain.

A useful starting point is this:

Psoas tendinitis tends to hurt when the hip flexor tendon itself is loaded. Hip joint disorders are more likely to hurt when the joint is compressed, rotated or moved through certain ranges.

This is not an absolute rule, but it helps clinicians decide where to look next.

Anterior hip pain can arise from several sources, while intra-articular hip pain in younger adults commonly involves femoroacetabular impingement or a labral tear and in older adults commonly involves osteoarthritis. [4]

Psoas Tendinitis vs Hip Labral Tear

A hip labral tear is particularly easy to confuse with iliopsoas problems.

Both may cause:

  • Deep groin pain
  • Clicking or catching
  • Pain with physical activity
  • Pain during hip movement
  • A sensation that something is moving inside the joint

There are, however, some differences.

A labral tear is more likely to produce deep joint pain associated with hip rotation, pivoting or twisting. Some people experience locking, instability or a persistent clicking sensation. Labral tears can also cause stiffness. [9]

With psoas tendinitis, symptoms are often particularly reproducible when you actively lift the thigh or when someone applies resistance while you try to flex the hip.

Internal snapping of the iliopsoas tendon can further confuse the picture. The American Academy of Orthopaedic Surgeons notes that the iliopsoas tendon can catch over structures at the front of the pelvis, producing a snapping sensation. Labral and cartilage problems can also cause catching or locking, which is why clicking alone cannot identify the source. [5]

In fact, iliopsoas tendinopathy itself may produce a catching or slipping sensation in the groin, so a physical examination and sometimes imaging are required to tell these conditions apart. [1]

Psoas Tendinitis vs Hip Osteoarthritis

Hip osteoarthritis can also cause groin pain, particularly in middle-aged and older adults.

The biggest clue is often stiffness and loss of hip motion.

Hip arthritis commonly causes:

  • Groin pain
  • Hip stiffness
  • Reduced range of motion
  • Difficulty bending at the waist
  • Limping
  • Pain that may spread into the thigh, buttock or knee
  • Grinding, catching or clicking. [10]

Psoas tendinitis usually does not cause the same generalized loss of hip joint movement. Instead, particular movements that load or stretch the hip flexor tend to be disproportionately painful.

If putting on socks, tying shoes and rotating the hip in several directions are becoming increasingly difficult because the entire joint feels stiff, osteoarthritis becomes more likely than isolated psoas tendinitis.

The two conditions can also coexist.

Psoas Tendinitis vs Hip Bursitis

“Hip bursitis” usually refers to greater trochanteric pain syndrome, which produces pain over the outer side of the hip rather than deep in the groin.

This distinction can sometimes be quite helpful.

Greater trochanteric pain syndrome typically produces:

  • Pain directly over the outside of the hip
  • Tenderness when pressing over the bony prominence at the side of the hip
  • Pain while lying on the affected side
  • Pain during walking or stair climbing
  • Pain that may spread down the outside of the thigh

Psoas tendinitis generally causes anterior hip or groin pain, not isolated tenderness over the outer hip.

There is another condition called iliopsoas bursitis, however, and this can produce symptoms extremely similar to psoas tendinitis because the bursa and tendon are located close together. Iliopsoas bursitis may cause groin, hip or anterior thigh discomfort. [6]

Psoas Tendinitis vs Hip Flexor Strain

A hip flexor strain usually follows a more obvious episode of muscle overload or injury.

For example, pain may begin suddenly while:

  • Sprinting
  • Kicking a ball
  • Changing direction rapidly
  • Jumping
  • Performing an explosive exercise

A more chronic iliopsoas tendinopathy often develops gradually as repeated loading exceeds the tendon’s ability to recover.

That distinction is not perfect. The iliopsoas is itself part of the hip flexor group, and both muscle and tendon injuries can occur together. But sudden pain after an explosive movement is more suggestive of an acute strain, whereas gradually worsening pain during repeated hip flexion is more typical of tendinopathy.

Psoas Tendinitis vs Adductor or Groin Strain

Not all groin pain comes from the hip flexors.

The adductor muscles run along the inner thigh and are commonly injured in sports involving kicking, cutting and twisting.

Adductor-related groin pain is typically associated with:

  • Tenderness near the adductor attachment in the groin
  • Pain when squeezing the legs together
  • Pain with resisted hip adduction
  • Inner-thigh discomfort

By comparison, iliopsoas-related pain is more likely to occur with resisted hip flexion and stretching of the hip flexors. Sports medicine literature specifically uses these movement patterns to help distinguish adductor-related from iliopsoas-related groin pain. [3]

Importantly, more than one source of groin pain can exist at the same time, particularly in athletes.

Psoas Tendinitis vs Lower Back Pain or Lumbar Radiculopathy

Pain originating in the lumbar spine may be mistaken for hip pain, while true hip and iliopsoas problems may occasionally be mistaken for spinal pain.

There are several clues that make a nerve problem more likely.

Lumbar radiculopathy can cause:

  • Lower back pain
  • Burning or shooting pain into the leg
  • Numbness
  • Tingling
  • Pins-and-needles sensations
  • Muscle weakness [8]

These neurological symptoms are not typical features of isolated psoas tendinitis.

Psoas syndrome can sometimes produce pain that radiates toward the thigh or lower back, but pain from iliopsoas irritation generally does not follow the classic nerve-root pattern of numbness, tingling and weakness extending down the leg. A recent review specifically lists iliopsoas tendinopathy and bursitis among musculoskeletal conditions that can mimic lumbar radiculopathy. [7]

If symptoms extend well below the knee or include obvious sensory changes or weakness, a spinal or neurological cause deserves particular attention.

Is Pain When Lifting the Leg a Sign of Psoas Tendinitis?

It can be one of the stronger clues.

Imagine sitting in a chair and lifting your knee toward your chest. The iliopsoas contracts strongly to perform that movement.

If this reliably reproduces deep anterior hip or groin pain—particularly when the movement is resisted—it raises suspicion that the iliopsoas is involved.

Clinicians may therefore assess pain during resisted hip flexion in several positions. Current clinical approaches to iliopsoas-related groin pain also consider tenderness over the hip flexor complex and pain when the iliopsoas is stretched. [3]

That does not mean you should use a painful leg-lifting exercise to diagnose yourself. Several hip conditions can hurt during the same movement.

What About Psoas Pain When Standing Up Straight?

This is another potentially useful clue.

When you stand upright after sitting, your hip moves from flexion toward extension. An irritated or shortened iliopsoas is stretched during that transition.

Some people with psoas syndrome therefore feel as though they cannot immediately straighten fully after getting out of a chair. They may take a few shortened steps before standing more comfortably upright. [1]

A similar pattern can appear after prolonged sitting at a desk or during a long car journey.

Again, this is suggestive rather than diagnostic.

Can Psoas Tendinitis Cause Clicking or Snapping in the Hip?

Yes.

The iliopsoas tendon can move over bony structures at the front of the hip and produce an audible or palpable snap. This is sometimes called internal snapping hip syndrome.

Snapping itself is not always painful and can occur without a significant injury. When the snapping becomes painful, however, irritation of the tendon or nearby bursa may be involved.

A painful snap in the front of the hip is more suggestive of the iliopsoas than a snap over the outside of the hip.

However, deep catching, locking or clicking may also come from cartilage or a labral tear inside the joint. Symptoms alone cannot always separate them.

How Do Doctors Diagnose Psoas Tendinitis?

There is no single home test that can prove that hip or groin pain comes from the psoas.

Diagnosis usually begins with a careful history.

A clinician may ask:

  • Where exactly is the pain?
  • Did it develop suddenly or gradually?
  • Does lifting the knee reproduce it?
  • Does stretching the hip backward reproduce it?
  • Is there clicking or snapping?
  • Does the pain travel below the knee?
  • Is there numbness or tingling?
  • Has your running or exercise volume recently changed?
  • Have you had previous hip surgery?
  • Do you have back pain as well?

The physical examination may include palpating the iliopsoas area and testing hip flexion against resistance. The Thomas or modified Thomas test may also be used to assess hip flexor tightness or reproduce symptoms. [3,7]

However, no isolated examination maneuver should be considered definitive. The clinician also needs to assess the hip joint, lumbar spine and surrounding groin structures.

Do You Need Magnetic Resonance Imaging for Psoas Tendinitis?

Not always.

Many cases can initially be evaluated clinically. Imaging becomes more useful when the diagnosis is uncertain, symptoms persist despite appropriate treatment, or another condition needs to be excluded.

Magnetic resonance imaging can show abnormalities involving the iliopsoas tendon, bursa and surrounding structures. Musculoskeletal ultrasound can also evaluate the tendon and bursa and has the advantage of showing the iliopsoas dynamically while the hip moves. [1,7]

In selected cases, an image-guided injection of local anesthetic around the iliopsoas may also help determine whether it is actually the source of the pain.

X-rays do not show the iliopsoas tendon well but may be useful for identifying or excluding problems involving the bones and hip joint.

When Groin or Psoas-Like Pain Needs More Urgent Evaluation

Most activity-related iliopsoas problems are not emergencies. But not every deep groin or psoas-region pain is a tendon problem.

Seek prompt medical assessment if hip, groin or lower abdominal pain is accompanied by:

  • Fever or chills
  • Unexplained weight loss
  • Severe or rapidly worsening pain
  • Significant night pain without an obvious mechanical trigger
  • Inability to bear weight
  • Major trauma
  • New leg weakness
  • Significant numbness
  • Loss of bladder or bowel control
  • Severe abdominal symptoms
  • A new groin lump or swelling

The psoas lies deep within the abdomen and pelvis, close to several organs and important structures. Less common conditions such as infection, a psoas abscess, malignancy, kidney stones and abdominal or pelvic disorders can occasionally produce pain that resembles a musculoskeletal psoas problem. [1,2]

The Location of Psoas Pain Is a Clue—But the Movement Pattern Matters More

If there is one useful way to think about psoas tendinitis, it is this:

Do not focus only on where the pain is. Pay attention to what makes it appear.

Deep pain at the front of the hip or groin that repeatedly worsens when you lift your knee, climb stairs, run, get out of a car or stretch the hip backward fits the iliopsoas pattern better than pain based on location alone.

Outer hip tenderness—especially pain when sleeping on that side—points more toward greater trochanteric pain syndrome.

Deep groin pain with stiffness, loss of hip rotation or progressive limitation may suggest a problem within the hip joint.

Catching or locking during rotation may raise concern for labral or cartilage pathology.

Back pain accompanied by numbness, tingling, weakness or pain extending farther down the leg makes a spinal nerve problem more likely.

And none of these patterns are absolute. Hip, groin and spinal disorders frequently overlap.

That is why persistent “psoas pain” should not automatically be treated as a tight muscle that simply needs more stretching. Correctly identifying whether the pain is coming from the iliopsoas tendon, hip joint, outer hip, groin muscles or lumbar spine is usually the most important first step toward choosing the right treatment.

Frequently Asked Questions About Psoas Tendinitis Pain

Where is psoas tendinitis pain usually located?

Psoas tendinitis most often causes a deep ache or sharp pain in the front of the hip or groin. Pain may sometimes extend into the upper thigh, pelvis, buttock or lower back.

Can psoas tendinitis cause groin pain?

Yes. Groin pain is one of the most characteristic symptoms of iliopsoas tendinitis or iliopsoas tendinopathy. It often worsens during movements involving hip flexion.

Can psoas tendinitis cause lower back pain?

It can. The psoas attaches to the lumbar spine, and psoas syndrome can be associated with lower back or lumbosacral discomfort. However, many other conditions cause back pain, so back pain alone is not enough to diagnose a psoas problem.

Why does my psoas hurt when I lift my leg?

The iliopsoas is a primary hip flexor. Lifting the thigh requires it to contract. If its tendon is irritated, active or resisted hip flexion may reproduce pain.

Does psoas tendinitis hurt when walking?

It can, particularly with longer strides, fast walking, hills or prolonged activity. Some people develop a subtle limp or shorten their stride because hip extension is uncomfortable.

Does psoas tendinitis hurt when sitting?

Prolonged sitting can aggravate symptoms in some people because the hip remains flexed for an extended period. Pain may be most noticeable when first standing after sitting.

Can psoas pain travel down the leg?

Psoas-related pain can extend toward the upper thigh, but pronounced numbness, tingling, burning, weakness or pain traveling well below the knee should raise greater suspicion for a neurological or spinal problem.

How can you tell psoas tendinitis from hip bursitis?

Typical greater trochanteric pain syndrome causes pain and tenderness over the outside of the hip, often worsening when lying on that side. Psoas tendinitis more commonly causes deep anterior hip or groin pain, especially during resisted hip flexion.

How can you tell psoas tendinitis from a labral tear?

Both can cause groin pain and clicking. Psoas pain tends to be reproduced by loading the hip flexor, while labral problems may produce deeper joint pain, catching, locking or pain during twisting and hip rotation. Clinical examination and sometimes imaging may be needed to distinguish them.

Should you stretch a painful psoas?

Stretching is sometimes included in rehabilitation, but aggressively stretching an already irritated tendon is not automatically helpful. Treatment should be based on whether the problem is primarily tendon overload, muscle tightness, hip joint disease or another cause. Persistent symptoms are better evaluated before repeatedly stretching through pain.

References:

  1. Dydyk AM, Hu Y, Stretanski MF. Psoas Syndrome. StatPearls. Updated May 4, 2025. National Center for Biotechnology Information. (NCBI)
  2. Bordoni B, Varacallo MA. Anatomy, Bony Pelvis and Lower Limb: Iliopsoas Muscle. StatPearls. Updated June 8, 2026. National Center for Biotechnology Information. (NCBI)
  3. A New Clinical Examination Algorithm to Prescribe Conservative Treatment in People with Hip-Related Pain. Pain and Therapy. Discussion of iliopsoas-related groin pain assessment, resisted hip flexion and hip flexor stretch testing. (Springer Link)
  4. Chamberlain R. Hip Pain in Adults: Evaluation and Differential Diagnosis. American Family Physician. 2021;103(2):81-89. (AAFP)
  5. American Academy of Orthopaedic Surgeons. Snapping Hip. OrthoInfo. (OrthoInfo)
  6. Teh J. Imaging the Hip. Imaging. Discussion of iliopsoas bursitis and other causes of hip pain. (OUP Academic)
  7. Bateman EA, et al. Musculoskeletal Mimics of Lumbosacral Radiculopathy. Muscle & Nerve. Discussion of iliopsoas tendinopathy and bursitis as mimics of lumbar radiculopathy. (Wiley Online Library)
  8. Cleveland Clinic. Psoas Syndrome: Symptoms, Causes & Treatment. (Cleveland Clinic)
  9. Cleveland Clinic. Hip Labral Tear: Symptoms & Treatment. (Cleveland Clinic)
  10. Cleveland Clinic. Hip Arthritis: Causes, Symptoms & Treatment Options. (Cleveland Clinic)

Lactic Acid Buildup and the Workout Burn: What Your Muscles Are Actually Doing

Anyone who has pushed through the last few repetitions of a difficult squat, sprinted up a hill, or cycled hard against resistance knows the feeling: the muscles begin to burn, power starts dropping, and eventually the body seems to demand that you slow down.

For decades, that uncomfortable sensation was commonly blamed on lactic acid buildup in the muscles. The explanation sounded simple enough—exercise produces lactic acid, lactic acid makes the muscles acidic, and the acid causes burning, fatigue, and eventually soreness.

Exercise physiology has moved well beyond that explanation.

The substance accumulating during intense exercise is primarily lactate, not pools of lactic acid sitting inside your muscles. Lactate is not merely an unwanted waste product. It is continuously produced and used by the body, and it can serve as an important fuel and metabolic intermediate. Researchers now recognize lactate as part of a sophisticated system that moves energy between muscles and other tissues. [1,2]

The burning sensation during intense exercise is real, but lactate alone is not responsible for it. And the sore legs you feel one or two days after a workout are caused by an entirely different process.

So what is actually happening when your muscles burn? How long does exercise-related lactate remain elevated? And is there really anything you can do to “flush lactic acid” from your muscles?

Here is what the science shows.

What Is Lactic Acid Buildup During Exercise?

When you exercise, your muscles need energy to continue contracting. That energy ultimately comes from adenosine triphosphate, the molecule muscle fibers use to power contraction.

Because muscles store only a limited amount of immediately available adenosine triphosphate, the body must continually regenerate it while you exercise.

During lower-intensity activity, much of the energy requirement can be met through aerobic metabolism. As exercise becomes harder, however, the rate at which the muscles need energy rises sharply.

Carbohydrate breakdown through glycolysis becomes increasingly important. Glycolysis converts glucose into pyruvate while rapidly helping regenerate the energy required for muscle contraction. When the rate of glycolysis is high, much of that pyruvate is converted into lactate. [1]

Blood lactate concentration can therefore increase dramatically during very intense exercise. Measurements after maximal exercise have recorded blood lactate concentrations many times higher than resting concentrations, with peak values sometimes occurring several minutes after the exercise has stopped. [3]

This rise is what people usually mean when they refer to “lactic acid buildup.”

But there is an important scientific distinction.

Lactic Acid vs Lactate: Are They the Same Thing?

The phrases lactic acid and lactate are frequently used interchangeably, including in gyms, sports commentary and even some older medical literature.

Inside the human body, however, the distinction matters.

At physiological conditions, the compound commonly referred to as lactic acid exists overwhelmingly in its dissociated form: lactate and a hydrogen ion. For this reason, exercise physiologists generally refer to lactate when discussing what is measured in blood and produced during exercise.

This may sound like a minor chemistry lesson, but it changed how researchers understood muscle fatigue.

Older theories suggested that muscles produced lactic acid, which released hydrogen ions, lowered acidity levels within muscle cells and caused fatigue.

Modern biochemical evidence indicates that lactate production itself is not the cause of exercise-induced metabolic acidosis. In fact, the chemical reactions involved in forming lactate can consume hydrogen ions rather than generating the acidosis once attributed to lactate. [4]

In other words, lactate rises during intense exercise at approximately the same time that other fatigue-related metabolic changes occur. That does not mean lactate is responsible for all of them.

Correlation created a reputation lactate did not entirely deserve.

Why Do Muscles Burn During Exercise?

If lactic acid is not simply burning your muscles, what causes that familiar sensation?

During intense muscle contraction, several things happen simultaneously.

Muscle cells are breaking down adenosine triphosphate extremely rapidly to produce force. Metabolic substances including hydrogen ions, inorganic phosphate and other compounds change in concentration. Potassium movement across muscle-cell membranes changes, calcium handling becomes altered, and the machinery responsible for muscle contraction gradually becomes less efficient.

These changes collectively contribute to muscle fatigue and the uncomfortable sensations associated with very intense exercise. [5,6]

Acidity can play a role, particularly during intense exercise, but even that relationship is more complicated than the traditional “acid equals fatigue” explanation. Research suggests that high concentrations of hydrogen ions and inorganic phosphate can affect muscle-force production under some conditions, while other cellular mechanisms also contribute substantially to fatigue. [6,7]

The important point is this:

Your muscles are not burning because lactate is physically accumulating like acid being poured onto the tissue.

The burning sensation reflects the combined metabolic and sensory consequences of forcing muscle fibers to produce energy and contract at a very high rate.

Why Does the Burning Get Worse During High-Intensity Exercise?

Imagine walking comfortably on a treadmill.

Your muscles need energy, but the demand is manageable. Production and utilization of lactate remain relatively balanced, so blood lactate concentration stays fairly low.

Now increase the speed until you are running hard.

Glycolysis accelerates. Muscle fibers generate lactate more rapidly, but lactate is simultaneously transported out of cells and used by other tissues.

Increase the intensity again into a near-maximal sprint and the rate of lactate appearance can exceed the rate at which it is being utilized or redistributed. Blood lactate rises quickly.

The same general phenomenon occurs during:

  • Sprinting
  • High-intensity cycling
  • Heavy squats
  • Repeated leg presses
  • High-repetition resistance exercises
  • Hill running
  • Rowing
  • Swimming sprints
  • Circuit training
  • Repeated athletic bursts

The harder the muscles work, the faster energy must be supplied.

That is why a leisurely walk rarely produces intense muscle burning, while 30 seconds of hard sprinting can make the legs feel as though they are on fire.

Is Lactate a Waste Product?

No. This is another major misconception.

Lactate was once widely regarded as a metabolic dead end—a waste product that had to be removed before muscles could function normally again.

Research now shows that lactate is an important energy substrate and metabolic intermediary.

Lactate produced by one muscle fiber can be transported and used by other muscle fibers. It can also circulate to organs such as the heart, where it can be oxidized for energy. Lactate reaching the liver can contribute to the production of glucose, which may subsequently be returned to the circulation or stored. [1,2]

This movement and reuse of lactate is often described through the lactate shuttle concept.

Rather than thinking of lactate as metabolic garbage, it is more accurate to picture it as recyclable fuel moving through the body.

The body produces lactate even under aerobic conditions. Its production is not proof that the muscle has suddenly “run out of oxygen.” Lactate production increases substantially when carbohydrate metabolism accelerates, particularly as exercise intensity rises. [1]

Does Lactic Acid Cause Muscle Fatigue?

Lactate concentration and muscle fatigue often rise together during intense exercise, which is one reason lactate was blamed for fatigue for so long.

But lactate itself is not considered the sole—or even necessarily the primary—cause of muscle fatigue.

Muscle fatigue involves several interacting mechanisms, including:

  • Accumulation of inorganic phosphate
  • Changes in hydrogen-ion concentration
  • Altered potassium distribution
  • Changes in calcium release and reuptake
  • Reduced sensitivity of the contractile machinery to calcium
  • Changes in energy availability
  • Alterations in nerve and muscle-cell excitability
  • Central nervous system regulation of effort

The relative importance of each mechanism depends on the intensity, duration and type of exercise being performed. [5,6]

Lactate therefore functions more like a marker of intense glycolytic activity than a simple poison forcing your muscles to stop working.

How Long Does Lactic Acid Buildup Last After Exercise?

This is where one of the biggest myths about exercise soreness falls apart.

Exercise-induced elevations in blood lactate are temporary.

After an intense workout ends, lactate is rapidly transported, metabolized and reused by the body. Lactate levels may actually continue rising briefly after an all-out effort because lactate produced within the muscle takes time to appear in the blood. In maximal exercise studies, peak blood lactate measurements are commonly observed approximately three to eight minutes after exercise. [3]

Afterward, levels progressively decline.

The exact speed of lactate clearance varies according to factors such as:

  • How intense the exercise was
  • How long the activity lasted
  • Training status
  • Recovery activity
  • Blood flow
  • Individual metabolic characteristics

Healthy individuals clear lactate relatively quickly, with reported lactate half-life estimates commonly in the range of roughly 15 to 30 minutes, although recovery kinetics vary considerably according to exercise and recovery conditions. [8]

This means lactate does not remain trapped in your muscles overnight or for several days.

Within the normal recovery period following exercise, the elevated lactate associated with the workout is being rapidly processed.

That leads to an important practical point:

If your legs are sore 24 or 48 hours after a workout, leftover lactic acid is not causing that pain.

Why Are My Muscles Sore the Next Day If the Lactate Is Already Gone?

The discomfort that develops hours after exercise is called delayed onset muscle soreness.

It is particularly common after unfamiliar exercise and activities involving substantial eccentric muscle contractions, where a muscle produces force while lengthening. Examples include lowering a dumbbell, descending stairs, running downhill or lowering yourself into a squat.

These contractions can produce microscopic structural disruption within muscle fibers and supporting structures. This is followed by inflammatory and sensory responses that make the muscle tender and stiff.

This process develops gradually, which is why soreness often becomes more noticeable the day after exercise rather than during the workout itself.

A classic study demonstrated the difference particularly well. People performing level running developed substantial blood lactate elevations but little delayed soreness. Those performing downhill running developed significant delayed muscle soreness even though lactate did not show the same rise. The researchers concluded that lactate was not responsible for delayed onset muscle soreness. [9]

So remember the distinction:

Burning during hard exercise is associated with acute metabolic changes occurring while muscles are working intensely.

Soreness one or two days later is primarily associated with exercise-induced muscle stress, microscopic damage and the subsequent recovery response.

They are not the same phenomenon.

What Is the Lactate Threshold?

As exercise intensity increases, there comes a point at which blood lactate begins rising more rapidly.

This transition is commonly discussed in exercise science using terms such as lactate threshold.

For endurance athletes, the ability to exercise at a higher workload before lactate begins accumulating rapidly is an important part of performance.

A well-trained runner, cyclist or swimmer can often sustain a greater absolute workload before reaching this metabolic transition than an untrained person.

Training does not simply teach the body to “tolerate more lactic acid.” Adaptations can improve mitochondrial function, lactate transport and the ability of tissues to use lactate as fuel.

This is one reason the same running pace that once left a beginner breathless and burning may feel relatively comfortable after months of consistent training.

Can You Flush Lactic Acid Out of Your Muscles?

The phrase “flush out lactic acid” is catchy, but physiologically it is misleading.

Your body does not require a detox drink, supplement, massage gun or special stretch to remove lactate.

It already has an efficient system for transporting and metabolizing lactate.

However, certain recovery strategies can influence how quickly blood lactate concentration falls immediately after intense exercise.

Active Recovery Can Speed Lactate Clearance

Light activity after intense exercise can increase blood flow and allow working and nonworking tissues to continue using lactate for energy.

Research comparing active and passive recovery has repeatedly found that appropriately performed active recovery can reduce blood lactate concentration more quickly than sitting completely still. [10,11]

Examples may include:

  • Easy walking
  • Slow cycling
  • Gentle jogging
  • Very light swimming
  • Low-resistance movement

The key word is light.

Turning a recovery period into another hard workout may continue producing lactate rather than promoting net clearance.

Importantly, faster lactate clearance does not automatically mean faster recovery from every aspect of exercise. Muscle glycogen restoration, nervous-system recovery, repair of exercise-induced muscle damage and recovery of performance occur on different timelines.

Is a Cool-Down Necessary?

A light cool-down may accelerate the decline in blood lactate following high-intensity exercise compared with complete rest.

That can matter particularly for athletes who need to perform another intense effort relatively soon—for example, between heats, intervals or repeated competitive events.

For the average person finishing a gym workout, however, the body will clear exercise-related lactate even without a formal cool-down.

You do not need to keep walking because you are afraid lactate will otherwise remain trapped in your legs.

Does Drinking Water Flush Out Lactic Acid?

Hydration is important, especially after sweating heavily, exercising for a prolonged period or training in hot conditions.

But water does not literally wash lactic acid out of muscle tissue.

Lactate is cleared predominantly through metabolic processes: it is transported and oxidized as fuel or used as a substrate in other metabolic pathways. [1,2]

Drinking adequate fluids supports normal circulation, temperature regulation and overall recovery, but drinking several litres of water simply to “flush lactate” is unnecessary and can be unsafe if taken to excess.

Replace fluid according to your exercise conditions and thirst rather than treating water as an antidote to lactate.

Does Massage Remove Lactic Acid?

Massage can feel good after exercise, and some people find that it reduces sensations of muscle stiffness.

But massage should not be described as physically squeezing lactic acid out of muscle.

In one study examining post-exercise recovery, massage did not enhance lactate clearance in the way traditionally claimed. Active recovery was more effective at reducing blood lactate following intense leg exercise. [12]

Another study specifically investigating the idea that massage enhances blood flow to improve lactate clearance found evidence inconsistent with that explanation. [13]

Massage may have other recovery effects, but “removing lactic acid” is not a good explanation for them.

Does Stretching Get Rid of Lactic Acid?

Stretching also does not pull lactate out of muscle fibers.

Gentle stretching may help some people feel less tight after exercise and can be useful for maintaining or improving flexibility when incorporated appropriately into a training program.

But lactate is already being metabolized by the body.

If you enjoy stretching after a workout, there is no need to stop. Just do it for mobility, relaxation or flexibility—not because lactate has become stuck inside your muscles.

What Should You Eat After Exercise?

Food does not need to “neutralize lactic acid.”

Post-exercise nutrition should instead focus on the actual demands created by training.

After prolonged or demanding exercise, carbohydrate helps replenish muscle glycogen. Protein supplies amino acids that support muscle protein repair and remodeling.

The appropriate amount depends on the duration and intensity of the exercise, body size, training goals and how soon the next exercise session will occur.

Interestingly, lactate itself participates in the movement of carbohydrate-derived energy throughout the body and may eventually contribute to glucose and glycogen production. [2]

So rather than treating lactate as something that must urgently be eliminated, it makes more sense to view it as part of the body’s normal recovery metabolism.

How to Recover After a Workout That Causes Intense Muscle Burning

If you have just completed a strenuous workout and your muscles feel exhausted or heavy, recovery does not need to be complicated.

Slow Down Gradually

After intense cardiovascular exercise or repeated sprints, several minutes of easy movement may help blood lactate fall more rapidly than immediately sitting down.

Rehydrate

Replace fluid lost through sweating. After prolonged exercise or heavy sweating, electrolytes may also need to be replaced depending on the circumstances.

Eat Appropriately

A meal containing carbohydrate, protein and normal nutrient-rich foods can support restoration of energy stores and muscle recovery.

Allow Adequate Recovery Time

The fact that lactate has cleared does not necessarily mean the muscle has completely recovered.

Fatigue can involve muscle-cell processes, nervous-system factors and depleted energy stores that recover at different rates.

Sleep

Adequate sleep supports numerous processes involved in physical recovery and adaptation. It is considerably more important to long-term training recovery than trying to find a product that claims to “detox” lactic acid.

Resume Exercise Gradually

If the muscles are simply fatigued but not injured, normal training can resume according to your recovery and training program.

If significant delayed muscle soreness appears over the next day or two, temporarily reducing the intensity of exercise involving those muscles may be more comfortable.

Can Training Reduce Lactic Acid Buildup?

Training changes how the body handles lactate.

Endurance training can improve the ability of skeletal muscle to oxidize fuels, transport lactate and maintain exercise at greater workloads before blood lactate rises dramatically.

This does not mean trained athletes stop producing lactate. Quite the opposite—they may produce and use large quantities of lactate during intense exercise.

What improves is the body’s ability to transport, recycle and utilize it while sustaining a higher level of performance. The lactate shuttle concept demonstrates that lactate movement between tissues is an integral component of exercise metabolism rather than simply a disposal process. [1,2]

Consistent training therefore changes both how much exercise you can perform before experiencing intense burning and how efficiently your body manages the metabolic demands of that exercise.

Is Lactic Acid Buildup Dangerous?

The temporary increase in lactate caused by vigorous exercise in a healthy person is usually part of normal physiology.

This should not be confused with lactic acidosis associated with serious medical conditions.

Persistently elevated blood lactate can occur with severe illnesses involving inadequate tissue perfusion, certain metabolic disorders, medications or other medical problems. That situation is fundamentally different from the temporary lactate rise following a hard gym session.

If someone develops unexplained rapid breathing, profound weakness, confusion or serious illness, the symptoms should not be attributed casually to “lactic acid from exercise.”

When Muscle Pain After Exercise Is More Than Normal Fatigue

Muscle burning that occurs during strenuous exercise and resolves when the intensity is reduced is generally different from an acute muscle injury.

Stop exercising and seek appropriate evaluation if pain is sudden, sharp or associated with:

  • A popping or tearing sensation
  • Immediate loss of strength
  • Significant swelling
  • Bruising
  • Inability to use the limb normally
  • Severe localized pain
  • Symptoms that progressively worsen rather than improve

Extremely severe muscle pain after unusually strenuous exercise also deserves attention, particularly when accompanied by pronounced weakness, swelling or dark, tea- or cola-colored urine. These can occur with exertional rhabdomyolysis, a potentially serious breakdown of muscle tissue that requires prompt medical assessment.

Do not assume that unusually severe symptoms are simply “too much lactic acid.”

Frequently Asked Questions About Lactic Acid Buildup During Exercise

How long does lactic acid stay in muscles after exercise?

Exercise-related lactate does not remain trapped in muscle for days. Blood lactate may peak several minutes after a maximal effort and then progressively decline as it is transported and metabolized. In healthy people, lactate clearance occurs over a relatively short recovery period rather than over the 24 to 72 hours associated with delayed muscle soreness. [3,8]

Why do my legs burn when doing squats?

High-repetition or intense squats require rapid energy production and cause substantial metabolic changes within the working muscles. Lactate rises, but changes involving hydrogen ions, inorganic phosphate, ions and muscle contraction processes collectively contribute to fatigue and burning. [5,6]

Is muscle burning a sign of a good workout?

Not necessarily. Muscle burning indicates that a muscle is working under substantial metabolic stress, but it is not a universal measure of workout quality. Strength, endurance, mobility and muscle growth can improve without producing extreme burning during every session.

Does lactic acid cause cramps?

Muscle cramps are complex and should not automatically be blamed on lactate. Exercise-associated cramping can involve neuromuscular fatigue and other factors, and simply “removing lactic acid” is not a proven solution.

Does lactic acid cause soreness the next day?

No. Studies comparing different forms of exercise have demonstrated that delayed muscle soreness can develop without corresponding lactate accumulation. Delayed onset muscle soreness is linked much more closely with unfamiliar exercise and exercise-induced muscle stress, particularly eccentric loading. [9]

What is the fastest way to get rid of lactic acid after exercise?

The body clears lactate naturally. Light active recovery can accelerate the reduction in blood lactate compared with complete rest after high-intensity exercise, but special supplements, detox drinks or aggressive massage are not required. [10,11]

Should I stop exercising when my muscles start burning?

A mild to moderate burning sensation is common during strenuous exercise. However, technique should not be sacrificed simply to continue through discomfort. Sharp pain, sudden pain, joint pain, dizziness, chest discomfort or unusual weakness should not be treated as normal exercise burn.

The Bottom Line

“Lactic acid buildup” remains one of the most widely used phrases in exercise, but it gives lactate a role it does not deserve.

During hard exercise, carbohydrate metabolism accelerates and lactate production rises. Lactate may accumulate temporarily in the blood when its rate of production exceeds its rate of utilization and clearance, but lactate is not simply metabolic waste. It can be transported throughout the body, burned as fuel and recycled into other useful molecules. [1,2]

The burning sensation during an intense set of squats or a hard sprint comes from a much broader set of metabolic and cellular changes occurring inside working muscles. Lactate happens to rise at the same time, but that does not make it the sole cause of the burn or fatigue.

And it certainly does not explain why your muscles hurt tomorrow.

Exercise-related lactate begins being processed as soon as it is produced and falls substantially during recovery. It does not remain stored in muscle tissue for the next two or three days. The soreness that appears later is a different phenomenon related to exercise-induced muscle stress and recovery.

So you do not need to “detox” your muscles after a hard workout.

Move lightly if it feels good, replace lost fluids, eat appropriately, sleep well and give heavily exercised muscles enough time to recover. Your body already has an impressive system for dealing with lactate—and far from being the enemy of exercise, lactate is part of the machinery that allows you to keep moving.

References:

  1. Rabinowitz JD, Enerbäck S. Lactate: the ugly duckling of energy metabolism. Nature Metabolism. 2020;2:566-571. (PubMed Central (PMC))
  2. Brooks GA. What the Lactate Shuttle Means for Sports Nutrition. Nutrients. 2023;15(9):2178. (PubMed)
  3. Goodwin ML, Harris JE, Hernández A, Gladden LB. Blood lactate measurements and analysis during exercise: a guide for clinicians. Journal of Diabetes Science and Technology. 2007;1(4):558-569. (PubMed Central (PMC))
  4. Robergs RA, Ghiasvand F, Parker D. Biochemistry of exercise-induced metabolic acidosis. American Journal of Physiology-Regulatory, Integrative and Comparative Physiology. 2004;287:R502-R516. (PubMed)
  5. Green HJ. Mechanisms of muscle fatigue in intense exercise. Journal of Sports Sciences. 1997;15(3):247-256. (PubMed)
  6. Allen DG, Lamb GD, Westerblad H. Skeletal muscle fatigue: cellular mechanisms. Physiological Reviews. 2008;88(1):287-332. (PubMed)
  7. Hureau TJ, et al. On the role of skeletal muscle acidosis and inorganic phosphates as determinants of central and peripheral fatigue. 2022. (PubMed)
  8. Dezman ZDW, et al. Repeat lactate level predicts mortality better than rate of clearance. American Journal of Emergency Medicine. 2018. (PubMed Central (PMC))
  9. Schwane JA, Johnson SR, Vandenakker CB, Armstrong RB. Is lactic acid related to delayed-onset muscle soreness? The Physician and Sportsmedicine. 1983. (PubMed)
  10. Bond V, Adams RG, Tearney RJ, Gresham K, Ruff W. Effects of active and passive recovery on lactate removal and subsequent isokinetic muscle function. Journal of Sports Medicine and Physical Fitness. 1991. (PubMed)
  11. Monedero J, Donne B. Effect of recovery interventions on lactate removal and subsequent performance. International Journal of Sports Medicine. 2000. (PubMed)
  12. Martin NA, Zoeller RF, Robertson RJ, Lephart SM. The comparative effects of sports massage, active recovery, and rest in promoting blood lactate clearance after supramaximal leg exercise. Journal of Athletic Training. 1998;33(1):30-35. (PubMed)
  13. Wiltshire EV, Poitras V, Pak M, Hong T, Rayner J, Tschakovsky ME. Massage impairs postexercise muscle blood flow and “lactic acid” removal. Medicine and Science in Sports and Exercise. 2010;42(6):1062-1071. (PubMed)

Muscle Soreness After Exercise: Why the Ache Shows Up Later

You finish a workout feeling tired but surprisingly good. Then you wake up the next morning, try to walk downstairs, and suddenly your thighs have a different opinion about yesterday’s squats.

Muscle soreness after exercise is extremely common, particularly after starting a new workout, increasing exercise intensity, returning to training after a break, or performing movements your muscles are not accustomed to. The soreness may feel like tenderness, stiffness, aching, reduced flexibility, or discomfort when the affected muscle is stretched or contracted.

For years, one of the most popular explanations was that lactic acid builds up inside the muscles and causes soreness. That explanation is still repeated in gyms and casual conversations, but it does not accurately explain why muscles hurt a day or two after exercise.

The more important factors are unaccustomed muscle contractions, microscopic structural disruption within muscle tissue, changes in muscle-cell function, and the inflammatory and pain-signaling processes that follow exercise. [1,2] Eccentric muscle contractions—movements in which a working muscle lengthens while producing force—are particularly likely to produce delayed soreness.

Understanding what actually happens can help explain why your legs may hurt after hiking downhill, why your chest becomes sore after returning to bench presses, and why an exercise that made you sore last month may barely bother you today.

What Is Muscle Soreness After Exercise?

Not all exercise-related muscle discomfort is the same.

There is an important difference between the burning or fatigue felt during exercise and the soreness that develops many hours later.

The burning sensation you experience during a hard set of squats, sprinting, cycling uphill, or doing repeated push-ups occurs while the muscles are working intensely. During high-intensity exercise, energy demand rises rapidly and numerous metabolic changes occur within the muscle. These changes contribute to fatigue and the uncomfortable burning sensation that can accompany strenuous muscular work.

Delayed onset muscle soreness, however, develops after the workout is over. It is particularly common following strenuous or unfamiliar exercise and tends to become noticeable during the following day rather than immediately after exercise. [2,3]

Typical symptoms include:

  • Aching or tenderness in muscles that were exercised
  • Muscle stiffness
  • Pain when stretching or contracting the affected muscle
  • Temporary reduction in strength
  • Reduced range of motion
  • Mild swelling in some cases
  • Increased sensitivity when the muscle is pressed

The discomfort commonly becomes strongest approximately 24 to 72 hours after the exercise and then gradually improves. In many people, the soreness resolves within several days, although particularly demanding or unfamiliar exercise can produce symptoms lasting closer to a week. [3]

Why Are Muscles Sore the Day After Exercise Instead of Immediately?

This delay is one of the reasons the old lactic acid explanation never fit very well.

If a substance produced during exercise were simply sitting inside the muscle causing pain, soreness would be expected to be most severe during or immediately after exercise. Instead, delayed onset muscle soreness frequently becomes more noticeable many hours later.

That happens because some of the processes involved in soreness develop progressively.

An unfamiliar or strenuous workout can produce microscopic structural changes within muscle fibers and their supporting structures. It can also alter cell membranes, calcium regulation and normal muscle contraction mechanisms. These changes are followed by biological responses involving inflammation and increased sensitivity of pain-sensing nerve endings. [1,4]

The result is that the muscle may feel relatively normal immediately after training but become increasingly tender and stiff during the following 24 to 48 hours.

How Muscle Contractions Cause Post-Exercise Soreness

To understand why certain workouts leave you particularly sore, it helps to understand the three basic ways muscles produce force.

Concentric Muscle Contractions

A concentric contraction occurs when a muscle produces force while shortening.

For example, when performing a biceps curl, the biceps muscle shortens as you lift the dumbbell toward your shoulder.

Other examples include:

  • Rising from the bottom of a squat
  • Pushing yourself upward during a push-up
  • Climbing a staircase
  • Pressing a weight overhead

Concentric contractions can certainly cause fatigue and some soreness, especially when performed at high intensity. However, they generally produce less exercise-induced muscle damage than unfamiliar eccentric exercise.

Eccentric Muscle Contractions

An eccentric contraction occurs when the muscle remains active while lengthening under tension.

Using the biceps curl example, the eccentric portion happens when you slowly lower the dumbbell back toward the starting position.

Common eccentric movements include:

  • Lowering a weight
  • Walking or running downhill
  • Descending stairs
  • Lowering your body during a squat
  • Lowering yourself during a push-up
  • Landing after a jump

Eccentric exercise is especially associated with delayed onset muscle soreness and exercise-induced muscle damage, particularly when the movement is unfamiliar or performed at high intensity or volume. [1,4]

This helps explain an interesting experience familiar to hikers: walking uphill may feel harder during the activity, but walking downhill can leave the thighs much more sore the next day. During the downhill portion, the quadriceps repeatedly contract while lengthening to control the descent.

Isometric Muscle Contractions

An isometric contraction occurs when a muscle generates force without significantly changing length.

Examples include:

  • Holding a plank
  • Holding a wall sit
  • Pausing with a weight in a fixed position

Isometric exercise can also produce fatigue and soreness, but unfamiliar high-force eccentric contractions are particularly well known for causing significant delayed muscle soreness. [5]

What Are the “Microtears” That Happen During Exercise?

You may have heard people say that lifting weights creates tiny tears in your muscles and that these tears cause soreness.

There is some truth behind the idea, but the term muscle microtears simplifies a much more complicated process.

Following strenuous or unfamiliar exercise—especially eccentric exercise—researchers can detect microscopic structural disruption involving muscle fibers and components that help maintain the organization and function of muscle cells. Changes may involve structures called sarcomeres, the muscle cell membrane, the cytoskeleton and systems responsible for calcium regulation and muscle contraction. [4]

Rather than imagining the muscle as being covered with tiny cuts, it is more accurate to think of the muscle as experiencing microscopic exercise-induced disruption and stress that temporarily affects its structure and function.

The body then begins repairing and adapting to that stress.

This repair process is part of how muscles become better prepared for future exercise, but an important distinction should be made: more muscle soreness does not necessarily mean more muscle damage, and more damage does not automatically mean more muscle growth. Studies have shown that perceived delayed onset muscle soreness does not reliably indicate the magnitude of exercise-induced muscle damage. [6]

So being barely able to walk after leg day is not proof that you had a better workout.

How Inflammation Contributes to Muscle Soreness

Microscopic exercise-induced muscle damage initiates a repair response.

Various immune cells and chemical signals become involved in removing damaged material and coordinating tissue recovery. Changes in the local environment surrounding the exercised muscle can increase the sensitivity of nerve endings that detect potentially painful stimuli.

This is one reason a sore muscle may hurt when you press it, stretch it, sit down, climb stairs or contract it.

The inflammatory response should not automatically be viewed as something harmful. Inflammation is part of the body’s normal response to tissue stress and participates in repair and adaptation.

The exact relationship between muscle damage, inflammation and delayed muscle soreness is complex, however. Researchers have found that soreness, inflammatory markers, strength loss and structural muscle damage do not always rise and fall together. Delayed onset muscle soreness therefore reflects a combination of processes rather than one single injury occurring inside the muscle. [2,6]

Does Lactic Acid Cause Muscle Soreness After Exercise?

This is one of the most persistent exercise myths.

Lactic acid accumulation is not considered the cause of the muscle soreness you feel one or two days after exercise.

During intense exercise, carbohydrate metabolism accelerates dramatically. Lactate levels can rise as the body rapidly produces energy. However, lactate is not simply a useless waste product trapped inside muscles. It can be transported between tissues and used as an important metabolic fuel or converted into other energy substrates. [7]

One classic experiment illustrates the problem with blaming lactate for delayed soreness. Researchers compared level running with downhill running. Blood lactate increased considerably during level running, yet the runners did not develop significant delayed muscle soreness. Downhill running produced substantial soreness even though lactate was not elevated in the same manner. [8]

The conclusion was straightforward: elevated lactate during exercise does not explain delayed onset muscle soreness.

Modern research has also challenged the traditional idea that lactate production itself is responsible for the metabolic acidosis associated with intense exercise. [9]

So the familiar phrase “you need to flush the lactic acid out of your muscles” is misleading when discussing soreness that appears the following day.

Then Why Do Muscles Burn During Exercise?

The burning sensation during an intense workout is real. It is simply different from delayed onset muscle soreness.

When muscles work very hard, their demand for energy rises rapidly. Numerous changes occur within the muscle, including alterations in hydrogen ions, inorganic phosphate, potassium, calcium handling and other metabolites involved in muscle contraction and fatigue.

Together, these changes influence how effectively muscle fibers can continue producing force and contribute to the sensation of fatigue and discomfort during intense exercise. [10]

Lactate often rises at the same time because both occur during intense metabolism. That association helped create the historical belief that lactate itself was responsible for the burning sensation and subsequent soreness.

The reality is considerably more complicated.

The burn during your workout and the ache when getting out of bed the next morning should therefore be thought of as related to different physiological processes.

Why Does a New Workout Make You More Sore?

Anyone who has returned to the gym after several months away has probably experienced this.

You may perform what seems like a reasonable workout on Monday and discover on Wednesday that sitting down requires careful planning.

The reason is that unaccustomed exercise is one of the strongest triggers of delayed onset muscle soreness.

Muscles adapt remarkably well to repeated stress. After experiencing a particular eccentric exercise, they frequently show less damage and soreness when exposed to a similar exercise again. This phenomenon is commonly called the repeated bout effect. [11]

This explains why:

  • Your first squat workout may make your legs extremely sore.
  • Several weeks later, the same workout causes much less discomfort.
  • Introducing a new exercise can suddenly make you sore again.
  • Returning after a long training break can recreate the soreness.

The adaptation is one reason gradually progressing an exercise program is usually more comfortable than suddenly performing a large amount of unfamiliar training.

Which Exercises Are Most Likely to Cause Muscle Soreness?

Any sufficiently strenuous or unfamiliar exercise can cause soreness, but activities with a strong eccentric component are particularly likely to do so.

Examples include:

  • Heavy resistance training
  • Squats and lunges
  • Romanian deadlifts
  • Lowering heavy weights slowly
  • Running downhill
  • Hiking downhill
  • Descending long stairways
  • Plyometric jumping
  • Sprinting
  • High-volume push-ups
  • New exercise classes
  • Returning to exercise after a long break

Exercise intensity matters, but novelty is just as important.

A trained runner may complete a long run with little soreness because the body has adapted to running. The same person might experience pronounced muscle soreness after an unfamiliar session of lunges even though the workout lasts only 20 minutes.

Does Muscle Soreness Mean You Are Building Muscle?

Not necessarily.

Soreness is often treated as a badge of honor after training: “If I am not sore tomorrow, the workout did not work.”

That is not a reliable way to judge exercise quality.

Muscle growth is influenced by repeated resistance-training stimulus, mechanical tension, appropriate training volume, recovery, nutrition and progressive overload. Delayed onset muscle soreness may occur during a productive training program, especially when a new stimulus is introduced, but soreness itself is not required for muscle growth.

Likewise, trying to create extreme soreness at every workout may interfere with training quality if strength and movement remain impaired for several days.

A better goal is progressive, sustainable training—not chasing pain.

How Long Should Muscle Soreness Last After Exercise?

Normal delayed onset muscle soreness commonly follows a recognizable pattern.

You may feel little discomfort immediately after exercise. Soreness develops during the following day, often becomes strongest somewhere between 24 and 72 hours, and then gradually subsides. [3]

For many people it is substantially improved within three to five days. More demanding or highly unfamiliar workouts may cause symptoms lasting closer to five to seven days.

The trend matters.

Typical post-exercise soreness should gradually improve rather than become progressively more severe.

What Helps Muscle Soreness After a Workout?

There is no single treatment that instantly eliminates delayed onset muscle soreness. The muscle needs time to recover and adapt.

Several practical strategies may make the recovery period more manageable.

Keep Moving, but Reduce the Intensity

Complete inactivity is not always necessary.

Gentle walking, easy cycling or light movement can temporarily make sore muscles feel better. Earlier research and reviews have found that exercise can provide temporary relief from delayed muscle soreness, although the pain may return afterward. [2]

Avoid interpreting temporary pain relief as proof that the muscle is fully recovered.

Use Massage or Foam Rolling if It Feels Helpful

Massage and other physical recovery strategies have shown some ability to reduce perceived delayed onset muscle soreness in research, although results vary between techniques and studies. [12]

Foam rolling may also improve temporary feelings of stiffness or soreness in some people. It does not literally “push lactic acid out” of the muscle.

Eat Adequate Protein

Protein supplies amino acids required for rebuilding and maintaining muscle tissue.

Adequate dietary protein is therefore important for recovery from resistance exercise. However, protein should not be marketed as a cure for soreness. A systematic review and meta-analysis found that protein intake around resistance exercise could improve some measures of strength recovery and muscle-damage markers but did not consistently reduce reported muscle soreness. [13]

Replace Fluids Lost During Exercise

Hydration is important for normal physical function and recovery, particularly after prolonged exercise, heavy sweating or training in hot conditions.

Drinking water will not “wash away lactic acid” responsible for next-day soreness because retained lactic acid is not causing the soreness in the first place. Nevertheless, replacing fluids lost during exercise remains sensible for overall recovery.

Give the Muscle Time

Sometimes the most effective recovery strategy is also the least exciting: allow adequate time before placing the same muscle under another unusually demanding load.

You do not necessarily need to stop all exercise. A person with sore quadriceps, for example, may be able to train the upper body while allowing the legs to recover.

Should You Work Out When Your Muscles Are Sore?

Mild soreness does not always require skipping exercise.

If soreness is minor and your movement remains normal, light or moderate activity may be reasonable. You may also train a different muscle group.

More caution is appropriate when soreness is severe enough to significantly alter your movement. For example, if your legs are so sore that you cannot squat, walk or descend stairs normally, another intense leg workout is unlikely to be productive.

Training hard while movement mechanics are significantly altered could also place unnecessary stress on joints and other tissues.

A simple principle is useful: exercise should challenge the body without repeatedly overwhelming its ability to recover.

How Can You Prevent Severe Muscle Soreness?

It is impossible to prevent all post-exercise soreness, and mild soreness is not necessarily a problem.

Severe soreness can often be reduced by introducing new exercise gradually.

If you are starting resistance training, returning after a long break or adding unfamiliar eccentric exercises:

  • Begin with fewer sets and repetitions.
  • Use manageable resistance.
  • Increase training volume gradually.
  • Avoid taking every new exercise to complete muscular failure.
  • Introduce downhill running or hiking progressively.
  • Allow recovery between demanding sessions.
  • Maintain regular training rather than alternating prolonged inactivity with extremely strenuous workouts.

Research on eccentric exercise suggests that gradually increasing intensity and volume can reduce the muscle damage associated with suddenly performing high-intensity eccentric contractions. [1]

Your muscles essentially become better prepared for a stress they have experienced before.

Muscle Soreness or Muscle Injury: How Can You Tell the Difference?

Normal exercise soreness usually involves the muscles you trained and tends to develop gradually.

An injury may feel different.

Consider seeking medical evaluation if exercise-related pain is:

  • Sudden and sharp during the exercise
  • Highly localized to one small area
  • Associated with a popping or tearing sensation
  • Accompanied by significant bruising
  • Associated with marked swelling
  • Preventing normal use of the limb
  • Affecting a joint rather than primarily the muscle
  • Getting worse instead of improving
  • Persisting longer than expected

Pain that began suddenly during a particular repetition should not automatically be dismissed as ordinary post-workout soreness.

Severe Muscle Pain and Dark Urine After Exercise Should Not Be Ignored

Very severe muscle symptoms after strenuous exercise can occasionally indicate a much more serious condition called rhabdomyolysis.

In rhabdomyolysis, muscle tissue breaks down excessively and releases intracellular material into the bloodstream. The condition can affect the kidneys and requires medical assessment.

Warning signs include:

  • Muscle pain or cramping that is much more severe than expected
  • Severe weakness
  • Marked swelling
  • Unusual difficulty completing normal physical tasks
  • Dark, tea-colored or cola-colored urine

Symptoms may develop hours or even days after the triggering activity. Anyone experiencing these warning signs after strenuous exercise should seek prompt medical attention rather than assuming it is simply a bad case of workout soreness. [14]

Frequently Asked Questions About Muscle Soreness After Exercise

Why do my muscles hurt two days after working out?

Delayed onset muscle soreness commonly becomes strongest between approximately 24 and 72 hours after unfamiliar or strenuous exercise. The delay reflects the evolving structural, inflammatory and pain-sensitization processes that occur after exercise rather than lactic acid remaining in the muscles. [3,4]

Is lactic acid responsible for sore muscles the next day?

No. Elevated lactate during exercise does not explain delayed muscle soreness. Experimental evidence has demonstrated that exercise can produce substantial lactate without subsequent soreness and substantial soreness without corresponding lactate accumulation. [8]

Why do squats make my legs sore?

Squats contain both concentric and eccentric muscle actions. During the lowering phase, muscles such as the quadriceps and gluteal muscles produce force while lengthening. Unfamiliar or high-volume eccentric loading is particularly associated with exercise-induced muscle damage and delayed soreness. [1]

Are muscle microtears good?

Microscopic muscle disruption can occur after strenuous exercise and forms part of the stimulus to which the body adapts. However, deliberately trying to maximize muscle damage is unnecessary. Greater soreness does not necessarily mean greater muscle damage or a more effective workout. [6]

Why am I less sore after doing the same workout for several weeks?

The muscles adapt to repeated exposure. After an initial unfamiliar exercise bout, subsequent sessions of a similar exercise generally produce less muscle damage and soreness. This protective adaptation is known as the repeated bout effect. [11]

Does stretching remove lactic acid from sore muscles?

No. Delayed soreness is not caused by lactic acid trapped in the muscles, so stretching cannot eliminate soreness by “removing” lactic acid. Gentle stretching may feel comfortable and temporarily reduce stiffness, but stretching has not consistently been shown to prevent delayed muscle soreness. [15]

The Bottom Line

That stiff, aching feeling the day after a tough workout is usually not a pool of lactic acid waiting to be flushed from your muscles.

Post-exercise soreness is more accurately understood as part of the body’s response to unfamiliar or demanding muscular work, particularly eccentric contractions. Those contractions can produce microscopic structural disruption within muscle tissue, temporary changes in muscle function and a subsequent biological response that increases tenderness and pain sensitivity.

The process takes time, which is why soreness often appears the following day and may become most noticeable 24 to 72 hours after exercise.

Lactate does increase during many forms of intense exercise, but it is an important part of normal energy metabolism—not the substance sitting inside your muscles making them hurt two days later.

And perhaps the most useful lesson is that soreness is not a scorecard for workout quality. As your muscles adapt to training, the same workout usually causes less soreness even though it may still be improving strength, fitness and muscle function.

Progressive training, adequate recovery and consistency are far better measures of an effective exercise program than how difficult it is to walk down the stairs the next morning.

References:

  1. Ruas CV, Nosaka K. Eccentric Contractions Are Responsible for Muscle Damage and Neuromuscular Fatigue. American College of Sports Medicine, 2022.
  2. Cheung K, Hume P, Maxwell L. Delayed onset muscle soreness: treatment strategies and performance factors. Sports Medicine. 2003;33(2):145-164.
  3. Wiecha S, et al. Physical therapies for delayed onset muscle soreness. 2024.
  4. Stožer A, et al. Pathophysiology of exercise-induced muscle damage and its structural, functional, metabolic and clinical consequences. Physiology Research. 2020.
  5. Byrnes WC, Clarkson PM. Delayed onset muscle soreness and training. Clinics in Sports Medicine. 1986.
  6. Wilke J, et al. Is delayed onset muscle soreness a false friend? The potential implication for clinical and sports practice. Frontiers in Physiology. 2021.
  7. Rabinowitz JD, Enerbäck S. Lactate: the ugly duckling of energy metabolism. Nature Metabolism. 2020.
  8. Schwane JA, Johnson SR, Vandenakker CB, Armstrong RB. Is lactic acid related to delayed-onset muscle soreness? Physician and Sportsmedicine. 1983.
  9. Robergs RA, Ghiasvand F, Parker D. Biochemistry of exercise-induced metabolic acidosis. American Journal of Physiology-Regulatory, Integrative and Comparative Physiology. 2004.
  10. Allen DG, Lamb GD, Westerblad H. Skeletal muscle fatigue: cellular mechanisms. Physiological Reviews. 2008.
  11. Cleary MA, Kimura IF, Sitler MR, Kendrick ZV. Temporal pattern of the repeated bout effect of eccentric exercise on delayed-onset muscle soreness. Journal of Athletic Training. 2002.
  12. Dupuy O, Douzi W, Theurot D, Bosquet L, Dugué B. An evidence-based approach for choosing post-exercise recovery techniques to reduce markers of muscle damage, soreness, fatigue and inflammation: a systematic review with meta-analysis. Frontiers in Physiology. 2018.
  13. Pearson AG, Hind K, Macnaughton LS. The impact of dietary protein supplementation on recovery from resistance exercise-induced muscle damage: a systematic review with meta-analysis. European Journal of Clinical Nutrition. 2023;77(8):767-783.
  14. National Institute for Occupational Safety and Health. Signs and Symptoms of Rhabdomyolysis. Centers for Disease Control and Prevention. Updated January 14, 2025.
  15. Herbert RD, Gabriel M. Effects of stretching before and after exercising on muscle soreness and risk of injury: systematic review.

Why Dextrose Comes in 5%, 10%, 25% and 50% and Why the Strength Matters

If you have ever looked at an intravenous fluid bag or an emergency medication record, you may have seen terms such as 5% dextrose, 10% dextrose, 25% dextrose, or 50% dextrose. At first glance, the difference may seem simple: one contains more sugar than another. Clinically, however, the concentration can substantially change how much glucose is delivered, how quickly it can be given, the amount of fluid required, and how irritating the solution may be to a vein.

Dextrose is essentially a form of glucose. When given intravenously, it provides glucose that is immediately available in the bloodstream. Depending on the situation, intravenous dextrose may be used to provide carbohydrate calories and water, correct dangerously low blood glucose, accompany insulin treatment for high potassium, or serve as part of intravenous fluid therapy. [1,2,3]

But 50% dextrose is not simply a “better” or more powerful version of 5% dextrose. A highly concentrated dextrose solution can deliver a large amount of glucose in a very small volume, but it is also much more hypertonic and can irritate or damage blood vessels and surrounding tissue if it is administered improperly. [2,3]

Understanding the percentages makes the differences much easier to appreciate.

What Is Dextrose and What Does It Do in the Body?

Dextrose is chemically equivalent to glucose, one of the body’s most important sources of energy. Glucose circulates in the blood and is used by cells throughout the body, particularly the brain, muscles, and other metabolically active tissues.

Under normal circumstances, most glucose comes from food. Carbohydrates are digested and converted into glucose, which enters the bloodstream. Insulin then helps many cells take up glucose and use or store it.

Intravenous dextrose bypasses digestion. Because the glucose is placed directly into the bloodstream, it can increase blood glucose rapidly. This is particularly valuable when someone has severe hypoglycemia and cannot safely eat or drink.

Dextrose solutions can also supply calories when oral intake is inadequate. Five percent and 10% dextrose intravenous solutions are specifically labeled as sources of water and calories and may also be used as diluents for certain medications. [1]

However, dextrose does not replace complete nutrition. A glucose-containing intravenous fluid provides carbohydrate, but it does not by itself provide all of the protein, essential fatty acids, vitamins, minerals, and electrolytes required for long-term nutritional support.

What Does 5%, 10%, 25%, or 50% Dextrose Actually Mean?

The percentage describes the amount of dextrose contained in 100 milliliters of solution.

Therefore:

  • 5% dextrose contains 5 grams of dextrose per 100 milliliters
  • 10% dextrose contains 10 grams per 100 milliliters
  • 25% dextrose contains 25 grams per 100 milliliters
  • 50% dextrose contains 50 grams per 100 milliliters

This difference becomes clinically important when considering how much fluid is needed to provide a particular amount of glucose.

For example, 50% dextrose contains approximately 0.5 gram of dextrose in each milliliter, which means 50 milliliters contains about 25 grams of dextrose. [3]

By comparison, delivering 25 grams of glucose using 10% dextrose requires a much larger volume.

That illustrates the main trade-off: higher concentrations provide more glucose in less fluid, while lower concentrations provide the glucose in a more dilute solution.

The concentration also affects osmolarity. As the percentage of dextrose increases, the solution becomes progressively more concentrated relative to body fluids. This is one reason higher-strength preparations require greater care during intravenous administration.

What Is 5% Dextrose Used For?

Five percent dextrose is one of the most familiar glucose-containing intravenous fluids.

It contains:

5 grams of dextrose per 100 milliliters, or approximately 50 grams per liter.

Unlike the much more concentrated preparations used primarily for rapid glucose replacement, 5% dextrose is commonly used as an intravenous fluid that supplies water plus a modest amount of carbohydrate calories. It may also be used as a diluent for compatible intravenous medications. [1]

A liter of 5% dextrose provides roughly 170 calories from dextrose. [1]

When might 5% dextrose be used?

Depending on the patient’s clinical situation, it may be used when a clinician wants to provide:

  • water together with a small amount of carbohydrate;
  • a continuous source of glucose;
  • an intravenous vehicle for certain medications; or
  • glucose-containing fluid as part of a broader fluid-management plan.

Five percent dextrose should not automatically be thought of as a treatment for every form of dehydration. Once glucose is taken up and metabolized, much of the administered water becomes available as relatively electrolyte-free water. The patient’s sodium level, glucose level, kidney function, fluid status, and reason for receiving intravenous fluids therefore matter.

It also contains no sodium, potassium, or other electrolytes unless those ingredients have specifically been added to the fluid formulation.

What Is 10% Dextrose Used For?

Ten percent dextrose contains twice the glucose concentration of 5% dextrose:

10 grams per 100 milliliters, or approximately 100 grams of dextrose per liter.

It provides approximately 340 calories per liter. [1]

Ten percent dextrose may be used as a source of carbohydrate and water, but it is also important in the treatment of hypoglycemia, particularly in emergency and hospital protocols where clinicians want to raise blood glucose in a controlled manner.

Why might 10% dextrose be chosen instead of 50% dextrose?

The advantage is not that 10% dextrose contains more glucose—it obviously contains less glucose per milliliter.

Its advantage is that glucose can be titrated using a more dilute solution.

A randomized study comparing 10% with 50% intravenous dextrose in adults with hypoglycemia found similar time to recovery, while patients treated with 10% dextrose received a lower total dose of glucose and had lower post-treatment blood glucose levels. [4]

This helps explain why some emergency medical systems and hospitals use lower-concentration dextrose rather than automatically giving a highly concentrated bolus.

Treatment practices vary, however. The concentration selected depends on the patient’s condition, intravenous access, local protocol, age, fluid status, and severity of hypoglycemia.

What Is 25% Dextrose Used For?

Twenty-five percent dextrose contains:

25 grams of dextrose per 100 milliliters, equivalent to 250 milligrams per milliliter.

This is substantially more concentrated than either 5% or 10% dextrose.

Certain 25% dextrose products are used for the treatment of acute symptomatic hypoglycemia in pediatric patients. Product indications and age ranges can differ, so the specific formulation and prescribing information matter. [2]

Because 25% dextrose is highly hypertonic, intravenous administration requires particular care. Current product labeling warns that concentrated 25% dextrose can cause phlebitis and thrombosis, and accidental leakage of a concentrated solution outside the vein must be avoided. [2]

This is a key point for patients reading medical records: seeing “25% dextrose” does not simply mean the doctor wanted a stronger sugar solution. The concentration may have been selected to balance the required amount of glucose, the amount of fluid being administered, patient age, and the type of intravenous access available.

What Is 50% Dextrose Used For?

Fifty percent dextrose is a very concentrated glucose preparation.

It contains:

50 grams of dextrose per 100 milliliters, or approximately 0.5 gram per milliliter.

A commonly encountered 50-milliliter preparation therefore contains about 25 grams of dextrose. [3]

Its major advantage is obvious: a substantial amount of glucose can be delivered using a relatively small volume.

Fifty percent dextrose has long been used to rapidly restore blood glucose in severe hypoglycemia, particularly when a patient cannot safely swallow oral glucose. Current United States labeling includes treatment of insulin-induced hypoglycemia, although exact approved indications and age recommendations vary by product. [3]

Why does 50% dextrose require more caution?

Concentration is the reason.

Current labeling describes 50% dextrose as having an osmolarity above 900 milliosmoles per liter and warns that it can cause venous irritation. Slow administration into an appropriate vein is recommended, with central or large peripheral venous access used depending on patient age and circumstances. [3]

If concentrated dextrose escapes from the intravenous catheter into surrounding tissue—a problem known as extravasation—local tissue injury can occur.

Rapid administration may also cause excessive elevations in blood glucose and hyperosmolarity. [3]

Therefore, while 50% dextrose can correct glucose rapidly, more concentrated does not automatically mean safer or preferable.

Dextrose 10% Versus Dextrose 50% for Low Blood Sugar

This is one of the most common questions surrounding intravenous dextrose.

If both solutions can deliver the same total number of grams of glucose, why not always use 50% dextrose?

The answer involves concentration, volume and control.

With 50% dextrose, a relatively small volume contains a large glucose dose. That can be useful when fluid volume needs to be limited or rapid glucose delivery is required.

With 10% dextrose, the same amount of glucose requires more fluid, but clinicians can administer smaller incremental amounts of glucose and reassess the patient.

In one randomized prehospital trial, 10% and 50% dextrose produced similar recovery times in adults with hypoglycemia, but the 10% group received less total dextrose and had lower blood glucose after treatment. [4]

This does not mean that 10% dextrose is appropriate in every situation or that 50% dextrose should never be used. Rather, it demonstrates why clinicians may deliberately choose a lower concentration even when a stronger preparation is readily available.

How Does Intravenous Dextrose Treat Severe Hypoglycemia?

Hypoglycemia means the blood glucose level has fallen too low.

Symptoms may include:

  • sweating;
  • shaking;
  • hunger;
  • palpitations;
  • weakness;
  • dizziness;
  • confusion;
  • abnormal behavior;
  • blurred vision;
  • seizures; or
  • loss of consciousness.

For a person who is awake and able to swallow safely, oral glucose or another rapidly absorbed carbohydrate may be appropriate.

The situation changes when someone is severely confused, having a seizure, unconscious, or unable to swallow safely. Giving food or liquid by mouth can create an aspiration risk. Intravenous dextrose allows glucose to enter the bloodstream directly.

Treatment does not necessarily end as soon as the person wakes up. The underlying cause of hypoglycemia may still be present—for example, long-acting insulin or a glucose-lowering medication may continue working.

Blood glucose therefore needs to be rechecked after treatment, and additional carbohydrate, intravenous glucose, observation, or other treatment may be necessary. Current diabetes hospital guidance recommends repeated glucose monitoring after hypoglycemia treatment until blood glucose has stabilized. [5]

Why Is Dextrose Given With Insulin for High Potassium?

Dextrose has another important use that can initially seem confusing.

A patient with hyperkalemia, or dangerously high blood potassium, may receive insulin even if the patient does not have diabetes.

Insulin stimulates movement of potassium from the bloodstream into cells, which can temporarily lower the concentration of potassium in the blood.

But insulin also moves glucose out of the bloodstream. As a result, giving insulin for hyperkalemia can produce hypoglycemia.

Dextrose is therefore frequently administered with insulin to provide glucose while the insulin is being used to shift potassium into cells.

In other words:

The insulin is primarily being used to lower the blood potassium temporarily; the dextrose helps protect against insulin-induced low blood sugar.

Contemporary resuscitation guidance includes intravenous insulin together with glucose for moderate and severe hyperkalemia, followed by glucose monitoring because hypoglycemia can occur after treatment. [6]

This is a good example of why seeing dextrose on a medication record does not necessarily mean that the patient originally had low blood sugar.

How Do Doctors Decide Which Dextrose Concentration to Give?

There is no rule that the most severe condition always gets the highest dextrose percentage.

Clinicians consider several factors.

How low is the blood glucose?

A mildly low glucose level in an alert patient is very different from profound hypoglycemia associated with seizure or unconsciousness.

Can the patient safely swallow?

If the person can eat or drink safely, intravenous glucose may not be necessary.

How much glucose is required?

The clinician considers the amount of glucose needed rather than simply choosing a percentage.

What intravenous access is available?

Highly concentrated dextrose is more irritating to veins. The size and location of the intravenous catheter and whether central venous access is available may influence concentration choice. [2,3]

Is fluid volume a concern?

A lower concentration requires more liquid to provide an equivalent glucose dose. That may matter in patients for whom excessive fluid administration could be problematic.

What is the patient’s age?

Pediatric and neonatal glucose management differs from adult treatment, and product labeling for 25% and 50% dextrose includes age-specific precautions and administration recommendations. [2,3]

Is continued glucose support needed?

A single concentrated dose may correct an immediate glucose crisis, but some patients require a continued infusion because the cause of hypoglycemia persists.

Why Is Stronger Dextrose Not Always Better?

It is easy to assume that if 10% dextrose works, 50% should work four or five times better.

That is not how intravenous glucose treatment is approached.

The goal is generally to provide enough glucose to correct the problem without unnecessarily overshooting blood glucose levels or exposing the patient to avoidable complications.

Higher-concentration dextrose has several disadvantages.

It is more hypertonic, which means it can be harder on peripheral veins. It can cause phlebitis and thrombosis. If extravasation occurs, concentrated solutions pose a greater concern for local tissue injury. Rapid administration can also lead to marked hyperglycemia and increased serum osmolality. [2,3]

Lower-concentration solutions require more fluid, however, so they have their own limitations.

The best concentration is therefore the one suited to the clinical objective, glucose requirement, route of administration, fluid requirement and individual patient.

What Are the Possible Risks and Side Effects of Intravenous Dextrose?

Intravenous dextrose is routinely used in medical care, but it is still a medication and fluid therapy that requires monitoring.

Potential complications include:

High blood sugar

Too much dextrose or excessively rapid administration may cause significant hyperglycemia. Highly concentrated preparations require particularly careful administration. [2,3]

Hyperosmolarity

A rapid rise in glucose can raise blood osmolality. Severe hyperglycemia and hyperosmolar states can cause neurological symptoms and other serious complications. [3]

Phlebitis or thrombosis

Concentrated dextrose can irritate veins and contribute to inflammation or thrombosis. [2,3]

Extravasation injury

If a concentrated dextrose solution leaks from the vein into surrounding tissue, local injury can occur.

Fluid overload

Dextrose solutions add fluid as well as glucose. Depending on the volume and rate given, intravenous dextrose can contribute to fluid overload, including pulmonary edema in susceptible patients. [1,2,3]

Sodium and other electrolyte disturbances

Dextrose infusions can affect water and electrolyte balance. Current labeling warns about hyponatremia and notes that potassium and phosphate deficits may occur with prolonged therapy. [1,2,3]

This is why hospitalized patients receiving substantial or prolonged intravenous dextrose may have glucose levels, electrolytes, fluid balance and other laboratory measurements monitored.

Is Dextrose Safe for People With Diabetes?

Dextrose can raise blood glucose rapidly, so patients with diabetes generally require careful monitoring when receiving it.

However, having diabetes does not mean dextrose can never be given.

A person taking insulin, for example, may develop severe hypoglycemia and require intravenous glucose precisely because the blood glucose has fallen dangerously low. Similarly, a person with diabetes who develops severe hyperkalemia may require insulin and glucose as part of emergency treatment.

The immediate medical problem determines whether dextrose is appropriate.

Clinicians then monitor glucose and adjust treatment accordingly.

Frequently Asked Questions About Dextrose Concentrations

Does 5% dextrose mean the solution is 5% sugar?

Essentially, it means there are 5 grams of dextrose in every 100 milliliters of solution.

How much glucose is in 10% dextrose?

Ten percent dextrose contains 10 grams per 100 milliliters, or approximately 100 grams per liter.

How much glucose is in 50% dextrose?

Fifty percent dextrose contains approximately 0.5 gram per milliliter. Therefore, 50 milliliters contains about 25 grams of dextrose. [3]

Is 50% dextrose always used for severe hypoglycemia?

No. Different emergency and hospital protocols use different concentrations. Ten percent dextrose can also be used to correct significant hypoglycemia, and evidence has shown effective recovery using this more dilute concentration. [4]

Why would a doctor use 10% instead of 50% dextrose?

Using a lower concentration can allow glucose to be given incrementally and may reduce excessive post-treatment glucose elevations. It is also less concentrated than 50% dextrose, although it requires more fluid to deliver the same number of grams of glucose. [4]

Can dextrose be given when blood sugar is normal?

Yes. Intravenous dextrose has uses other than treating hypoglycemia. Examples include providing carbohydrate calories and giving glucose alongside insulin during treatment for hyperkalemia. [1,6]

Does dextrose lower potassium?

Not directly. In emergency hyperkalemia treatment, insulin is what shifts potassium into cells. Dextrose is given with insulin primarily to help prevent the blood glucose from falling too low. [6]

The Bottom Line

The difference between 5%, 10%, 25%, and 50% dextrose is much more than a number on an intravenous bag or syringe.

Five percent dextrose contains 5 grams of glucose per 100 milliliters, while 50% dextrose contains ten times that concentration. As the concentration rises, substantially more glucose can be delivered in a smaller amount of fluid.

That can be useful in an emergency—but concentrated dextrose also becomes increasingly hypertonic and requires greater attention to the intravenous route, administration rate, blood glucose response and risk of vein or tissue injury.

Five percent and 10% dextrose may be used to provide water and carbohydrate calories, while 10%, 25%, and 50% preparations can have roles in glucose replacement depending on the patient and clinical protocol. Dextrose may also accompany insulin during emergency treatment of high potassium.

The key principle is that the highest dextrose concentration is not automatically the best concentration. Doctors choose the preparation based on how much glucose is needed, how quickly it is needed, the patient’s age and condition, fluid requirements, intravenous access, and the risks associated with a highly concentrated solution.

Intravenous dextrose should therefore be viewed as a carefully selected treatment—not simply “sugar water.”

This article is intended for general education and should not be used to determine an intravenous dextrose dose or concentration. Severe hypoglycemia, loss of consciousness, seizures and severe hyperkalemia require urgent medical treatment.

References:

  1. MedlinePlus Medical Encyclopedia. Whiplash. Updated January 14, 2026.
  2. National Health Service. Whiplash. Guidance on symptoms, recovery, activity, and when to seek medical care.
  3. National Health Service. Sprains and Strains. Guidance on expected recovery time for uncomplicated soft-tissue injuries.
  4. East of England Ambulance Service NHS Trust. Minor Whiplash. Patient guidance regarding delayed symptom onset and progression following whiplash injury.
  5. Centers for Disease Control and Prevention. Symptoms of Mild Traumatic Brain Injury and Concussion. Updated May 15, 2024.
  6. Centers for Disease Control and Prevention. Signs and Symptoms of Concussion – Concussion Danger Signs.
  7. MedlinePlus Medical Encyclopedia. Spinal Injury and Spinal Cord Trauma. Guidance regarding neurological symptoms following spinal trauma.
  8. MedlinePlus Medical Encyclopedia. Bleeding. Guidance regarding symptoms associated with significant bleeding and shock. Updated October 14, 2025.
  9. American College of Radiology. Appropriateness Criteria: Acute Spinal Trauma. Guidance regarding imaging following cervical spine trauma and persistent neurological symptoms.
  10. MedlinePlus. Concussion. Updated November 24, 2025. Guidance regarding delayed concussion symptoms and symptoms requiring medical evaluation.

How Long Should Soreness Last After a Car Accident? When Pain Is Normal and When It Is Not

Walking away from a car accident without a broken bone or an obvious wound can feel reassuring. Then the next morning arrives.

Your neck is stiff. Your shoulders hurt. Your lower back feels as though you spent the previous day lifting furniture. Turning your head is uncomfortable, getting out of bed takes more effort than usual, and areas that felt fine immediately after the crash suddenly ache.

This delayed soreness after a car accident is common. The forces involved in a collision can stretch muscles, ligaments, tendons, joints, and other soft tissues even when there is no immediately visible injury. Whiplash symptoms, in particular, may not appear until several hours after an accident and can become more noticeable during the following day or days. [1,2]

But there is an important distinction between expected soreness after a car accident and pain that could indicate a more significant injury.

So, how long should soreness last after a car accident? For many minor muscle strains and sprains, symptoms begin improving within days and are substantially better within a couple of weeks. More significant soft-tissue injuries may take several weeks, while whiplash symptoms can sometimes persist for two to three months or longer. [2,3]

The timeline alone, however, does not tell the whole story. Pain that is steadily improving is very different from pain that is intensifying, spreading, or appearing along with weakness, numbness, confusion, repeated vomiting, breathing difficulty, or loss of bowel or bladder control.

Understanding that difference can help you know when soreness is part of recovery and when it deserves medical attention.

Why Are You Sore After a Car Accident Even If You Felt Fine at First?

A motor vehicle collision subjects the body to forces that occur far more quickly than the muscles can consciously react to.

When one vehicle is struck by another, the torso may move with the seat while the head, arms, and legs move at slightly different speeds. Seat belts restrain the body and significantly reduce the risk of serious injury, but the sudden acceleration and deceleration can still stress muscles, joints, ligaments, and tendons.

This is particularly noticeable in the neck.

During a rear-end collision, for example, the neck may rapidly move backward and then forward. That movement can injure the soft tissues around the cervical spine and produce what is commonly called whiplash.

Symptoms do not necessarily begin at the moment of impact. Neck pain from whiplash may take hours to develop, and soreness or stiffness may become more noticeable later that evening or the following morning. [1,4]

Delayed symptoms do not automatically mean that the injury is becoming dangerous. They do, however, mean that feeling fine immediately after the collision does not always rule out an injury.

How Long Should Soreness Last After a Car Accident?

There is no universal recovery timeline because “car accident soreness” can describe several different injuries.

A mild muscle strain may settle relatively quickly. A ligament sprain can take longer. Whiplash may cause symptoms for weeks. A herniated disc, fracture, nerve injury, concussion, or more significant soft-tissue injury can follow a completely different course.

As a general guide, most uncomplicated sprains and strains should show meaningful improvement within approximately two weeks, although complete healing may take longer. [3]

Whiplash often has a longer recovery period. Many people improve within several weeks, but symptoms can persist for two to three months, and some people experience longer-lasting problems. [2]

Rather than asking only, “How many days have I been sore?” it is useful to ask:

  • Is the pain gradually becoming less intense?
  • Is movement getting easier?
  • Are you sleeping better?
  • Are you able to resume more of your normal activities?
  • Is the soreness remaining in the same area rather than spreading?
  • Have any new neurological symptoms appeared?

A person who is mildly sore 10 days after an accident but improving every day may be following a reasonable recovery pattern. Someone whose pain is significantly worse on day 10 than it was on day three deserves a closer look.

Is It Normal to Feel Worse the Day After a Car Accident?

Yes, it can be.

One of the most common questions after a collision is, “Why am I more sore the day after my car accident?”

Whiplash symptoms can take several hours to become apparent, and pain and stiffness may be worse the following day. [4]

A person may therefore go home from an accident thinking they escaped injury, only to wake up with:

  • Neck stiffness
  • Shoulder pain
  • Upper back soreness
  • Lower back pain
  • Headache
  • Muscle spasms
  • General body aches
  • Tenderness where the seat belt contacted the body

This pattern can occur with soft-tissue injury.

What should not simply be dismissed as routine soreness is rapidly worsening severe pain or new symptoms suggesting injury to the brain, spine, nerves, chest, or abdomen.

Common Causes of Body Aches and Soreness After a Car Accident

Muscle Strains and Ligament Sprains

Muscles and ligaments can be stretched beyond their normal range during a collision. This may cause tenderness, stiffness, swelling, spasms, or pain with movement.

Minor strains and sprains commonly begin improving within the first couple of weeks, although more severe soft-tissue injuries can require substantially longer to heal. [3]

Whiplash

Whiplash is one of the best-known causes of neck soreness after a car accident.

Typical symptoms include neck pain, stiffness, reduced range of motion, headaches, and discomfort affecting the shoulders or arms. [1,2]

The pain may not begin immediately. This delayed onset is one reason neck symptoms that appear later in the day or the day after a collision should not automatically be considered unusual.

Back Strain

The lumbar and thoracic muscles can be stretched during sudden twisting, bending, or forward-and-back movement of the torso.

Lower back soreness after a car accident may feel like:

  • Tightness across the lower back
  • Pain when bending
  • Pain getting into or out of a chair
  • Increased discomfort after sitting
  • Muscle spasms
  • Tenderness beside the spine

Muscular back pain should generally trend toward improvement. Pain accompanied by leg weakness, spreading numbness, difficulty walking, or bowel or bladder changes requires more urgent assessment.

Bruising From the Seat Belt

A seat belt may leave tenderness or bruising across the shoulder, chest, or lower abdomen after a substantial collision.

Minor surface bruising can be painful without indicating a serious injury. However, significant chest or abdominal pain, increasing swelling, difficulty breathing, faintness, or symptoms of shock should not be assumed to be simple seat-belt soreness.

Joint Injuries

Shoulders, knees, wrists, hips, and other joints can be injured when the body strikes the steering wheel, dashboard, door, center console, or another part of the vehicle.

Joint pain that becomes increasingly swollen, unstable, severely painful, or difficult to bear weight on may need further evaluation.

Sore Three Days After a Car Accident: Is That Normal?

Being sore three days after a car accident can still fall within the expected period for many soft-tissue injuries.

What matters is how the symptoms are behaving.

If the soreness peaked during the first day or two and is beginning to ease, that is generally more reassuring than pain that continues to escalate.

For example, neck stiffness that was severe on the second morning but is slightly easier on the third or fourth day suggests a different pattern from neck pain that suddenly begins shooting into the arm with numbness or hand weakness.

The same principle applies to lower back pain.

General muscular soreness that gradually becomes easier is different from back pain that begins radiating into the leg and is accompanied by weakness or loss of sensation.

Sore a Week After a Car Accident: Should You Be Concerned?

Not necessarily.

Soft-tissue injuries frequently require more than a few days to recover. Many sprains and strains are still symptomatic at one week, although most uncomplicated injuries should be heading in the right direction by around two weeks. [3]

Whiplash may take considerably longer. [2]

However, soreness lasting a week becomes more important when:

  • The pain has not improved at all
  • The pain is becoming worse
  • Pain is preventing normal walking or movement
  • You cannot turn your head adequately
  • Pain repeatedly wakes you from sleep
  • You develop numbness or tingling
  • Pain begins radiating into an arm or leg
  • You develop weakness
  • Headaches become frequent or increasingly severe

Persistent symptoms do not automatically mean something serious is wrong. They may indicate that the injury deserves a more thorough evaluation or a different treatment approach.

Can You Still Be Sore Weeks After a Car Accident?

Yes.

Some people expect every car accident injury to resolve within several days. That is not always realistic.

More significant strains and sprains can take several weeks or even months to fully recover. Whiplash commonly improves within weeks but may continue for two to three months in some cases. [2,3]

Persistent pain can also occur because the original injury involved more than simple muscle soreness.

Possible causes of prolonged neck or back pain after a car accident include:

  • Persistent muscle or ligament injury
  • Whiplash-associated disorder
  • Joint irritation
  • Disc injury
  • Nerve irritation or compression
  • Fracture
  • Aggravation of pre-existing degenerative spinal changes
  • Post-concussion symptoms

Pain lasting for weeks therefore deserves to be considered in context rather than dismissed merely because initial imaging or examination did not show a major injury.

Delayed Pain After a Car Accident: How Late Can Symptoms Appear?

Some accident-related symptoms may not be recognized immediately.

Whiplash pain can develop several hours after the collision. [1,2] Concussion symptoms may also be delayed or may become more apparent as time passes. [5]

A concussion does not always require a dramatic loss of consciousness. Symptoms can include:

  • Headache
  • Dizziness
  • Nausea
  • Balance problems
  • Sensitivity to light or noise
  • Difficulty concentrating
  • Feeling mentally slowed down
  • Memory difficulties
  • Unusual fatigue
  • Irritability
  • Sleep changes

Because symptoms after a crash can evolve, paying attention to how you feel during the first several days is important even when you initially felt relatively well.

Symptoms After a Car Accident That Should Not Be Ignored

Ordinary muscle soreness is one thing. Certain symptoms deserve prompt or emergency medical attention.

1. A Headache That Keeps Getting Worse

Headaches may occur with whiplash or concussion, but a headache that becomes progressively more severe after a head injury is considered a concussion danger sign. [6] This is particularly concerning if the headache occurs with vomiting, confusion, severe drowsiness, weakness, or vision changes.

2. Repeated Vomiting

Nausea may occur after a concussion, but repeated vomiting after a head injury is a warning sign that should not simply be watched at home. [6]

3. Increasing Confusion or Unusual Behavior

Confusion, agitation, inability to recognize familiar people or places, or other significant changes in behavior after a crash can indicate a potentially serious head injury. [6]

4. Extreme Drowsiness or Difficulty Waking Up

Increasing difficulty staying awake or being unable to wake normally after a head injury warrants urgent medical attention. [6]

5. Slurred Speech, Weakness, or Poor Coordination

New weakness, numbness, slurred speech, or decreased coordination can indicate neurological injury and should not be attributed to ordinary post-accident soreness. [6]

6. Numbness or Tingling That Spreads Into an Arm or Leg

Spinal injuries can produce numbness, tingling, weakness, difficulty walking, or changes in sensation. [7] Occasional mild tingling caused by positioning is different from persistent or progressive neurological symptoms after trauma.

7. New Arm or Leg Weakness

Weakness deserves particular attention. If you begin dropping objects, cannot grip normally, have trouble lifting an arm, notice one leg giving way, or find walking unexpectedly difficult, seek medical evaluation. Persistent neurological symptoms after cervical spine trauma may also affect decisions about whether additional imaging is appropriate. [9]

8. Loss of Bowel or Bladder Control

New inability to control the bladder or bowel after spinal trauma is not a normal consequence of muscle soreness. Loss of bladder or bowel control is among the symptoms that can occur with significant spinal injury and warrants emergency medical evaluation. [7]

9. Severe or Increasing Abdominal Pain

Abdominal pain after a crash should be taken seriously, particularly following a high-impact collision or when there is substantial bruising. Seek urgent assessment for severe or worsening abdominal pain, abdominal swelling, faintness, weakness, clammy skin, confusion, or other symptoms suggesting significant blood loss. Internal bleeding can produce symptoms such as dizziness, weakness, rapid pulse, shortness of breath, pale skin, confusion, and clammy skin. [8]

10. Chest Pain or Difficulty Breathing

Chest soreness may occur from the seat belt or impact with the vehicle interior, but significant chest pain and breathing difficulty should not be dismissed as bruising. These symptoms may require urgent assessment to rule out injury involving the ribs, lungs, heart, or other structures.

11. Severe Neck or Back Pain

Mild or moderate soreness is common after collisions. Severe spinal pain is different. Urgent evaluation is particularly important when severe neck or back pain is accompanied by weakness, numbness, tingling, difficulty walking, loss of coordination, or loss of bowel or bladder control.

12. Pain That Continues to Get Worse Instead of Better

Pain does not have to disappear immediately, but the overall trajectory matters. If your pain continues intensifying several days after the accident, becomes severe, spreads to another area, or is joined by new symptoms, it is reasonable to seek reassessment rather than assuming you simply need more recovery time.

What About Neck and Back Soreness After a Rear-End Collision?

Rear-end accidents are strongly associated with rapid back-and-forth movement of the head and neck, making whiplash an important consideration.

Someone with whiplash may experience:

  • Neck stiffness
  • Difficulty turning the head
  • Pain at the base of the skull
  • Headaches
  • Shoulder or upper back pain
  • Muscle spasms
  • Arm discomfort

Symptoms may begin several hours after the collision rather than immediately. [1,2]

Most people improve with time, but persistent or progressive neurological symptoms need further assessment. When neurological symptoms continue after cervical spine trauma, magnetic resonance imaging may sometimes be considered as part of the evaluation depending on the clinical situation. [9]

Does Soreness Mean You Need an X-Ray or Magnetic Resonance Imaging?

Not necessarily.

Imaging decisions after an accident depend on factors such as:

  • The type and force of the collision
  • Location and severity of pain
  • Age
  • Physical examination findings
  • Midline spinal tenderness
  • Neurological symptoms
  • Ability to move or bear weight
  • Whether a fracture is suspected
  • Whether symptoms persist or worsen

Simply being sore does not automatically mean everyone needs an X-ray, computed tomography scan, or magnetic resonance imaging scan.

On the other hand, persistent neurological symptoms, significant trauma, suspected spinal injury, or other concerning findings may change the imaging decision. [9]

This is why two people involved in the same accident may appropriately receive very different evaluations.

What Can You Do for Mild Soreness After a Car Accident?

If a healthcare professional has ruled out a serious injury and your symptoms appear consistent with a minor soft-tissue injury, recovery usually involves gradually returning to normal movement rather than remaining completely inactive for prolonged periods.

Depending on the specific injury and your medical history, management may include:

  • Temporarily reducing activities that clearly aggravate the pain
  • Gentle movement within a comfortable range
  • Gradually returning to ordinary daily activity
  • Using prescribed or recommended pain treatment appropriately
  • Following a physical therapy program when advised
  • Paying attention to changes in symptoms

With whiplash, prolonged avoidance of movement is generally not the goal. Staying active within reasonable limits and gradually returning to normal activities can be part of recovery. [2]

If movement causes severe pain, neurological symptoms, dizziness, or other concerning symptoms, however, further medical evaluation is more important than attempting to exercise through it.

When Should You See a Doctor for Soreness After a Car Accident?

Consider medical evaluation after a collision if soreness is significant, persists, interferes with normal activity, or behaves differently from ordinary muscle pain.

You should be especially cautious when:

  • Pain is moderate to severe
  • Symptoms continue worsening after the first few days
  • You have significant neck or back pain
  • You hit your head
  • You develop headaches, dizziness, nausea, or concentration problems
  • Pain radiates into an arm or leg
  • You notice numbness, tingling, or weakness
  • Walking becomes difficult
  • You have substantial chest or abdominal pain
  • Symptoms are not showing meaningful improvement over time

After trauma, a clinician can assess whether the problem appears to be a strain, whiplash injury, joint injury, nerve problem, concussion, fracture, or another condition that requires different management.

Do Not Judge an Injury Only by the Damage to the Car

A frequent assumption is that a relatively minor-looking vehicle collision could not have caused a meaningful injury.

Vehicle damage and human injury, however, are not interchangeable measurements.

The way the body moves in a collision depends on many factors, including the direction of impact, seating position, restraint use, head position, and individual anatomy.

Likewise, severe-looking vehicle damage does not tell you precisely which injuries a particular occupant sustained.

Symptoms and medical findings should therefore be assessed on their own merits.

The Most Useful Question Is Not Just “How Long Have I Been Sore?”

When people search “how long should soreness last after a car accident,” they often want a specific cutoff: three days, seven days, two weeks.

Recovery is rarely that precise.

A better question is: “Are my symptoms behaving like a recovering soft-tissue injury, or are they suggesting something that needs further evaluation?”

Mild soreness that gradually decreases, movement that slowly improves, and steadily increasing activity are generally more reassuring.

Pain that becomes increasingly severe, begins radiating, causes weakness or numbness, or occurs with neurological, abdominal, chest, or significant head-injury symptoms is different.

Frequently Asked Questions About Soreness After a Car Accident

How long does muscle soreness last after a car accident?

Minor muscle strains and sprains often show significant improvement within approximately two weeks, although complete healing can take longer. [3] More significant injuries may require several weeks or months.

Is it normal to hurt more two days after a car accident?

It can be. Whiplash symptoms may take hours to appear, and pain or stiffness can become more noticeable during the day after an accident or over the next several days. [1,4]

Why does my whole body hurt after a car accident?

A collision can strain multiple muscle groups at once. The neck, shoulders, upper back, lower back, hips, and extremities may all absorb forces during sudden acceleration, deceleration, twisting, bracing, or impact. Whole-body soreness that gradually improves can occur after a crash. Severe, worsening, or unusual symptoms should be evaluated.

How long does whiplash soreness last?

Whiplash often improves over several weeks, although symptoms may persist for two to three months and occasionally longer. [2]

Is neck pain a week after a car accident normal?

Neck soreness can still be present one week after a collision, particularly with whiplash. The more important issue is whether symptoms are gradually improving and whether any neurological symptoms have developed.

Is lower back pain normal after a car accident?

Lower back pain can occur because of muscle strain, joint irritation, or other injuries during a collision. Persistent pain, radiating leg pain, numbness, weakness, difficulty walking, or bowel or bladder changes should be evaluated promptly.

When should delayed pain after a car accident worry me?

Delayed pain becomes more concerning when it is severe, rapidly worsening, associated with weakness or numbness, or accompanied by significant headache, repeated vomiting, confusion, breathing difficulty, abdominal pain, faintness, or bowel or bladder changes.

Final Takeaway: Watch the Pattern, Not Just the Number of Days

Some soreness after a car accident can be expected, particularly after the body has been suddenly thrown forward, backward, or sideways.

Symptoms may not be obvious immediately. Neck pain and whiplash symptoms can appear several hours later, and many people feel considerably stiffer the morning after an accident. [1,4]

Minor soft-tissue injuries frequently begin improving within days and are often noticeably better by around two weeks, although complete recovery can take longer. Whiplash may require several weeks and sometimes two to three months to settle. [2,3]

The calendar, however, should never be the only guide.

Improving soreness is different from worsening pain.

Seek medical attention when pain becomes severe or progressively worse, or when soreness is accompanied by symptoms such as numbness, weakness, difficulty walking, worsening headache, repeated vomiting, confusion, extreme drowsiness, chest or abdominal pain, difficulty breathing, faintness, or loss of bowel or bladder control.

After a car accident, the most reassuring sign is not simply that several days have passed. It is that your symptoms are moving steadily in the right direction.

References:

  1. MedlinePlus Medical Encyclopedia. Whiplash. Updated January 14, 2026.
  2. National Health Service. Whiplash. Guidance on symptoms, recovery, activity, and when to seek medical care.
  3. National Health Service. Sprains and Strains. Guidance on expected recovery time for uncomplicated soft-tissue injuries.
  4. East of England Ambulance Service NHS Trust. Minor Whiplash. Patient guidance regarding delayed symptom onset and progression following whiplash injury.
  5. Centers for Disease Control and Prevention. Symptoms of Mild Traumatic Brain Injury and Concussion. Updated May 15, 2024.
  6. Centers for Disease Control and Prevention. Signs and Symptoms of Concussion – Concussion Danger Signs.
  7. MedlinePlus Medical Encyclopedia. Spinal Injury and Spinal Cord Trauma. Guidance regarding neurological symptoms following spinal trauma.
  8. MedlinePlus Medical Encyclopedia. Bleeding. Guidance regarding symptoms associated with significant bleeding and shock. Updated October 14, 2025.
  9. American College of Radiology. Appropriateness Criteria: Acute Spinal Trauma. Guidance regarding imaging following cervical spine trauma and persistent neurological symptoms.
  10. MedlinePlus. Concussion. Updated November 24, 2025. Guidance regarding delayed concussion symptoms and symptoms requiring medical evaluation.